
In this guide
What does injecting testosterone involve?
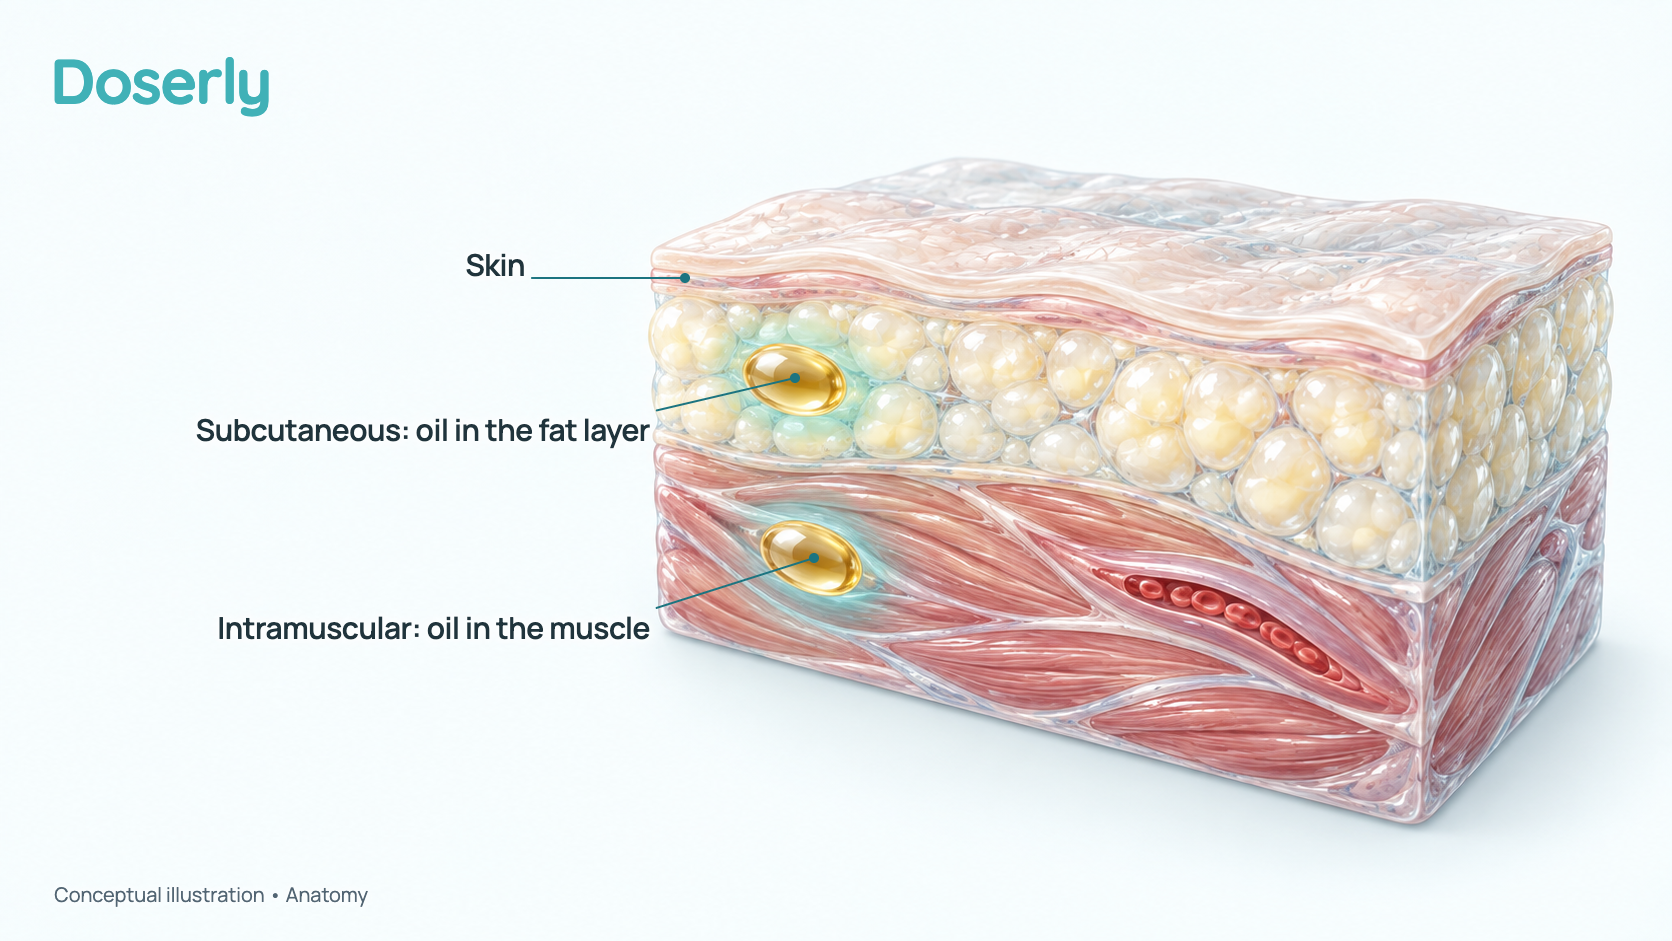
Most injectable testosterone is an ester, testosterone with a small chemical tail, dissolved in oil. Injected into a muscle, the oil forms a small pool called a depot, and the testosterone seeps out of it slowly. That is why injections are given weekly or every few weeks rather than every day. [1], [2]
There are two routes. Intramuscular injection (IM, into a muscle) is the route on almost every label. Subcutaneous injection (SC, into the fatty layer under the skin) is labeled in the US only for Xyosted, a prefilled autoinjector; using a cypionate or enanthate vial subcutaneously is off-label (outside the approved label), although a UK guideline accepts it for weekly doses. [2], [4], [5]
Who injects depends on the product: Aveed only in certified healthcare settings, Sustanon 250 and Testosterone Enantate by a doctor or nurse, and Nebido by a doctor (UK leaflets), and Xyosted by you after training. US vial labels do not say. Checked September 2026. [7], [14], [15], [16], [4]
How much to inject is your prescriber's decision and is covered in the TRT dosage guide; hands-on technique is best learned in person from a nurse, pharmacist or prescriber.
Injecting testosterone: the key numbers
This table shows what each product label and clinical guideline says about where and how testosterone is injected, and who gives it. The labels come first because they are the approved instructions. Checked September 2026.
| Source (version, year) | Route and site | How it is given | Who injects |
|---|---|---|---|
| US cypionate vial labels: Depo-Testosterone (Aug 2026) and generic cypionate (May 2026) | Intramuscular only, deep in the buttock (gluteal) muscle | Check for particles; warm to redissolve crystals | Not stated |
| US generic enanthate vial label (May 2026) | Intramuscular only, deep in the buttock muscle | Check for particles; warm to redissolve crystals; inject "slowly" | Not stated |
| Azmiro (cypionate 200 mg/mL, US label Jul 2025) | Intramuscular only, deep in the buttock muscle | Straight in at 90 degrees; prefilled syringe holds 200 mg, no needle included | Healthcare professional (prefilled syringe) |
| Xyosted (enanthate autoinjector, US label Apr 2026) | Subcutaneous, abdomen only, left or right side, not within 2 inches (5 cm) of the navel | Squeeze the skin, hold at 90 degrees for 10 seconds; do not rub | You or a caregiver, after training |
| Aveed (undecanoate 750 mg/3 mL, US label Mar 2026) | Upper outer buttock (gluteus medius); alternate sides | Aspirate for several seconds; inject over 60 to 90 seconds; stay 30 minutes | Certified healthcare setting only |
| Nebido (undecanoate 1,000 mg/4 mL, UK label Dec 2025) | Deep in the buttock muscle | Very slowly, over two minutes; watched during and right after | Doctor |
| Sustanon 250 (UK label and leaflet 2026; same wording in Australia) | Deep intramuscular: buttock, upper leg or upper arm (leaflet) | Very slowly; not for people allergic to peanut or soya | Doctor or nurse |
| Testosterone Enantate 250 mg/mL (UK label, Jan 2026) | Intramuscular | "Extremely slowly"; inject immediately after drawing up | Doctor or nurse (leaflet) |
| Primoteston Depot (Australia, Jan 2026) | Intramuscular | "Extremely slowly" | Not stated |
| Canadian cypionate monographs (Taro 2022, StériMax 2026) | Deep in the buttock muscle | Discard an opened vial 56 days after first use | Healthcare professional (StériMax) |
| Society for Endocrinology (UK, 2022) | Buttock muscle or upper thigh; or subcutaneous, 50–100 mg once a week | Inject slowly; subcutaneous comparable in blood levels, safety and tolerability | Supports subcutaneous self-injection |
| BSSM, British Society for Sexual Medicine (2023) | Intramuscular; subcutaneous enanthate is comparable | Oil-cough risk lower if given over several minutes; no long-term studies of subcutaneous "micro-dosing" | Subcutaneous can be self-injected |
| AUA, American Urological Association (2018, validity reconfirmed 2024) | Cypionate or enanthate, intramuscular or subcutaneous | First testosterone test no earlier than 3–4 injection cycles | Not stated |
| CUA, Canadian Urological Association (2021) | Into a large muscle, thigh or buttock | May need clinic visits | Not stated |
| Endocrine Society (2018) | Intramuscular | Lists site pain and coughing right after an injection | You or a clinician |
| Endocrine Society of Australia (2016) | Undecanoate: deep intramuscular | Not for men with bleeding disorders or low platelets | Clinician only |
| VA, US Department of Veterans Affairs (Jan 2026) | Intramuscular; subcutaneous only for specific cases | Possible bruising and redness at the site | Not stated |
[2], [1], [3], [4], [7], [8], [15], [17], [14], [18], [19], [16], [20], [21], [5], [22], [23], [6], [24], [25], [26]
US vial labels name only the buttock muscle; UK and Canadian guidelines also list the thigh; only Xyosted is labeled for subcutaneous injection; and every oil label that gives a speed asks for a slow injection. No randomized trial has compared injection sites for testosterone: one 1995 study compared pain and bleeding by site, not testosterone levels (see which site hurts less). Labels describe the sites used in the studies behind each approval; the Australian undecanoate label calls the buttock "the only site for which clinical experience has been obtained". Guidelines add sites and routes used in practice. [27], [5], [6]
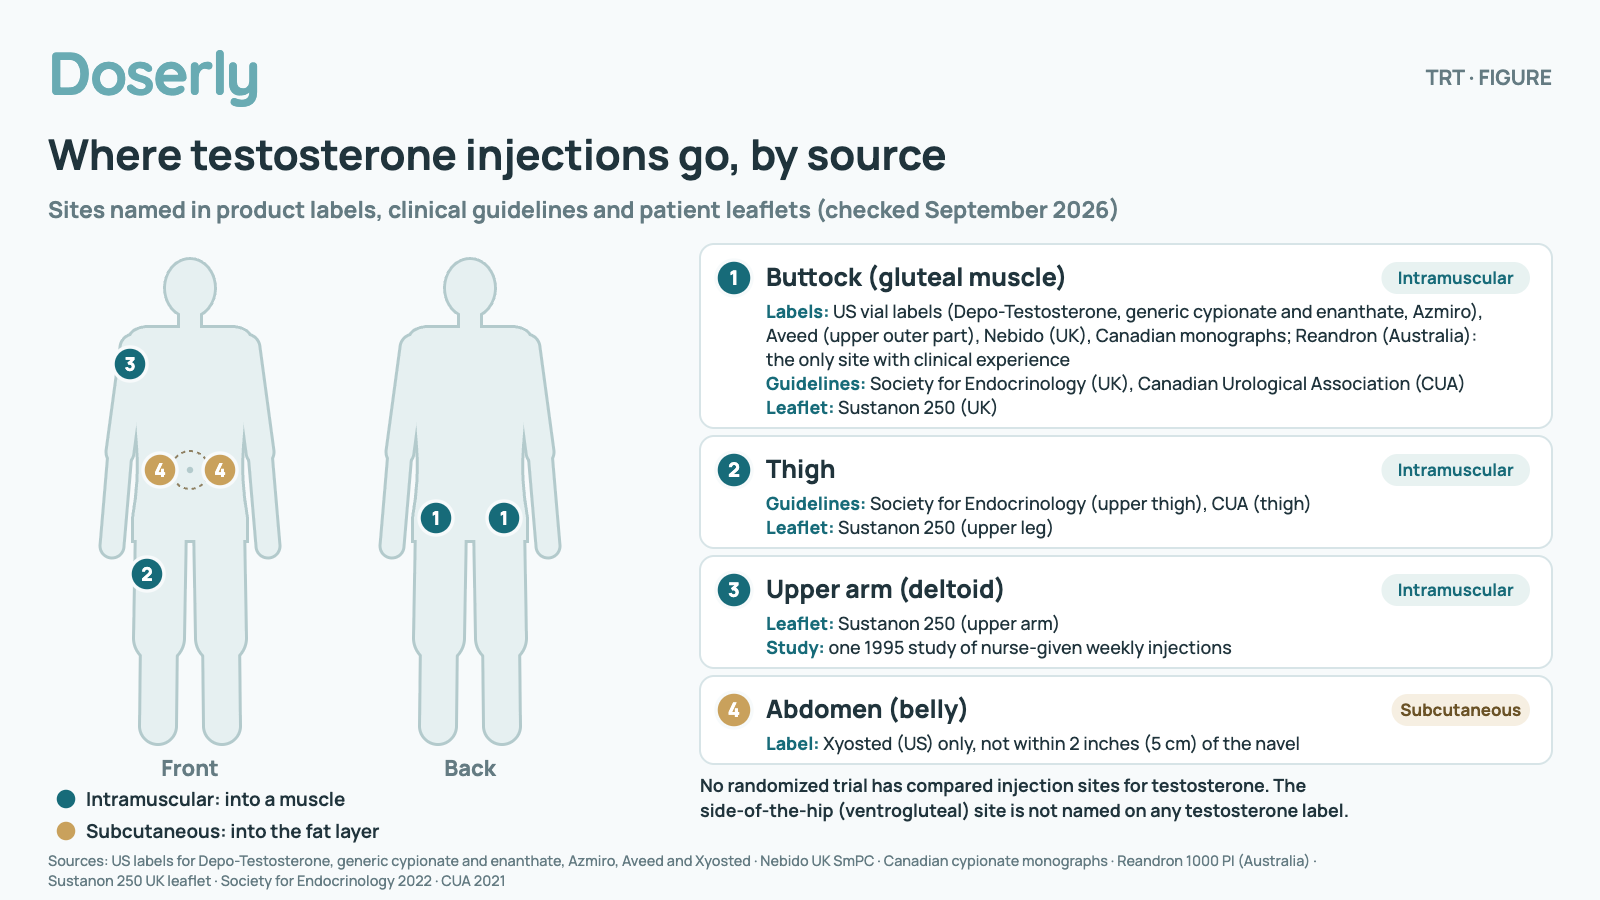
Where testosterone injections go, by source
Sites named in product labels, clinical guidelines and patient leaflets (checked September 2026).
Teal markers: intramuscular (into a muscle). Gold marker: subcutaneous (into the fat layer). The dashed ring marks the area around the navel to avoid.
- 1. Buttock (gluteal muscle) · intramuscular
- Labels: US vial labels (Depo-Testosterone, generic cypionate and enanthate, Azmiro), Aveed (upper outer part), Nebido (UK), Canadian monographs; Reandron (Australia): the only site with clinical experience
- Guidelines: Society for Endocrinology (UK), Canadian Urological Association (CUA)
- Leaflet: Sustanon 250 (UK)
- 2. Thigh · intramuscular
- Guidelines: Society for Endocrinology (upper thigh), CUA (thigh)
- Leaflet: Sustanon 250 (upper leg)
- 3. Upper arm (deltoid) · intramuscular
- Leaflet: Sustanon 250 (upper arm)
- Study: one 1995 study of nurse-given weekly injections
- 4. Abdomen (belly) · subcutaneous
- Label: Xyosted (US) only, not within 2 inches (5 cm) of the navel
No randomized trial has compared injection sites for testosterone. The side-of-the-hip (ventrogluteal) site is not named on any testosterone label.
How do milligrams, millilitres and syringe units fit together?
Syringe units measure volume, not testosterone. On a U-100 insulin syringe, 100 units equal 1 mL, so 1 unit is 0.01 mL. [11] To turn a dose into a volume, divide the dose by the vial's strength:
- 100 mg from a 200 mg/mL vial is 0.5 mL, or 50 units.
- 100 mg from a 100 mg/mL vial is 1 mL, or 100 units: twice the volume for the same dose. US cypionate comes in both strengths. [2]
- A split dose. If a prescriber splits 100 mg a week into two injections, each is 50 mg: 0.25 mL, or 25 units, at 200 mg/mL.
Mixing up milligrams, millilitres and units causes real errors: the US Food and Drug Administration (FDA) has reported patients drawing 50 units instead of 5 of a different injectable medicine. [28] The TRT dose calculator shows each step for your vial's strength, and the TRT dosage guide covers the doses themselves.
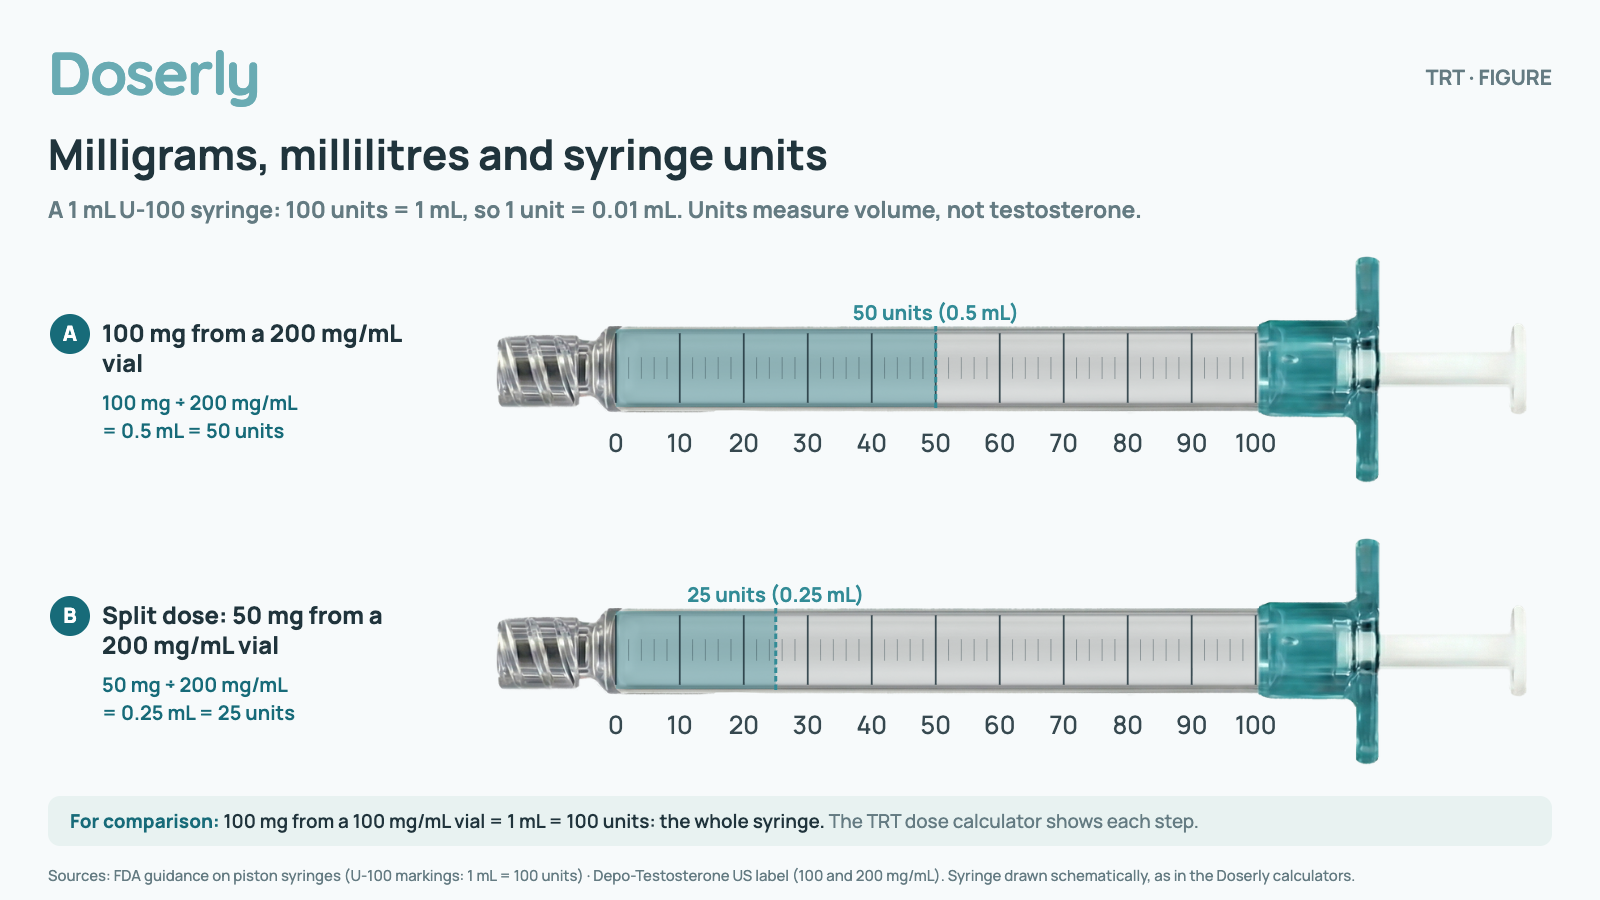
Milligrams, millilitres and syringe units
A 1 mL U-100 syringe: 100 units = 1 mL, so 1 unit = 0.01 mL. Units measure volume, not testosterone.
- A. 100 mg from a 200 mg/mL vial
- 100 mg ÷ 200 mg/mL = 0.5 mL = 50 units
- B. Split dose: 50 mg from a 200 mg/mL vial
- 50 mg ÷ 200 mg/mL = 0.25 mL = 25 units
100 mg from a 100 mg/mL vial = 1 mL = 100 units: the whole syringe. The TRT dose calculator shows each step.
Where these numbers come from
The label rows come from the current US labels for Depo-Testosterone (effective August 2026), generic testosterone cypionate and enanthate (May 2026), Azmiro (July 2025), Xyosted (April 2026) and Aveed (March 2026), the last two still printing a July 2025 revision date; the UK labels and patient leaflets for Nebido (December 2025), Sustanon 250 and Testosterone Enantate (2026); the Australian product information for Primoteston Depot, Sustanon '250' and Reandron 1000; and the Canadian Taro and StériMax cypionate monographs. [2], [29], [1], [3], [4], [7], [8], [17], [18], [19], [30], [27], [20], [21]
The guideline rows come from each body's current document: the Society for Endocrinology (2022), the BSSM (2023), the AUA (2018, validity reconfirmed 2024), the CUA (2021), the Endocrine Society (2018), the Endocrine Society of Australia (2016) and the VA (January 2026). [5], [22], [23], [6], [24], [25], [26]
The units example uses the FDA's description of U-100 insulin syringes (1 mL marked as 100 units). [11]
Not used: needle sizes presented as instructions (no testosterone label gives one for the injection itself), an injection time of "10 to 30 seconds" and a claim that the outer thigh is the most common self-injection site, which circulate online without a traceable source.
How does an injected oil depot work?
The oil slows everything down: the US enanthate label says esters in oil "are absorbed slowly from the lipid phase", so doses can be weeks apart. The body then removes the ester tail to free testosterone. [1]
How long a depot lasts depends mostly on the ester, not the route:
- Cypionate. The US label gives a half-life of about 8 days after intramuscular injection. [2]
- Enanthate. The UK label gives a blood half-life of 2 to 3 days in healthy men. The two figures were measured in different ways, so they are not a head-to-head comparison. [18]
- Time to peak. Median 71.7 hours (about 3 days) after 200 mg of intramuscular Azmiro, 11.9 hours for weekly subcutaneous Xyosted and 7 days for intramuscular Aveed. Different products and doses, so this does not show that one route is faster. [3], [4], [7]
Small studies that gave the same product both ways found similar overall exposure: with undecanoate, levels peaked later after subcutaneous injection (8.0 vs 3.3 days) but reached similar levels, and in 14 transgender men the total amount of testosterone in the blood per milligram injected was similar by route. [31], [32] The testosterone level visualizer shows how injection frequency changes the peaks and troughs.
What is in the vial, and does the oil matter?
The oil differs by product, which matters if you have an allergy:
| Product | Oil | Allergy note |
|---|---|---|
| Depo-Testosterone and US generic cypionate; Azmiro | Cottonseed oil | Azmiro has more benzyl alcohol (a preservative, 20 mg/mL instead of 9.45); its maker says it may be less prone to crystals |
| US generic enanthate | Sesame oil | |
| Xyosted | Sesame oil | Not for people allergic to sesame oil |
| Testosterone Enantate (UK), Nebido | Castor oil, with benzyl benzoate | One reported case of a severe allergic reaction was traced to benzyl benzoate, not the oil |
| Sustanon 250 | Arachis (peanut) oil | Not for people allergic to peanut or soya |
[2], [29], [33], [1], [4], [16], [15], [34], [17]
A vial can look cloudy if a wet needle or syringe was used; the US enanthate label says this does not affect potency. [1] Crystals are covered under storage.
Does cypionate or enanthate change how you inject?
Not on the US labels, which use the same buttock site and dose range for both. They differ in oil and ester, and injectable products are not substitutable milligram for milligram, so a switch is a prescriber's decision. See cypionate vs enanthate. [2], [1], [3]
What does the research show?
The research is thin: small studies comparing routes, product trials that counted local reactions, a few studies of the oil cough, and imaging studies of needle length done for vaccines and other medicines. [35], [9]

Is subcutaneous injection as good as intramuscular?
For blood levels, small studies suggest yes; for long-term safety, nobody knows. No randomized trial has compared the same cypionate or enanthate vial given subcutaneously and intramuscularly in men with hypogonadism.
- Guidelines split. The UK Society for Endocrinology says weekly subcutaneous cypionate or enanthate at 50–100 mg is comparable and supports self-management. The BSSM agrees for enanthate but notes no long-term studies of subcutaneous "micro-dosing" and little long-term data for cypionate. The VA keeps subcutaneous testosterone for specific cases only. [5], [22], [26]
- The largest comparison in men. In 234 men with hypogonadism, weekly intramuscular cypionate 100 mg and a weekly subcutaneous enanthate autoinjector 100 mg raised trough testosterone to similar levels: from 313.6 to 536.4 ng/dL (10.9 to 18.6 nmol/L) on cypionate and from 246.6 to 552.8 ng/dL (8.6 to 19.2 nmol/L) on the autoinjector. The autoinjector group had lower estradiol and hematocrit. But the ester, the device and the route all differed, and the men were not randomized, so the study cannot isolate the route. [36]
- Transgender men. In 63 transgender men on weekly subcutaneous cypionate or enanthate, all reached male-range levels, 9 had minor local reactions (4 of them small lumps that cleared in 1 to 2 days, and one a single skin infection that cleared without treatment), and all 22 who had used muscle injections before preferred subcutaneous ones (20 of them markedly). In 14 transgender men, subcutaneous injections scored lower for anxiety before injecting, pain during it and pain afterwards. [37], [32]
- A larger volume. With 4 mL of undecanoate, the picture reversed: subcutaneous injection hurt more 24 hours later, and 11 of 20 people preferred intramuscular, 6 subcutaneous and 3 had no preference. [31]
A 2022 review concluded that, with training, people can self-inject subcutaneously with less discomfort, but that data are limited and direct safety comparisons are still needed. [35] What people report after switching is mixed (community reports).
How often do injections hurt, bleed or bruise?
Often a little, rarely badly. The studies below measured different things in different products, so compare within each row, not across rows.
| Study | Product and who injected | What was counted | Result |
|---|---|---|---|
| Weekly enanthate (1995) | 26 healthy men in a male contraception study; 551 nurse-given injections of enanthate in castor oil into buttock, shoulder or thigh | Any complaint after each injection | No complaint after 389 (70.6%); minor effects, mostly pain or bleeding, after 162 (29.4%) |
| Long-acting undecanoate (2010) | 125 men, 168 nurse-given 4 mL buttock injections | Pain, asked about directly | Reported by 80% of men; worst straight away, lasted 1–2 days, back to normal by day 4 |
| Xyosted trials (label) | 283 men on weekly subcutaneous doses, up to a year | Injection-site reactions | 36 men (12.7%); none stopped treatment because of them |
| Xyosted 26-week study | 133 men | Bleeding, bruising and pain at the site | Bleeding in 6 (4.5%), bruising in 4 (3.0%); mild pain in 1 man across 965 assessed injections |
| Azmiro vs Depo-Testosterone (label) | 27 men, one 200 mg injection of each | Redness at the site | 7 of 27 men (26%) after each product, all mild; all were recorded in the first study period, so the comparison is uncertain |
| Aveed 84-week study (label) | 153 men on 750 mg in clinic | Pain at the site | 7 of 153 men (4.6%) |
[10], [38], [4], [39], [3], [33], [7]
In the undecanoate study, pain was worse in men whose earlier injection had hurt, and milder in older and heavier men; which experienced nurse gave the injection made little difference. [38] The US labels for cypionate list inflammation and pain at the injection site among side effects. [2]
Which site hurts less?
For testosterone, the only site comparison is one 1995 study: in 551 weekly enanthate injections, the buttock caused fewer complaints and less bleeding than the shoulder or thigh, but more often caused pain. [10]
Studies of other intramuscular medicines add detail. A 2023 review of 17 studies (1,429 people) found injections into the side of the hip (ventrogluteal) moderately less painful than the classic upper-outer-buttock site (dorsogluteal), with less bleeding and bruising and no more accidental subcutaneous injections. [40] Pressing on the injection site also reduced pain in small studies, though the studies varied a lot. [41]
Does the needle reach the muscle?
It depends on the site and the person. These imaging studies were done for vaccines and other medicines, not testosterone, and they model where a needle would reach rather than watching real injections:
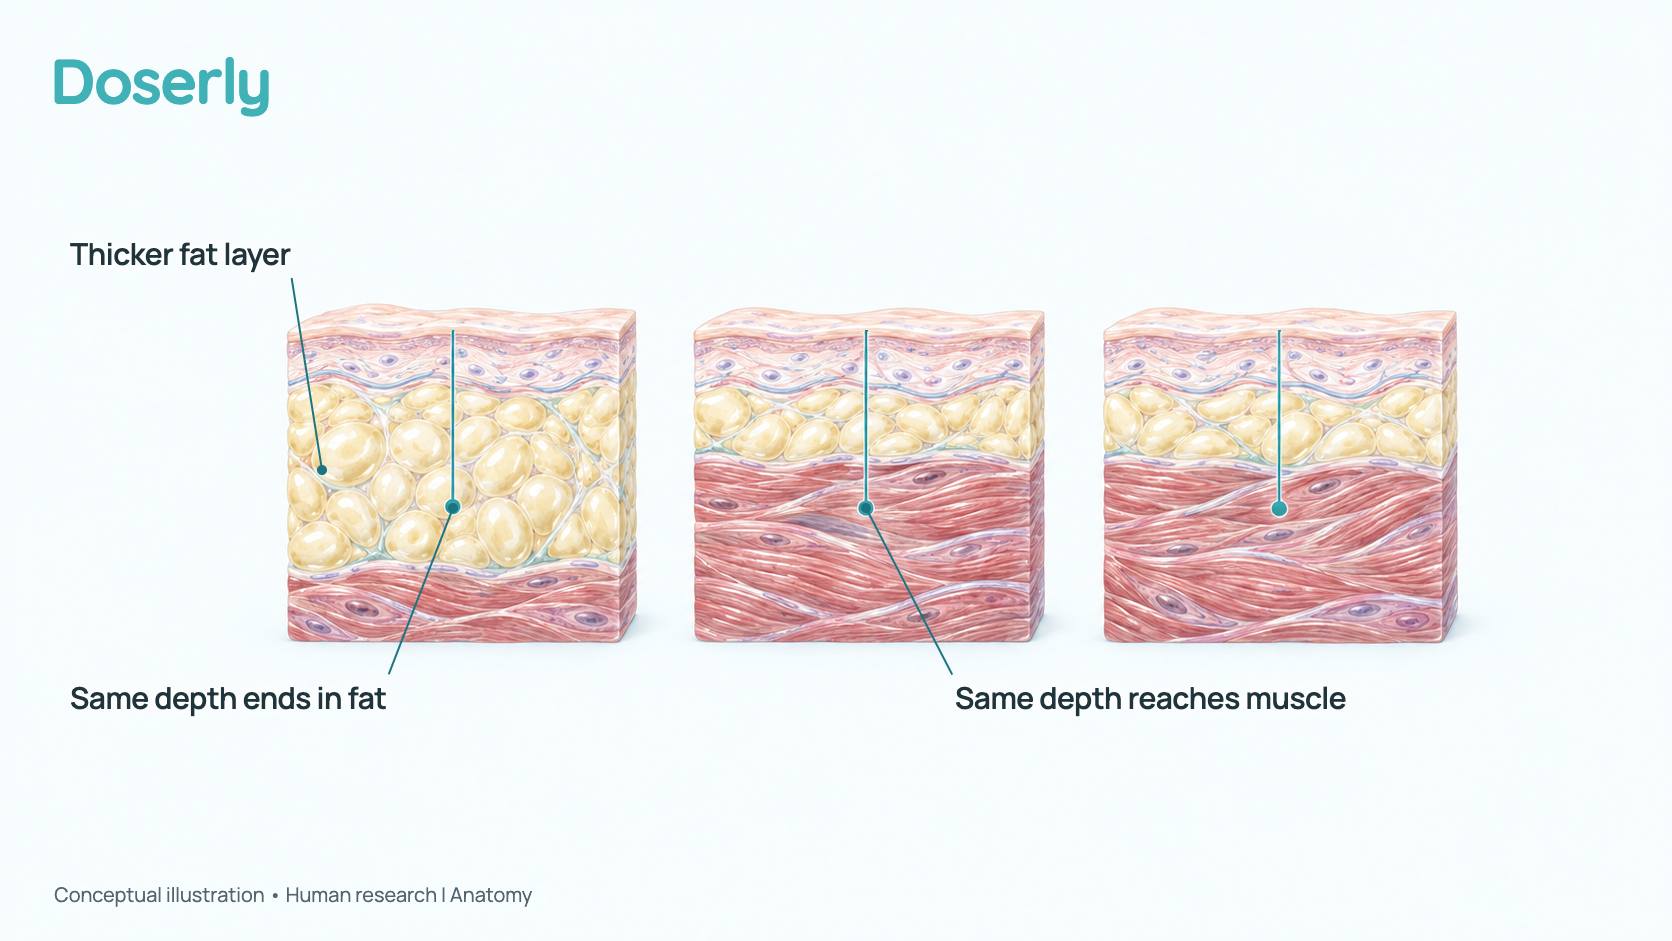
- Buttock. In CT scans of 150 men, the fat over the buttock muscle averaged 23.1 mm. A 37 mm needle would have missed the muscle in 21 of 150 men (14%) and in 81 of 148 women (54.7%). [9]
- Side of the hip. In an ultrasound study, 92% of men would have received a true intramuscular injection at the side-of-the-hip site located one standard way. [42]
- Upper arm. In PET/CT scans, a 1-inch (25 mm) needle was expected to reach the shoulder muscle in 207 of 210 men under 260 lb (118 kg), or 98.6%. A 1.5-inch (38 mm) needle was expected to reach it in 6 of only 8 men over 260 lb, so that figure is very uncertain. [43]
For small watery vaccines, the US Centers for Disease Control and Prevention (CDC) uses 1 to 1.5 inch (25–38 mm) needles for intramuscular shots in men of 70–118 kg (about 154–260 lb); oil depots are thicker and larger, so this is context, not a testosterone instruction. [44] No study has measured what happens to testosterone levels when an intended intramuscular injection lands in fat.

Does the needle reach the muscle? Three imaging studies
Each card is a separate study with its own measure, so the bars are not on one shared scale.
- Buttock (CT scans, 150 men)
- A 37 mm needle would miss the muscle in 14% of men (21 of 150)
- Women: 54.7% (81 of 148)
- Average fat over the muscle in men: 23.1 mm
- Side of the hip (Ultrasound, 28 men)
- 92% of men would get a true intramuscular injection at the site located one standard way
- The study does not say which needle length was assumed
- Upper arm (PET/CT scans, 218 men)
- A 1-inch (25 mm) needle reaches the shoulder muscle in 98.6% of men under 260 lb (207 of 210)
- Over 260 lb, a 1.5-inch (38 mm) needle: 6 of only 8 men
Modelled needle reach from studies of vaccines and other medicines, not testosterone injections.
Is injecting testosterone safe?
Usually, when it is done as the label describes. Most problems are minor pain, bleeding or bruising at the site. Serious local problems such as infection or nerve injury appear mainly as case reports, and the serious reaction that labels warn about, oil reaching the lungs, is best known with long-acting undecanoate. [10], [4], [45], [46], [7] This section covers the injection itself; the effects of testosterone on red blood cells, the heart and fertility are in the TRT side effects guide.
Why do some people cough right after an injection?
A sudden cough during or just after an oil injection is usually put down to pulmonary oil microembolism (POME): tiny droplets of the oil reaching the lungs. Labels list an urge to cough, coughing fits, shortness of breath, throat tightening, chest pain, dizziness and fainting. Most episodes on the Aveed label lasted a few minutes, but some lasted hours and needed emergency care. [7], [1]
How often it happens depends on the product and on how carefully people look:
| Source | Product | How it was counted | Result |
|---|---|---|---|
| Aveed label | Undecanoate, 18 trials | Cases reviewed against set criteria | 9 events in 8 of 3,556 men, plus 2 severe allergic reactions (anaphylaxis) |
| Nebido label (UK) | Undecanoate 1,000 mg | Frequency band | At least 1 in 10,000 and fewer than 1 in 1,000 injections |
| Australian clinic (2015) | Undecanoate, nurse-given | Nurses watched every injection | 56 of 3,022 injections (19 per 1,000); 40% began before the injection had finished |
| Aveed after approval (2020) | Undecanoate 750 mg | Voluntary reports, compared with doses shipped | 28 reports for 90,092 doses (below 0.1%); 13 of 17 with a known time settled within 30 minutes |
| Weekly enanthate (1995) | Enanthate, nurse-given | Complaints after each injection | Cough with faintness after 8 of 551 injections (1.5%), possibly oil-related |
| FDA review (2014) | All testosterone injections | Reports to FDA's adverse event database | 33 reports of severe oil reactions or anaphylaxis combined over 44 years; no rate can be calculated |
[7], [8], [47], [48], [10], [49]
Watching every injection finds far more mild episodes than waiting for reports, which is why the rates differ so much. The Endocrine Society says the cough is reported even more rarely after enanthate and cypionate than after undecanoate. [24], [1]
Labels respond with slow injection, watching the person during and after it and, for Aveed, 30 minutes in the clinic. The BSSM says the risk is lower if the injection takes several minutes, and in the Aveed safety review, technique or dosing problems were a possible factor in 3 of 4 cases that reached emergency care. [7], [15], [22], [48]
Chest pain, trouble breathing or fainting after an injection needs urgent medical help, and the prescriber should hear about any episode, because repeat episodes in the same men were more common than chance in the Australian series. [7], [47] A blood clot in the lung is a different problem, listed separately on the labels. [3]
Are lumps, bruises and bleeding normal?
A little bleeding or bruising is. The Xyosted instructions say slight bleeding after an injection is normal: hold a cotton ball or gauze on the spot for a few seconds and do not rub. The VA notes possible bruising and redness with intramuscular injections. [4], [26]
Small lumps after subcutaneous shots come up often in community reports. In one study of 63 transgender men on prescribed weekly subcutaneous testosterone, 4 reported small lumps that cleared in 1 to 2 days; no study has counted them in men on TRT. [37] Rarely, oil that stays in tissue forms an oil granuloma (a firm, walled-off lump): one case report describes painful lumps in both shoulders and a buttock found 9 years after a bodybuilder's non-prescribed oil injections. [50]
Can an injection get infected?
Yes, though no study has measured how often in men on TRT. In the study of 63 transgender men on subcutaneous injections, one had a single skin infection (cellulitis) that cleared without treatment. [37] A 2026 case report describes a 72-year-old man who developed a persistent thigh abscess (a pocket of pus) after a routine testosterone injection. It was caused by an unusual bacterium and needed surgical drainage and prolonged specialist antibiotics; his hospital stay was also complicated by breathing failure that needed intensive care. [45]
Guidance lowers the risk: a new sterile needle and syringe every time, and only healthy skin, not skin that is tender, bruised, red, hard or scarred. [51], [52], [4] A lump that keeps growing, feels hot, turns red, becomes more painful after the first day or two, or comes with a fever needs a clinician promptly.
Can you hit a nerve or a blood vessel?
It is possible, which is why labels describe the site so exactly. The Aveed label says to use the upper outer part of the buttock and avoid the superior gluteal arteries and the sciatic nerve, the large nerve running down the back of the leg. A review of injection injuries found that sciatic nerve damage from buttock injections is avoidable but still happens worldwide; most reported cases were in children, and the review covered injections in general, not testosterone. [7], [46] The US labels also say to avoid injecting into a vein, and cypionate is "not for intravenous use". [1], [2]
Who should be especially cautious?
- Men with a bleeding disorder, low platelets, or on blood thinners. The Endocrine Society of Australia says deep intramuscular undecanoate is unsuitable with bleeding disorders or low platelets. In one clinic, 269 undecanoate injections in men on blood thinners caused no bleeding lump. US labels note that testosterone can increase the effect of warfarin-type blood thinners. [25], [47], [2]
- People with oil or ingredient allergies. Sustanon 250 is not for people allergic to peanut or soya, and Xyosted is not for people allergic to sesame oil. [17], [4]
- Anyone who has had a cough or breathing reaction after an injection, and very lean or heavier men, whose needle reach differs (the research). [47], [9]
- People with diabetes. US labels say testosterone may lower blood sugar and insulin needs. [2]
- Drug-tested athletes. Testosterone is prohibited in sport at all times. [13]
- Under-18s. Testosterone for teenagers belongs only in specialist care.
- Women. This guide is written for men. Testosterone for women uses different doses and products; see testosterone therapy for women.
Can testosterone be mixed with other injections?
No testosterone label describes mixing it with another medicine in one syringe; UK labels say to inject the oil immediately after drawing it up. [18], [8] Ask a pharmacist first. hCG, which some men use alongside testosterone, is covered in the hCG guide. Checked September 2026.
Is testosterone legal, and is it allowed in sport?
Checked September 2026. Rules differ by country and change often.
- United States. Testosterone and its esters are Schedule III controlled substances, prescription only. No proposal to change that has been published. [12]
- United Kingdom. Testosterone is a Class C controlled drug. [53]
- Canada. Testosterone is a Schedule IV controlled substance. [54]
- Australia. Testosterone is a Schedule 4 prescription-only medicine. [55]
- Sport. The World Anti-Doping Agency (WADA) prohibits testosterone at all times, and its 2027 list, published in September 2026, keeps the ban. [13], [56]
What do labels and guidelines say about technique?
The labels describe the same basic steps: check the liquid, use a new sterile needle and syringe, inject slowly into the named site, rotate sides and put used sharps straight into a proper container. This is a summary, not a substitute for being shown in person. [2], [7], [4]
| Step | What labels and guidelines say | Source |
|---|---|---|
| Check the liquid | Clear, with no particles; crystals can form below the storage temperature | US cypionate label; UK enanthate leaflet |
| Redissolve crystals | Warm and shake (cypionate) or roll between the palms (enanthate); bring Nebido to room temperature if stored cold | US labels; Nebido label |
| Use a new needle and syringe | Single use; never reuse either | CDC; NHS sharps leaflet |
| Draw up | Aveed: draw with an 18-gauge needle, then fit a new needle to inject | Aveed label |
| Insert | Straight in at 90 degrees (Aveed, Azmiro, Xyosted) | US labels |
| Aspirate | Aveed only: pull back for several seconds; if blood appears, discard and start again | Aveed label |
| Inject | "Slowly" (US enanthate), 60 to 90 seconds (Aveed), over two minutes (Nebido); the longest times are for the largest volumes | Labels |
| Afterwards | Hold gauze on any bleeding for a few seconds; do not rub (Xyosted) | Xyosted instructions |
| Rotate | Alternate sides (Aveed, Xyosted) | Labels |
| Dispose | Straight into an approved sharps container | FDA; labels |
[2], [16], [1], [8], [51], [52], [7], [3], [4], [18], [57]
Should you pull back on the plunger before injecting?
The sources disagree, and the answer depends on the product. The Aveed label tells clinicians to aspirate (pull back on the plunger) for several seconds and to start again with a fresh dose if blood appears. [7] A 2025 review of 6 randomized trials (693 people, mostly children and vaccines) found that aspirating made injections more painful and slower, with no serious complications reported when it was skipped; its authors said the technique should depend on the type of medicine. CDC vaccine guidance also notes that aspiration can increase pain. [58], [44] For Aveed, the label applies. Other testosterone labels do not mention aspiration, so ask the nurse or pharmacist who trains you.
Do warming the oil, changing the needle or pressing on the skin help?
Pressing on the site may help. In small studies of other intramuscular medicines, pressing on the injection site reduced pain, though the results varied a lot and some studies were biased; warming the liquid did not help, a fresh needle after drawing up gave conflicting results, and there was not enough evidence for the "Z-track" technique (pulling the skin sideways first). Labels mention warming only to redissolve crystals. [2], [41] Aveed's label gives the reason for its separate 18-gauge drawing needle: it makes drawing the medicine out of the vial easier. [7]
How should you rotate injection sites?
Change sites so the same spot is not used again and again. Aveed alternates left and right buttock; Xyosted allows either side of the abdomen, away from the navel and any damaged skin. [7], [4] In the weekly enanthate study, the side of the body made no difference to side effects. [10] A simple record of date, site, side and any reaction shows which spots were used last and which cause trouble.
Sites, needles, syringes and supplies: practical questions
Where can you inject testosterone: buttock, thigh, shoulder or belly?
It depends on the product. US vial labels name only the buttock muscle; the UK Society for Endocrinology adds the upper thigh, the CUA the thigh, and the UK Sustanon leaflet the upper arm. The only belly site on a label is Xyosted's, given subcutaneously. [2], [7], [5], [6], [14], [4]
The shoulder (deltoid) appears in the old nurse-given enanthate study, not on US labels. The side of the hip (ventrogluteal) is not named on any testosterone label, but studies of other medicines found it less painful than the classic buttock site. [10], [40] If you want to use a site your label does not name, agree it with your prescriber first.
What needle size is used for testosterone injections?
The labels cited here give no needle size for the injection itself. Aveed names only the 18-gauge needle used to draw the oil up, and the Azmiro prefilled syringe comes without a needle ("obtain suitable needle separately"). [7], [3] Outside the labels, a UK administration guide for long-acting undecanoate, approved by the UK medicines regulator, suggests a 20-, 21- or 22-gauge needle chosen for the person's fat and muscle. [59] Needles are described by gauge, where a higher number means a thinner needle, and by length.
The length that reaches muscle depends on the site and the person (needle reach), so your prescriber or pharmacist supplies needles for your product, site and build. [9], [43]
Can you use an insulin syringe for testosterone?
For measuring volume, the arithmetic works: a U-100 insulin syringe is marked in units, with 1 mL shown as 100 units and 0.5 mL as 50 units. [11] The practical limits are the oil and the needle: in community reports, very fine insulin-syringe needles drew thick oil slowly, while others used them for subcutaneous or shoulder injections. Whether one suits your product and route is a question for your prescriber or pharmacist. See how the units work.
Can you pre-fill syringes ahead of time?
No label or official source gives a safe time for testosterone drawn into ordinary syringes ahead of use. The UK enanthate and Nebido labels say to inject immediately after drawing up, and the CDC advises preparing injections as close as possible to the time they are given. [18], [8], [51] Some people report oil appearing to soak into the rubber plunger of pre-filled syringes, but that is an observation, not a study (community reports).
How should testosterone be stored, and why can crystals form?
It depends on the product. The US cypionate and enanthate vials are kept at room temperature, and cypionate also away from light; UK Nebido has no special storage conditions. Cypionate and enanthate can form crystals when they get colder than the labeled range; warming and shaking or rolling the vial should redissolve them. [2], [1] The leaflet in your box is the final word for your product.
| Product | Storage | Notes |
|---|---|---|
| Depo-Testosterone and US generic cypionate | 20–25 °C; protect from light | Warm and shake to redissolve crystals |
| US generic enanthate | 20–25 °C | Warm and roll between the palms to redissolve crystals |
| Azmiro | 15–25 °C (short trips to 2–30 °C allowed), in the carton | Single use |
| Xyosted | 20–25 °C; do not refrigerate or freeze | Keep in the carton |
| Aveed | 25 °C (15–30 °C allowed), in the carton | Given in clinic |
| Sustanon 250 (UK) | Below 30 °C; do not refrigerate or freeze | Keep in the original pack |
| Nebido (UK) | No special storage conditions | Use immediately after opening |
[2], [29], [1], [3], [4], [7], [17], [8]
How long does an opened vial last?
The US Depo-Testosterone and generic enanthate labels cited here give no in-use period for an opened multi-dose vial, so follow the instructions for the vial you receive. US guidance for healthcare settings says to date an opened multi-dose vial and discard it within 28 days unless the manufacturer states another date; Canadian cypionate monographs say to discard it 56 days after first use. The printed expiry date applies to an unopened vial. [51], [20], [21] The testosterone cypionate guide covers storage in more detail.
Blood came out after the injection. Did I lose my dose?
Probably not much, though no study has measured it. The Xyosted instructions treat slight bleeding as normal. [4] Doses can also be lost through the device or technique: in a usability study of a Xyosted-type autoinjector, done with observers watching, 99 of 123 attempted injections (80.5%) delivered a full dose, and the most common error was not holding it against the skin long enough (at least 8 seconds). [60] That is why the Xyosted instructions say to hold it down for a full 10 seconds. [4]
How do you get rid of used needles?
Put each used needle and syringe straight into a sharps container; never put loose needles in household trash or recycling, and never flush them. [57]
- United States. Use an FDA-cleared sharps container or a heavy-duty plastic household container with a tight, puncture-resistant lid, such as a laundry detergent bottle. When it is about three-quarters full, follow local rules: drop-off sites, mail-back programs or special pick-up. [57], [61], [4]
- United Kingdom. Dispose of the needle and syringe together as one unit, do not fill the bin above its fill line, and do not use drink cans or bottles. [52]
- Canada. The cypionate monographs say to put used needles and syringes straight into a designated safety box or puncture-proof container. [20]
- Australia. NSW Health advises a puncture-proof container taken to a public sharps bin or a participating pharmacy, medical centre or hospital. [62]
Can you travel with injectable testosterone?
Yes, with preparation. In the US, the Transportation Security Administration allows unused syringes when they are carried with injectable medication, and used ones must go in a sharps or hard-sided container. Rules for controlled medicines differ by country. See traveling with testosterone. Checked September 2026. [63]
What if needles make you anxious?
There are options to discuss. In 14 transgender men, subcutaneous injections caused less anxiety beforehand than intramuscular ones; Xyosted is an autoinjector made for self-injection after training; and clinic-given injections remain an option (for Aveed and several UK products, the only one). [32], [4], [7], [14]
What do people report about injecting testosterone?
Public forums are full of men comparing sites, needles and routes, and asking whether a lump or a sore spot is normal. The accounts below come from public Reddit threads posted between September 2025 and September 2026, read with their replies. They show what people experience, not how often it happens, and several involve products that did not come from a pharmacy.
What happens when people switch from intramuscular to subcutaneous?
Results point both ways, and most switches changed something else too. One man moved to 30 mg of subcutaneous enanthate in the belly every other day and, two weeks later, described better sleep, erections and energy, with no lumps. [64] Another found injections easier after moving from weekly muscle shots to twice-weekly subcutaneous shots at the same 100 mg a week, but his mood, libido and erections got worse. [65]
Lab results rarely isolate the route. One man's testosterone fell after the switch, but his dose had also dropped. [66] Another recorded 1,151 ng/dL (about 40 nmol/L) on every-other-day muscle shots and 667 ng/dL (about 23 nmol/L) on daily subcutaneous shots, while his hCG timing, syringes, weight and sleep apnea treatment also changed. [67] Hematocrit fell for one man after he moved to three belly injections a week, alongside about 25 lb of weight loss. Another man started daily subcutaneous shots to bring his hematocrit down; about nine weeks later it was 57.4%. [68], [69]
What do people say about lumps, pain and the oil?
Lumps after subcutaneous shots come up often in these accounts. One man's red, itchy lumps began in his sixth week of twice-weekly shots and lasted longer each time, until he moved back to muscle; another had lumps lasting about a week whatever the needle size; others describe small lumps that clear within hours. [70], [71], [72]
Several stories blame the oil or a new vial. Itchy skin from subcutaneous cypionate in grapeseed oil settled for one man after he switched to muscle injections at the side of the hip; large lumps from a non-pharmacy product in MCT oil eased with an antihistamine and did not return with a different product. [73], [74] Pain after buttock injections from a new 400 mg/mL enanthate vial was easing by day eight, and severe thigh pain from a new non-pharmacy supply did not recur. [75], [76] None of these accounts can show what caused the reaction.
Which sites and needles do people find easier?
Preferences differ widely. One man found a 27-gauge, 13 mm needle in the shoulder painless after nine months of 25-gauge, 25 mm needles in the buttock or leg; another's first warmed shoulder injection was painless after weeks of uncomfortable belly shots. [77], [78] Others went the opposite way, feeling best on deeper thigh and buttock injections with 1-inch and 1.5-inch needles. [79] A wife describes her husband's first self-injection, low on the thigh near the knee, followed by two weeks of swelling and difficulty walking. [80]
What goes wrong with needles, syringes and volumes?
- Oil through fine needles. A 31-gauge insulin syringe drew the oil too slowly for one man; another found a 0.5 mL shoulder injection through a 27-gauge needle on a 3 mL syringe hard to push, ending in bleeding. [81], [82]
- One needle for everything. Drawing up and injecting with the same small needle left one man struggling to pierce the skin; later injections with a fresh 27-gauge insulin syringe caused no pain. [83]
- Where the dose went. Men ask whether a half-inch needle at the side of the hip reaches muscle, and one found that a pen dripping after removal may have delivered incomplete doses for two weeks. [84], [85]
- Units and millilitres. Replies pointed out that one man's 0.12 mL a day from a 200 mg/mL vial was 24 mg a day, about twice the weekly dose he thought he was taking. [86]
- Pre-filled syringes. Pre-filled insulin syringes of an MCT-oil product appeared to lose volume within hours as the plunger seal swelled. [87]
When do people get reactions checked, and what about needle fear?
The threads that drew the most urgent replies involved warmth, spreading swelling or a growing lump: warm, itchy thigh swelling after a reused needle, and a prominent bulge after alternating between only two sites. [88], [89] Fear of needles often eases: one man was frightened by the large drawing needle before his first belly injection, which turned out to be easy with a smaller needle, while another found one-inch needles so distressing that he tried inserting them only partway. [90], [91]
How can you judge an injection story?
Ask: Was the product from a pharmacy, and in which oil and strength? Was it injected into muscle or fat, where, and with what needle? Was the dose written in milligrams, not just units? What else changed at the same time? When was blood drawn relative to the last injection? And what happened over the following months?
These selected discussions show what people experience and the questions research has not answered. They are not a survey of all men who inject testosterone, a success rate or a substitute for the studies above.
What should you track?
The site and side of each injection, and any reaction, alongside the blood tests your prescriber orders. Use this summary to prepare questions for your prescriber; it is not a personal plan.
| What to note | Why it matters | What labels and guidelines say | Tracking category |
|---|---|---|---|
| Date, dose, volume and site of each injection | Makes rotation easy and shows what you took before each blood test | Aveed: alternate buttocks; Xyosted: rotate sides of the abdomen | Other (injection log) |
| Pain, bruising, lumps or redness | Shows which sites or products cause trouble | Labels list site pain and reactions; slight bleeding is normal | Side Effect Burden; Pain Management |
| Any cough, breathlessness or dizziness during or after an injection | May be oil reaching the lungs | Labels: watch during and after; tell the prescriber | Side Effect Burden |
| Testosterone level, drawn at the time your guideline specifies | Injection timing changes the result | AUA: first test no earlier than 3–4 injection cycles; Xyosted: trough after 6 weeks | Blood work |
| Hematocrit | Intramuscular cypionate and enanthate raised hematocrit more than patches in pooled trials | Xyosted: about every 3 months; see the hematocrit guide | Blood work |
[7], [4], [2], [47], [23], [92]
The TRT blood work guide explains when to draw each test, and the hematocrit guide covers the red-cell numbers. Noting the date of any change of route, site or needle makes later results easier to read.
Common questions about injecting testosterone
Is it better to inject testosterone in the glute, the thigh or the shoulder?
US vial labels name only the buttock (glute) muscle; UK and Canadian guidelines add the thigh, and the UK Sustanon leaflet the upper arm. No randomized trial has compared sites, so none has been shown to work better. [2], [5], [6], [14], [10] See the key numbers.
Can you inject testosterone subcutaneously instead of intramuscularly?
Only Xyosted is labeled for it in the US; using a vial subcutaneously is off-label. A UK guideline accepts weekly subcutaneous doses of 50–100 mg, and small studies found similar blood levels. One small randomized crossover study compared the two routes for undecanoate in 20 people, 11 of them men with hypogonadism; no randomized trial has compared them for a cypionate or enanthate vial in these men. Discuss any change with your prescriber. [4], [5], [37], [35], [31] See the research.
What size needle do you use for testosterone?
The labels cited here give none for the injection itself, though a UK administration guide for undecanoate suggests 20 to 22 gauge. The length needed depends on the site and body fat: a 37 mm needle would miss the buttock muscle in about 1 in 7 men. Your prescriber or pharmacist supplies suitable needles. [7], [59], [9] See needle size.
How many units is 100 mg of testosterone?
At 200 mg/mL, 100 mg is 0.5 mL, or 50 units on a U-100 insulin syringe. At 100 mg/mL, it is 1 mL, or 100 units. Units measure volume, so the answer depends on your vial's strength. [11], [2] The TRT dose calculator shows each step. See how the units work.
Are testosterone injections painful?
Usually only mildly. In 551 nurse-given weekly injections, 70.6% caused no complaint, and in the Xyosted 52-week study more than 95% of men reported no injection-related pain. Large undecanoate injections hurt more often, for 1–2 days. [10], [93], [38] See how often injections hurt.
Is there a risk of oil embolism from testosterone injections?
Yes, but serious episodes are rare. It is best known with long-acting undecanoate, and the Endocrine Society says it is reported even more rarely after enanthate and cypionate. A sudden cough or breathlessness during or just after an injection can mean oil reached the lungs; most episodes pass within minutes, but chest pain, trouble breathing or fainting needs urgent help. [7], [24], [22] See the cough after an injection.
Do injections raise hematocrit more than other forms?
Not clearly, except compared with patches. In a combined analysis of 29 placebo-controlled trials, cypionate or enanthate injections raised hematocrit by about 4.0 points, against 3.0 for gels and 1.4 for patches. Oral undecanoate capsules raised it by 4.3 points and long-acting undecanoate injections by 1.6. Only the difference from patches was clear; the other differences could have been chance. Whether the injection route matters is unsettled. [92], [36] The hematocrit guide has the full picture.
Glossary
Plain explanations of the medical, injection and research terms used in this guide. Underlined terms in the text link here.
- Anaphylaxis
- A severe, whole-body allergic reaction that can affect breathing and blood pressure. It needs emergency treatment.
- Aspiration
- Pulling back on the plunger after the needle is in, to check that no blood comes into the syringe. The Aveed label asks for it; vaccine guidance does not.
- Autoinjector
- A prefilled, spring-loaded device that inserts the needle and delivers a set dose when pressed against the skin. Xyosted is one.
- Controlled trial
- A study that compares people who receive a treatment with a similar group who do not, often receiving a placebo instead. Randomly assigning people to each group makes the comparison fairer.
- Depot
- A pool of medicine left in the body, such as oil in a muscle, that releases the drug slowly over days or weeks.
- Dorsogluteal site
- The classic injection site in the upper outer part of the buttock. The Aveed label uses this area (the gluteus medius muscle).
- Ester
- A chemical tail joined to testosterone that makes it dissolve in oil and release slowly after injection. The body removes the tail to free testosterone. Cypionate, enanthate and undecanoate are esters.
- Estradiol
- The main form of estrogen. In men it is made mostly from testosterone, so it rises when testosterone rises.
- Needle gauge
- A number describing how thick a needle is. A higher gauge means a thinner needle: a 27-gauge needle is thinner than an 18-gauge one.
- Gluteal
- Of the buttock muscles. US testosterone vial labels say to inject deep into the gluteal muscle.
- Half-life
- The time it takes for the level of a substance in the blood to fall by half. For injected testosterone esters it mostly reflects how slowly the oil depot releases the drug.
- Hematocrit
- The share of the blood made up of red blood cells. Testosterone raises it, which is why it is checked on treatment.
- Intramuscular (IM)
- Injected into a muscle. Most testosterone cypionate and enanthate is given this way.
- Product label (prescribing information)
- The official document approved by a medicines regulator for a product, describing its approved uses, doses, how to give it and warnings. In the UK it is called the summary of product characteristics.
- Meta-analysis and systematic review
- A systematic review gathers all studies on a question in a planned way. A meta-analysis combines their results statistically.
- Off-label
- Used in a way the product label does not describe, such as a different route or site. Prescribers may do this, but the label's studies do not cover it.
- Oil granuloma (oleoma)
- A firm lump that forms when the body walls off injected oil that stays in the tissue. It is rare and can appear long after the injections.
- Pharmacokinetics
- How the body absorbs, moves, breaks down and removes a substance.
- Placebo
- A dummy treatment with no active ingredient, used as a comparison in studies.
- Pulmonary oil microembolism (POME)
- Tiny droplets of injected oil reaching the lungs, causing a sudden cough, breathlessness or dizziness during or soon after an injection. It is rare, and best known with long-acting undecanoate.
- Sharps container
- A puncture-resistant container with a tight lid for used needles and syringes. Pharmacies sell approved ones; some sturdy household containers can stand in.
- Subcutaneous (SC)
- Injected into the fatty layer just under the skin. Xyosted is labeled this way; using a testosterone vial under the skin is off-label.
- Syringe units
- Markings on an insulin syringe that measure volume. On a U-100 syringe, 100 units equal 1 mL, so 0.5 mL is 50 units.
- Trough level
- The lowest level of a drug in the blood, measured just before the next dose.
- TRT (testosterone replacement therapy)
- Prescribed testosterone, by injection, gel or other forms, for men with low testosterone.
- U-100 syringe
- An insulin syringe marked for insulin at 100 units per mL. Its markings can be read as volume: each unit is 0.01 mL.
- Ventrogluteal site
- An injection site on the side of the hip, into the gluteus medius and minimus muscles. Studies of other medicines found it less painful than the classic buttock site.
- WADA
- The World Anti-Doping Agency, which publishes the list of substances banned in sport. Testosterone is prohibited at all times.
How this guide was researched
This guide is built from a thorough review of the sources cited throughout it: product labels and patient leaflets from the US, UK, Canada and Australia, clinical guidelines, published studies, and official guidance on injection safety and sharps disposal. We also reviewed public online forums where men describe their own experiences of injecting testosterone.
The guide cites 93 sources, including 17 studies in people, 17 product labels and patient leaflets, 7 clinical guidelines and position statements, and 28 public community discussions. Each type of source answers a different question. Labels and guidelines show what clinicians are told to do. Studies show what was measured. Personal accounts show what individual people experienced. Every numbered citation links to its entry below, labeled by source type.
How this guide was made
Research and drafting were AI-assisted. Every cited source was checked against the original, and the guide was reviewed and edited by Doserly before publication. It has not had an independent clinical review, and Doserly does not currently have medical reviewers. Doserly makes a medication and health-tracking app and runs Doserly Academy, both of which are promoted in this guide. Read our editorial policy for how guides are researched, updated and corrected.
This guide is for educational purposes. It summarizes what the reviewed sources report so the research is easier to understand; it is not medical advice. For a deeper dive, or to check any point for yourself, go straight to the cited sources.
Explore the sources
These are the documents cited in this guide. Labels, guidelines, studies, official guidance and personal accounts answer different questions. A source being listed does not mean every statement on its page is endorsed.
Showing 93 sources
- 01
Testosterone enanthate injection USP 200 mg/mL (generic, Hikma) prescribing information ↗
Product label (US)
Full label reviewed.
Detail: Generic enanthate in sesame oil: esters in oil are absorbed slowly; inject slowly and deep into the gluteal muscle, avoiding a vein; rare reports of cough and breathing distress right after injection; a wet needle can make the solution cloudy without affecting potency; warming and rotating the vial redissolves crystals.
- 02
Depo-Testosterone (testosterone cypionate) 100 and 200 mg/mL prescribing information ↗
Product label (US)
Full label reviewed.
Detail: Depo-Testosterone: intramuscular only, deep in the gluteal muscle, not into a vein; check for particles; warming and shaking redissolves crystals; 100 and 200 mg/mL in cottonseed oil; store at 20–25 °C, protected from light; lists pain and inflammation at the injection site; may increase the effect of oral anticoagulants and lower insulin needs.
- 03
Azmiro (testosterone cypionate) 200 mg/mL single-dose vial and prefilled syringe prescribing information ↗
Product label (US)
Full label reviewed.
Detail: Azmiro: deep gluteal intramuscular only; the prefilled syringe holds a 200 mg dose, is given by a healthcare professional and comes without a needle; insert at 90 degrees; injection-site redness in 26%, all mild; median time to peak 71.7 hours; injectable testosterone products are not substitutable milligram for milligram.
- 04
Xyosted (testosterone enanthate) subcutaneous autoinjector 50, 75, 100 mg/0.5 mL prescribing information ↗
Product label (US)
Full label and instructions for use reviewed.
Detail: Xyosted: subcutaneous in the abdomen only, not within 2 inches of the navel, avoiding damaged skin; squeeze the skin, hold at 90 degrees for 10 seconds; slight bleeding is normal, do not rub; injection-site reactions in 36 of 283 men (12.7%), none stopped; contains sesame oil; median time to peak 11.9 hours; store at 20–25 °C; sharps disposal steps.
- 05
Society for Endocrinology guidelines for testosterone replacement therapy in male hypogonadism ↗
Clinical guideline (UK)
Full text reviewed.
Detail: Oily preparation injected slowly into the gluteal muscle or upper thigh; cypionate or enanthate 50–100 mg subcutaneously once a week has comparable blood levels, safety and tolerability and supports self-management.
- 06
Canadian Urological Association guideline on testosterone deficiency in men: Evidence-based Q&A ↗
Clinical guideline (Canada)
Full text reviewed.
Detail: Injections are typically given into a large muscle, including the thigh or gluteal, and may require clinic visits.
- 07
Aveed (testosterone undecanoate) 750 mg/3 mL intramuscular injection prescribing information ↗
Product label (US)
Full label reviewed.
Detail: Aveed: gluteus medius in the upper outer buttock, avoiding the superior gluteal arteries and sciatic nerve; alternate sides; 18-gauge needle to draw, a new needle to inject; aspirate; inject over 60 to 90 seconds; 30-minute observation in a certified setting; 9 oil-cough events in 8 of 3,556 men and 2 anaphylaxis in 18 trials; injection-site pain 4.6%; median time to peak 7 days.
- 08
Nebido 1000 mg/4 ml solution for injection (testosterone undecanoate) SmPC ↗
Product information (UK)
Full SmPC reviewed.
Detail: Nebido: deep gluteal intramuscular, injected very slowly (over two minutes); oil reaching the lungs in at least 1 in 10,000 and fewer than 1 in 1,000 injections; bring to room or body temperature if stored cold; no special storage conditions; use immediately after opening.
- 09
Computed tomographic measurement of gluteal subcutaneous fat thickness in reference to failure of gluteal intramuscular injections ↗
Imaging study
Original abstract reviewed.
Detail: CT scans of 298 people: gluteal fat averaged 23.1 mm in men; a 37 mm needle would miss the muscle in 21 of 150 men (14%) and 81 of 148 women (54.7%).
- 10
Tolerability of intramuscular injections of testosterone ester in oil vehicle ↗
Human study
Original abstract reviewed.
Detail: 551 nurse-given weekly enanthate injections (castor oil) in 26 healthy men in a male contraception study: no complaint after 70.6%, minor effects (mostly pain or bleeding) after 29.4%; the buttock caused fewer complaints but more often pain than shoulder or thigh; cough with faintness after 8 injections (1.5%).
- 11
Guidance on the Content of Premarket Notification [510(K)] Submissions for Piston Syringes ↗
Regulator guidance (US)
Official page reviewed.
Detail: Standard insulin syringes are 1.0 mL (100 units) and 0.5 mL (50 units), marked for U-100 insulin.
- 12
21 CFR 1308.13(f) Schedule III: anabolic steroids ↗
Regulation (US)
Official text reviewed.
Detail: Lists anabolic steroids, including testosterone and its esters, in Schedule III.
- 13
World Anti-Doping Code International Standard: Prohibited List 2026 ↗
Anti-doping list
Full list reviewed.
Detail: Testosterone is prohibited at all times (S1.1).
- 14
Sustanon 250, 250 mg/ml solution for injection: Patient Information Leaflet (UK) ↗
Patient leaflet (UK)
Full leaflet reviewed.
Detail: Sustanon 250: given only by a doctor or nurse, deep into a muscle such as the buttock, upper leg or upper arm; not with peanut or soya allergy; oil-cough reaction up to 1 in 1,000; observe during and after each injection.
- 15
Nebido 1000 mg/4 ml solution for injection: Patient Information Leaflet (UK) ↗
Patient leaflet (UK)
Full leaflet reviewed.
Detail: Nebido: injected very slowly into a muscle by a doctor; contains benzyl benzoate and castor oil; observe during and immediately after each injection.
- 16
Testosterone Enantate 250 mg/ml Solution for Injection: Patient Information Leaflet (UK) ↗
Patient leaflet (UK)
Full leaflet reviewed.
Detail: Testosterone Enantate: given by a doctor or nurse by very slow injection into a muscle; castor oil and benzyl benzoate; use only clear solution free from particles.
- 17
Sustanon 250, 250 mg/ml solution for injection (testosterone esters: propionate 30 mg, phenylpropionate 60 mg, isocaproate 60 mg, decanoate 100 mg) SmPC ↗
Product information (UK)
Full SmPC reviewed.
Detail: Sustanon 250: deep intramuscular injection; contains arachis (peanut) oil, so not for people allergic to peanut or soya; store below 30 °C, do not refrigerate or freeze.
- 18
Testosterone Enantate 250 mg/ml solution for injection ampoules SmPC ↗
Product information (UK)
Full SmPC reviewed.
Detail: Testosterone Enantate 250 mg/mL: inject extremely slowly, immediately after drawing up; blood half-life 2–3 days in healthy men.
- 19
Primoteston Depot (testosterone enanthate 250 mg/mL prefilled syringe) Australian PI ↗
Product information (Australia)
Full product information reviewed.
Detail: Primoteston Depot: like all oily solutions, must be injected intramuscularly and extremely slowly.
- 20
Taro-Testosterone Cypionate Injection 100 mg/mL product monograph ↗
Product monograph (Canada)
Full label reviewed.
Detail: Taro cypionate: deep gluteal intramuscular; discard within 56 days of first use; put used needles and syringes straight into a safety box or puncture-proof container.
- 21
StériMax testosterone cypionate injection USP 100 mg/mL (new DIN) product monograph ↗
Product monograph (Canada)
Full label reviewed.
Detail: StériMax cypionate: discard within 56 days of first use; patient information says it should only be given by a healthcare professional.
- 22
The British Society for Sexual Medicine Guidelines on Male Adult Testosterone Deficiency, with Statements for Practice ↗
Clinical guideline (UK)
Full text reviewed.
Detail: Subcutaneous enanthate has comparable blood levels, safety and tolerability and can be self-injected; long-term studies of subcutaneous micro-dosing are not available; little long-term data for cypionate; oil-cough risk is reduced if the injection is given over several minutes.
- 23
Evaluation and Management of Testosterone Deficiency: AUA Guideline ↗
Clinical guideline (US)
Full guideline reviewed.
Detail: Cypionate or enanthate, intramuscular or subcutaneous: first testosterone test no earlier than 3–4 injection cycles.
- 24
Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline ↗
Clinical guideline
Full guideline reviewed.
Detail: Lists pain at the injection site and coughing right after intramuscular injection as effects of injectable forms; the cough is reported rarely after undecanoate and even more rarely after enanthate and cypionate.
- 25
Endocrine Society of Australia position statement on male hypogonadism (part 2): treatment and therapeutic considerations ↗
Position statement (Australia)
Full text reviewed.
Detail: Deep intramuscular undecanoate cannot be self-given and is unsuitable for men with bleeding disorders or low platelets.
- 26
Evaluation for and Management of Males with Low Testosterone: Recommendations for Use (January 2026) ↗
Clinical recommendations (US)
Full document reviewed.
Detail: Intramuscular injections are on formulary, with possible bruising and redness at the site; subcutaneous testosterone is non-formulary, for specific clinical situations.
- 27
Reandron 1000 (testosterone undecanoate 1000 mg/4 mL) Australian PI ↗
Product information (Australia)
Full product information reviewed.
Detail: Reandron 1000: inject very slowly and deeply into the gluteal muscle, the only site for which clinical experience has been obtained.
- 28
FDA alerts health care providers, compounders and patients of dosing errors associated with compounded injectable semaglutide products ↗
Regulator safety alert (US)
Official page reviewed.
Detail: About compounded semaglutide, not testosterone: patients drew 50 units instead of 5 when units, milliliters and milligrams were confused.
- 29
Testosterone cypionate injection USP (generic, Hikma) prescribing information ↗
Product label (US)
Full label reviewed.
Detail: Generic cypionate in cottonseed oil: intramuscular only, deep in the gluteal muscle; inspect for particles; warming and shaking redissolves crystals; store at 20–25 °C, protected from light.
- 30
Sustanon '250' (mixed testosterone esters) Australian PI ↗
Product information (Australia)
Full product information reviewed.
Detail: Sustanon '250' (Australia): deep intramuscular injection.
- 31
Pharmacokinetics and Acceptability of Subcutaneous Injection of Testosterone Undecanoate ↗
Human trial (crossover)
Original abstract reviewed.
Detail: Crossover study of 20 long-term undecanoate users (11 men with hypogonadism, 9 transgender men): peak later after subcutaneous than intramuscular injection (8.0 vs 3.3 days) with similar exposure; more pain 24 hours after subcutaneous injection; 11 preferred intramuscular, 6 subcutaneous, 3 no preference.
- 32
Pharmacokinetics, safety, and patient acceptability of subcutaneous versus intramuscular testosterone injection for gender-affirming therapy: A pilot study ↗
Human study (pilot)
Original abstract reviewed.
Detail: 14 transgender men: exposure per mg was similar by route; subcutaneous injection had lower anxiety and pain scores.
- 33
NDA 216318 multidisciplinary review and evaluation (testosterone cypionate injection) ↗
FDA review
Original full text reviewed.
Detail: Azmiro was reformulated with more benzyl alcohol (20 mg/mL instead of 9.45); its maker says it may be less prone to crystals; in the bridging study, injection-site redness occurred in 7 of 27 men (26%) with each product, all mild, all in the first study period.
- 34
Anaphylaxis triggered by benzyl benzoate in a preparation of depot testosterone undecanoate ↗
Case report
Original abstract reviewed.
Detail: One case of anaphylaxis to a depot undecanoate product traced by skin testing to benzyl benzoate, not the castor oil or testosterone.
- 35
Testosterone Therapy With Subcutaneous Injections: A Safe, Practical, and Reasonable Option ↗
Review
Original abstract reviewed.
Detail: With training, people can self-inject subcutaneously with less discomfort than intramuscular injection; data are limited and direct safety comparisons are needed.
- 36
Comparison of Outcomes for Hypogonadal Men Treated with Intramuscular Testosterone Cypionate versus Subcutaneous Testosterone Enanthate ↗
Human study (observational)
Original abstract reviewed.
Detail: 234 men: weekly intramuscular cypionate and a weekly subcutaneous enanthate autoinjector reached similar trough testosterone (313.6 to 536.4 vs 246.6 to 552.8 ng/dL; 10.9 to 18.6 vs 8.6 to 19.2 nmol/L); the autoinjector group had lower estradiol and hematocrit; route, ester and device all differed.
- 37
Subcutaneous Injection of Testosterone Is an Effective and Preferred Alternative to Intramuscular Injection: Demonstration in Female-to-Male Transgender Patients ↗
Human study
Full text reviewed.
Detail: 63 transgender men on weekly subcutaneous cypionate or enanthate reached male-range levels; minor local reactions in 9 (small lumps clearing in 1 to 2 days in 4; one episode of cellulitis that resolved without treatment); all 22 who had used muscle injections preferred subcutaneous.
- 38
Factors influencing time course of pain after depot oil intramuscular injection of testosterone undecanoate ↗
Human study
Original abstract reviewed.
Detail: 168 nurse-given 4 mL undecanoate injections in 125 men: pain reported by 80%, worst straight away, lasting 1–2 days and gone by day 4; worse after an earlier painful injection, milder in older and heavier men.
- 39
Safety of a New Subcutaneous Testosterone Enanthate Auto-Injector: Results of a 26-Week Study ↗
Human study
Original abstract reviewed.
Detail: Xyosted 26-week study: injection-site bleeding in 6 of 133 men (4.5%) and bruising in 4 (3.0%); mild pain reported by 1 man across 965 assessed injections.
- 40
Adverse effects of dorsogluteal intramuscular injection versus ventrogluteal intramuscular injection: A systematic review and meta-analysis ↗
Systematic review
Original abstract reviewed.
Detail: 17 studies (1,429 people): the side-of-the-hip (ventrogluteal) site was less painful and caused less bleeding and bruising than the classic buttock site, with no difference in accidental subcutaneous injection.
- 41
The effect of intramuscular injection technique on injection associated pain; a systematic review and meta-analysis ↗
Systematic review
Original abstract reviewed.
Detail: 29 studies of intramuscular injection technique (very high variation between studies and risk of bias in small studies): pressing on the site reduced pain; warming the liquid did not; Z-track evidence was insufficient; changing the needle after drawing up gave conflicting results.
- 42
Comparison of the G and V methods for ventrogluteal site identification: Muscle and subcutaneous fat thicknesses and considerations for successful intramuscular injection ↗
Imaging study
Original abstract reviewed.
Detail: Ultrasound in 60 adults: with one standard way of locating the side-of-the-hip site, 92% of men would receive a true intramuscular injection.
- 43
Statistical estimation of deltoid subcutaneous fat pad thickness: implications for needle length for vaccination ↗
Imaging study
Original full text reviewed.
Detail: PET/CT scans of 386 people: a 1-inch needle expected to reach the deltoid in 207 of 210 men under 260 lb (98.6%), and a 1.5-inch needle in 6 of only 8 men over 260 lb (75.0%). Vaccine-oriented modelling, not testosterone.
- 44
Vaccine Administration: During Vaccination (needle length and technique) ↗
Public health guidance (US)
Official page reviewed.
Detail: Vaccine guidance, used as context only: 1–1.5 inch (25–38 mm), 22–25 gauge needles for intramuscular shots in men of 70–118 kg; 5/8 inch (16 mm) for subcutaneous; aspiration can increase pain.
- 45
Injection-Site Abscess Caused by Mycobacterium abscessus Following Testosterone Injection: A Case Report ↗
Case report
Original full text reviewed.
Detail: A 72-year-old man developed a persistent thigh abscess with Mycobacterium abscessus after a routine testosterone injection at an outpatient clinic; it needed surgical drainage and prolonged multidrug antibiotics, and his hospital stay was complicated by acute respiratory failure needing intensive care.
- 46
Sciatic nerve injury from intramuscular injection: a persistent and global problem ↗
Review
Original abstract reviewed.
Detail: Sciatic nerve injury from buttock injections remains avoidable but persistent worldwide; most reported cases were in children; general injections, not testosterone.
- 47
Complications of injectable testosterone undecanoate in routine clinical practice ↗
Human study (clinic records)
Original abstract reviewed.
Detail: 3,022 nurse-given undecanoate injections in 347 men: oil cough after 56 (19 per 1,000); 40% began before the injection finished; repeats more common than chance; no bleeding lumps after 269 injections in men on blood thinners.
- 48
Occurrence of Pulmonary Oil Microembolism After Testosterone Undecanoate Injection: A Postmarketing Safety Analysis ↗
Human study (safety reports)
Original abstract reviewed.
Detail: Manufacturer safety database: 28 reported oil-cough events for 90,092 Aveed doses shipped (below 0.1%); 13 of 17 with a known time settled within 30 minutes; technique or dosing possibly contributed in 3 of 4 emergency-level cases. Authors linked to the manufacturer.
- 49
AVEED (NDA 022219) cross-discipline team leader review, 2014 ↗
FDA review
Original document reviewed.
Detail: FDA noted rare reports of severe oil cough and allergic reactions with enanthate and cypionate, and 33 adjudicated reports of severe oil reactions or anaphylaxis over 44 years for all approved testosterone injections combined, with no usable denominator.
- 50
Delayed oleoma formation with injection of oil-suspended testosterone: A case report and review of pathogenesis ↗
Case report
Original abstract reviewed.
Detail: Painful lumps (oil granulomas) in both shoulders and a buttock found 9 years after a bodybuilder's non-prescribed oil injections.
- 51
Preventing Unsafe Injection Practices (CDC Injection Safety) ↗
Public health guidance (US)
Official page reviewed.
Detail: Healthcare-setting guidance: a new sterile needle and syringe every time; date an opened multi-dose vial and discard within 28 days unless the manufacturer says otherwise; prepare injections as close as possible to giving them.
- 52
Safe disposal of needles and sharps in the home ↗
Health service leaflet (UK)
Official page reviewed.
Detail: Dispose of the needle and syringe as one unit, never reuse or recycle them, do not fill above the line, and do not use drink cans or bottles.
- 53
Misuse of Drugs Act 1971, Schedule 2 Part III (Class C drugs) ↗
Law (UK)
Official text reviewed.
Detail: Lists testosterone as a Class C drug.
- 54
Controlled Drugs and Substances Act (S.C. 1996, c. 19): ss. 4, 6 and Schedule IV ↗
Law (Canada)
Official text reviewed.
Detail: Lists testosterone among anabolic steroids in Schedule IV of the Controlled Drugs and Substances Act.
- 55
Therapeutic Goods (Poisons Standard—June 2026) Instrument 2026 (F2026L00633) ↗
Regulation (Australia)
Official text reviewed.
Detail: Poisons Standard: testosterone is a Schedule 4 prescription-only medicine.
- 56
World Anti-Doping Code International Standard: Prohibited List 2027 (and explanatory note) ↗
Anti-doping list
Full list reviewed.
Detail: Keeps testosterone prohibited at all times.
- 57
Safely Using Sharps (Needles and Syringes) at Home, at Work and on Travel ↗
Regulator guidance (US)
Official page reviewed.
Detail: Put used sharps straight into an FDA-cleared container or a heavy-duty plastic household container; never loose in trash or recycling, and never flushed.
- 58
Aspiration in intramuscular injection: a meta-analysis of pain, duration, and clinical outcomes ↗
Systematic review
Original abstract reviewed.
Detail: 6 randomized trials (693 people, mostly children and vaccines): aspiration increased pain and injection time; no serious complications reported without it.
- 59
Guidance on the administration of Testosterone Undecanoate (UK risk minimisation material, Teva UK, GEN-GB-NP-00287 v1) ↗
Administration guide (UK)
Official page reviewed.
Detail: For long-acting undecanoate 1,000 mg/4 mL: an 18-gauge blunt needle to draw up, then a 20-, 21- or 22-gauge needle for the injection, chosen for the fat and muscle over the buttock; gluteus medius; aspirate; inject over about 2 minutes; watch for the oil cough.
- 60
Summative Usability Evaluation of the SCTE-AI Device: A Novel Prefilled Autoinjector for Subcutaneous Testosterone Administration ↗
Human study (device usability)
Original abstract reviewed.
Detail: Usability study of a Xyosted-type autoinjector, with observers and cameras present: 99 of 123 attempted injections (80.5%) delivered a full dose; the most common error was not holding it on the skin long enough. Manufacturer-affiliated author.
- 61
Best Way to Get Rid of Used Needles and Other Sharps ↗
Regulator guidance (US)
Official page reviewed.
Detail: Two steps: a sharps container right away, then, when about three-quarters full, community disposal such as drop-off sites, mail-back or special pick-up.
- 62
Community sharps management ↗
Health department guidance (Australia)
Official page reviewed.
Detail: Store used sharps in an approved or puncture-proof screw-top container and take it to a public sharps bin or a participating pharmacy, medical centre or hospital.
- 63
TSA What Can I Bring: Unused Syringes / Used Syringes ↗
Regulator guidance (US)
Official page reviewed.
Detail: Unused syringes are allowed through security when carried with injectable medication; used syringes go in a sharps or hard-surface container.
- 64
IM to SubQ Update ↗
Community account
Public thread reviewed: opening post and 70 comments.
Detail: After years of intramuscular injections, the poster moved to 30 mg of enanthate under the belly skin every other day and two weeks later reported better sleep, erections and energy, with no lumps.
- 65
Switched from IM to SubQ ~2.5 weeks ago… feeling worse. Normal adjustment period or should I switch back? ↗
Community account
Public thread reviewed: opening post and 37 comments.
Detail: Injections felt easier after a switch from weekly intramuscular to twice-weekly subcutaneous shots at the same 100 mg weekly dose, but mood, libido and erections worsened over 2.5 weeks.
- 66
SubQ and My Levels Tanked ↗
Community account
Public thread reviewed: opening post and 43 comments.
Detail: Testosterone fell and the poster felt unwell after moving to subcutaneous injections, but his weekly dose had also dropped from 150 to 100 mg; he felt better back on intramuscular injections.
- 67
Why would my testosterone drop from 1,151 to 667 on the same weekly dose after switching from EOD IM to daily SubQ? ↗
Community account
Public thread reviewed: opening post and 19 comments.
Detail: At about 120 mg a week, total testosterone was 1,151 ng/dL (about 40 nmol/L) on every-other-day intramuscular shots and 667 ng/dL (about 23 nmol/L) on daily subcutaneous shots, while hCG timing, syringe type, weight and sleep apnea treatment also changed.
- 68
Switched IM to SubQ - results ↗
Community account
Public thread reviewed: opening post and 44 comments.
Detail: The same 90 mg weekly dose moved from two intramuscular to three abdominal subcutaneous injections: trough testosterone rose and hematocrit fell, alongside about 25 lb of weight loss.
- 69
Subcutaneous and Hematocrit ↗
Community account
Public thread reviewed: opening post and 38 comments.
Detail: Daily subcutaneous shots, started to bring hematocrit down, were followed by a hematocrit of 57.4% about nine weeks later.
- 70
SUBQ to IM during dose Increase ↗
Community account
Public thread reviewed: opening post.
Detail: Red, itchy lumps began in the sixth week of twice-weekly subcutaneous shots and lasted longer each time; the poster moved to intramuscular injections as the dose rose.
- 71
Test Issues / Lumps on injection sites ↗
Community account
Public thread reviewed: opening post and 25 comments.
Detail: Subcutaneous shots in the arm and thighs left lumps lasting about a week with both 31- and 27-gauge needles, and smaller daily shots did not stop them.
- 72
Switched from IM to SubQ - definitely did not expect this. ↗
Community account
Public thread reviewed: opening post and 55 comments.
Detail: Small daily subcutaneous shots sometimes left a lump that cleared within hours; the dose, schedule and a supplement changed at the same time.
- 73
UPDATE ON INJECTION SITE IRRITATION ↗
Community account
Public thread reviewed: opening post and 18 comments.
Detail: Itchy, irritated skin followed two weeks of subcutaneous cypionate in grapeseed oil; intramuscular injections into the side of the hip, with the vial warmed and the plunger pressed slowly, caused no meaningful irritation.
- 74
Post Injection Swelling ↗
Community account
Public thread reviewed: opening post and 48 comments.
Detail: Large, firm lumps after subcutaneous shots of a non-pharmacy product in MCT oil eased with an antihistamine and did not return with a product in grapeseed oil.
- 75
Been getting PIP every time I pin ↗
Community account
Public thread reviewed: opening post and 43 comments.
Detail: Pain and swelling after each buttock injection from a new 400 mg/mL enanthate vial were easing by day eight, and replacement vials of lower-strength cypionate were arranged.
- 76
Major pain after injection ↗
Community account
Public thread reviewed: opening post and 28 comments.
Detail: A thigh injection from a new non-pharmacy supply in MCT oil caused severe pain and stiffness; later injections from the same supply did not.
- 77
Finally switched to 27g 1/2 inch ↗
Community account
Public thread reviewed: opening post and 18 comments.
Detail: Moving from a 25-gauge, 25 mm needle in the buttock or leg to a 27-gauge, 13 mm needle in the shoulder made the poster's injection painless.
- 78
Holy Crap, my first IM shot, been doing Subq for 6 weeks... ↗
Community account
Public thread reviewed: opening post and 71 comments.
Detail: After six weeks of slow, sometimes painful belly injections, a warmed 75 mg shoulder injection with a 27-gauge, half-inch needle was painless.
- 79
Deep IM vs Shallow IM vs Subq ↗
Community account
Public thread reviewed: opening post and 55 comments.
Detail: After trying subcutaneous and shallow intramuscular injections, the poster felt best on deeper thigh and buttock injections with 1-inch and 1.5-inch needles.
- 80
Is my husbands nurse giving his TRT injections wrong?? ↗
Community account
Public thread reviewed: opening post and 48 comments.
Detail: A wife describes her husband's first self-injection, low on the thigh, followed by swelling and difficulty walking for two weeks.
- 81
Tried the insulin syringe. Screw that. ↗
Community account
Public thread reviewed: opening post and 127 comments.
Detail: A 31-gauge insulin syringe drew the oil too slowly to be practical, after longer needles in the side of the hip had left bruises.
- 82
Are people really injecting to delts with 27g/grey needles? ↗
Community account
Public thread reviewed: opening post and 61 comments.
Detail: A 0.5 mL shoulder injection of a non-pharmacy product through a 27-gauge needle on a 3 mL syringe was hard to push and bled.
- 83
Draw inject same needle- too dull ↗
Community account
Public thread reviewed: opening post and 74 comments.
Detail: Drawing up and injecting with the same small needle made it hard to pierce the shoulder and left bleeding; later daily injections with a 27-gauge insulin syringe caused no pain.
- 84
Results after switching from injecting every 3.5 days to every other day ↗
Community account
Public thread reviewed: opening post and 19 comments.
Detail: After switching to a 29-gauge, half-inch needle in the side of the hip, the poster could not tell whether injections reached muscle or fat.
- 85
Significant lab result difference SubQ vs IM ↗
Community account
Public thread reviewed: opening post and 26 comments.
Detail: A pen that kept dripping after it was removed may have delivered incomplete subcutaneous doses for two weeks.
- 86
Daily injections..soft erections ↗
Community account
Public thread reviewed: opening post and 72 comments.
Detail: Replies pointed out that 0.12 mL a day from a 200 mg/mL vial is 24 mg a day, about twice the weekly dose the poster thought he was taking.
- 87
PSA- prefilling syringes can cause loss of volume as the oil gets absorbed into the stopper ↗
Community account
Public thread reviewed: opening post and 52 comments.
Detail: Pre-filled insulin syringes of an MCT-oil product appeared to lose volume within hours as the plunger seal swelled.
- 88
I injected 125mg of test into my thigh, I’m concerned of the swelling ↗
Community account
Public thread reviewed: opening post and 63 comments.
Detail: Warm, itchy swelling appeared after a thigh injection with a reused needle; replies urged prompt assessment, and the poster planned to go to urgent care.
- 89
I’m guessing I should to start rotating injections? (currently alternating sides) ↗
Community account
Public thread reviewed: opening post and 54 comments.
Detail: After alternating between only two sites on the side of the hip, a prominent bulge appeared; several replies urged medical assessment.
- 90
47 M got prescribed trt - 1st injection tonight - questions ↗
Community account
Public thread reviewed: opening post and 9 comments.
Detail: Before a first prescribed belly-fat injection, the large drawing needle looked frightening; with a smaller injecting needle, the shot was easy.
- 91
How can I do injections without anxiety attacks ↗
Community account
Public thread reviewed: opening post and 111 comments.
Detail: One-inch needles caused the poster anxiety; he tried inserting the needle only partway and asked about shorter needles.
- 92
The Effect of Route of Testosterone on Changes in Hematocrit: A Systematic Review and Bayesian Network Meta-Analysis of Randomized Trials ↗
Systematic review
Original abstract reviewed.
Detail: Network meta-analysis of 29 placebo-controlled trials: hematocrit rises of 4.0 points with enanthate or cypionate injections, 3.0 with gels and 1.4 with patches.
- 93
A 52-Week Study of Dose Adjusted Subcutaneous Testosterone Enanthate in Oil Self-Administered via Disposable Auto-Injector ↗
Human study
Original abstract reviewed.
Detail: Xyosted 52-week study: more than 95% of men reported no injection-related pain.
No matching sources
Try a different term or show the full list.
Updates and corrections
Published September 28, 2026. This guide replaces the earlier testosterone injections guide, which covered all injectable testosterone; dosing, blood work, hematocrit, fertility and estrogen now have their own guides. It corrects several of the earlier guide's statements: Azmiro is an intramuscular product given by a healthcare professional, not a subcutaneous autoinjector; Delatestryl is no longer marketed in the US; labels ask for slow injection over much longer than "10 to 30 seconds"; US labels name only the buttock muscle; and the claim that subcutaneous injection lowers hematocrit and estradiol rests on one study in which the ester and device also differed. Unsourced needle sizes and statements such as "light massage reduces soreness" were removed. The date describes this version, not a fresh check of every source.
Found an error or a relevant study we missed? Report a correction with the guide title, the specific passage and a supporting source if available. Please leave out personal health records. See our editorial policy for how we handle attribution, evidence limits and corrections.