
TRT
October 16, 2026
TRT blood tests: why timing can change what your result means
On this page
A testosterone blood test during treatment is a measurement taken at a particular point after a particular dose. Without that context, a result can look surprisingly high or low, or appear to have changed when the treatment itself has stayed the same.
Testosterone formulations enter the circulation differently. An injected depot releases medicine over time, a gel is absorbed through skin, and an oral product has its own absorption pattern. The interval between administration and blood collection is therefore part of the result—not an administrative detail to reconstruct later.
The practical question is not simply, “Should everyone test in the morning?” It is: “When should this test be collected for my exact product, schedule and clinical purpose?” Answering that before the appointment makes the result much more useful.
Diagnosis and treatment monitoring ask different questions
Before treatment, testing helps establish whether the body is producing consistently low testosterone in a person with compatible symptoms. The Endocrine Society recommends separate fasting morning measurements for that diagnostic assessment.
During TRT, the question changes. The clinician is assessing exposure from a prescribed formulation, along with symptoms and safety. A morning draw does not standardize exposure if one visit occurs shortly after administration and the next just before another dose. Endocrine Society guideline
Imagine two appointments at 9 a.m. One is the day after an injection; the other is near the end of the dosing interval. The clock times match, but the elapsed times do not. Those samples should not automatically be treated as equivalent observations.
Keeping a pretreatment result separate from monitoring results also helps. A value obtained while using testosterone is not a measurement of untreated hormone production and cannot simply be used to recreate the original diagnosis.
What happens between an injection and the blood draw?
Many injected testosterone preparations contain an ester in an oil-based formulation. The administered medicine becomes available over time rather than entering and leaving the circulation in a single instant.
A small historical pharmacokinetic study illustrates the effect. In 11 hypogonadal men, a 200 mg intramuscular testosterone cypionate injection produced peak total testosterone values on days two to five. Free testosterone and other hormones also changed during follow-up. Nankin's primary study
That was a specific research exposure in a small group, not a recommended schedule for readers. It does not establish a personal peak day for every formulation, injection route or dosing interval. It does show why elapsed time can materially change the result.
Our testosterone cypionate guide covers the formulation in more detail. For interpreting a laboratory trend, the essential starting point is an accurate administration history.
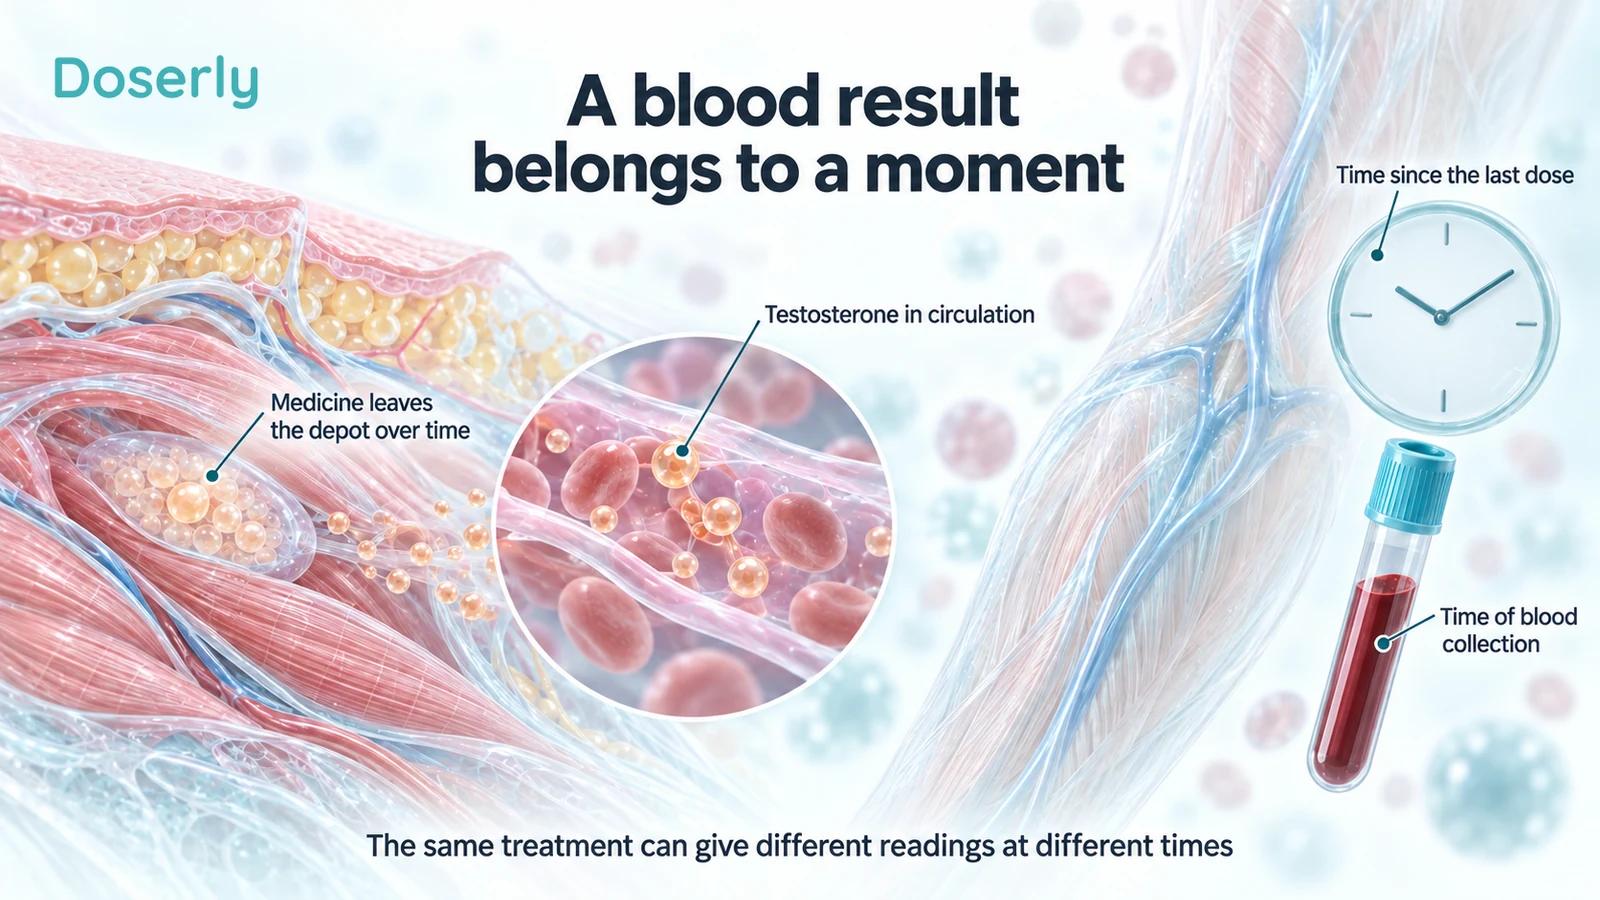
The depot, hormone shapes and blood collection scene are conceptual. They explain changing exposure over time without predicting a concentration, a personal peak or an appropriate injection technique.
Peak, trough and midpoint are different observations
A peak is a high point in the concentration profile. A trough is the low point near the end of an interval, commonly sampled before the next scheduled dose. A mid-interval sample is collected between doses.
These terms do not designate three interchangeable ways of measuring a person's single “true” level. Each describes a different position within exposure over time. A clinician might request one position for routine adjustment or another to investigate a particular concern.
The Endocrine Society's monitoring table recommends mid-interval measurement for injectable testosterone enanthate or cypionate. Product-specific instructions can differ: the XYOSTED label, for example, specifies a trough approach for that weekly subcutaneous enanthate product. Clinical guideline and XYOSTED prescribing information
This is why borrowing someone else's “always test at trough” rule can be misleading. The prescribed product and the clinical question determine which observation is intended. If instructions seem inconsistent, ask the prescriber to clarify the exact collection plan before the visit.
Three labels show why one rule does not fit every product
The following examples describe monitoring instructions from the named US prescribing information. They are not interchangeable schedules for all testosterone medicines.
Product
AndroGel 1.62%
- Label's sampling context
- Predose morning testosterone, around 14 and 28 days after starting or adjusting treatment
Product
XYOSTED
- Label's sampling context
- Trough concentration seven days after the most recent dose, following six weeks of treatment or dose adjustment
Product
JATENZO
- Label's sampling context
- Serum testosterone six hours after the morning dose, at least seven days after starting or adjusting treatment
Sources: AndroGel 1.62%, XYOSTED, JATENZO.
Two separate intervals appear in this table. One is the time since the last dose. The other is how long the person has been using the current regimen. Both can matter.
A sample might be collected at the correct hour after today's dose but too soon after a recent change to answer the intended monitoring question. Conversely, someone can have used an unchanged prescription for months but attend the laboratory at the wrong point in the dosing interval.
Why the exact gel product matters
“Testosterone gel” describes a route, not one universal formulation. Concentrations, application sites and monitoring instructions can differ. AndroGel 1.62% explicitly uses a predose morning concentration for its titration approach, and its label warns that its application site and dose are not substitutable with other topical products. AndroGel label
If advice from a general article says to test after application but your prescriber gives product-specific predose instructions, do not combine the two approaches on your own. Confirm the medicine name, concentration and intended collection time.
Bring a photograph of the pharmacy label or the actual medication name in your record. “Two pumps” without the product and concentration is not enough information to reconstruct exposure, because a pump actuation is a delivery unit rather than a universal testosterone amount.
The testosterone gel guide explains the practical differences between topical treatment and injections, including application and transfer precautions.
Oral testosterone adds a meal and product context
JATENZO's label instructs patients to take it with food and specifies a six-hour post-morning-dose serum measurement for adjustment. It also includes laboratory handling instructions. JATENZO prescribing information
That means a generic instruction to arrive fasting before taking any morning medicine could conflict with the intended monitoring procedure for this product. The ordering clinician and laboratory need a shared plan.
Other oral testosterone products have their own instructions. Do not assume that “oral testosterone undecanoate” makes every brand's sampling window identical. Our oral testosterone guide provides the broader formulation context.
When documenting the visit, include the time the capsule was taken and whether the prescribed food instructions were followed. These details help the clinician interpret an unexpected result without guessing whether it reflects the medicine, its administration or the collection.
A gel result can be wrong for a different reason
Correct timing does not prevent every sampling problem. Testosterone gel on or near the blood collection site can contaminate the specimen, producing an unexpectedly high measured concentration.
A 2023 retrospective report examined 578 people using topical testosterone gel. Forty-eight had at least one result above 1,000 ng/dL. The records strongly supported gel contamination as the explanation in seven patients. The authors did not establish that every high result was contaminated, and the true frequency remained uncertain. Case series and retrospective review
The distinction matters because contamination is a collection problem, not necessarily excessive circulating exposure. At the same time, a high result should not be dismissed as contamination without assessment. The clinician may need to review application location, collection circumstances and repeat testing.
Tell the phlebotomy team that you use testosterone gel and follow the product and clinician instructions for application and blood collection. Do not improvise a new application site simply for testing.
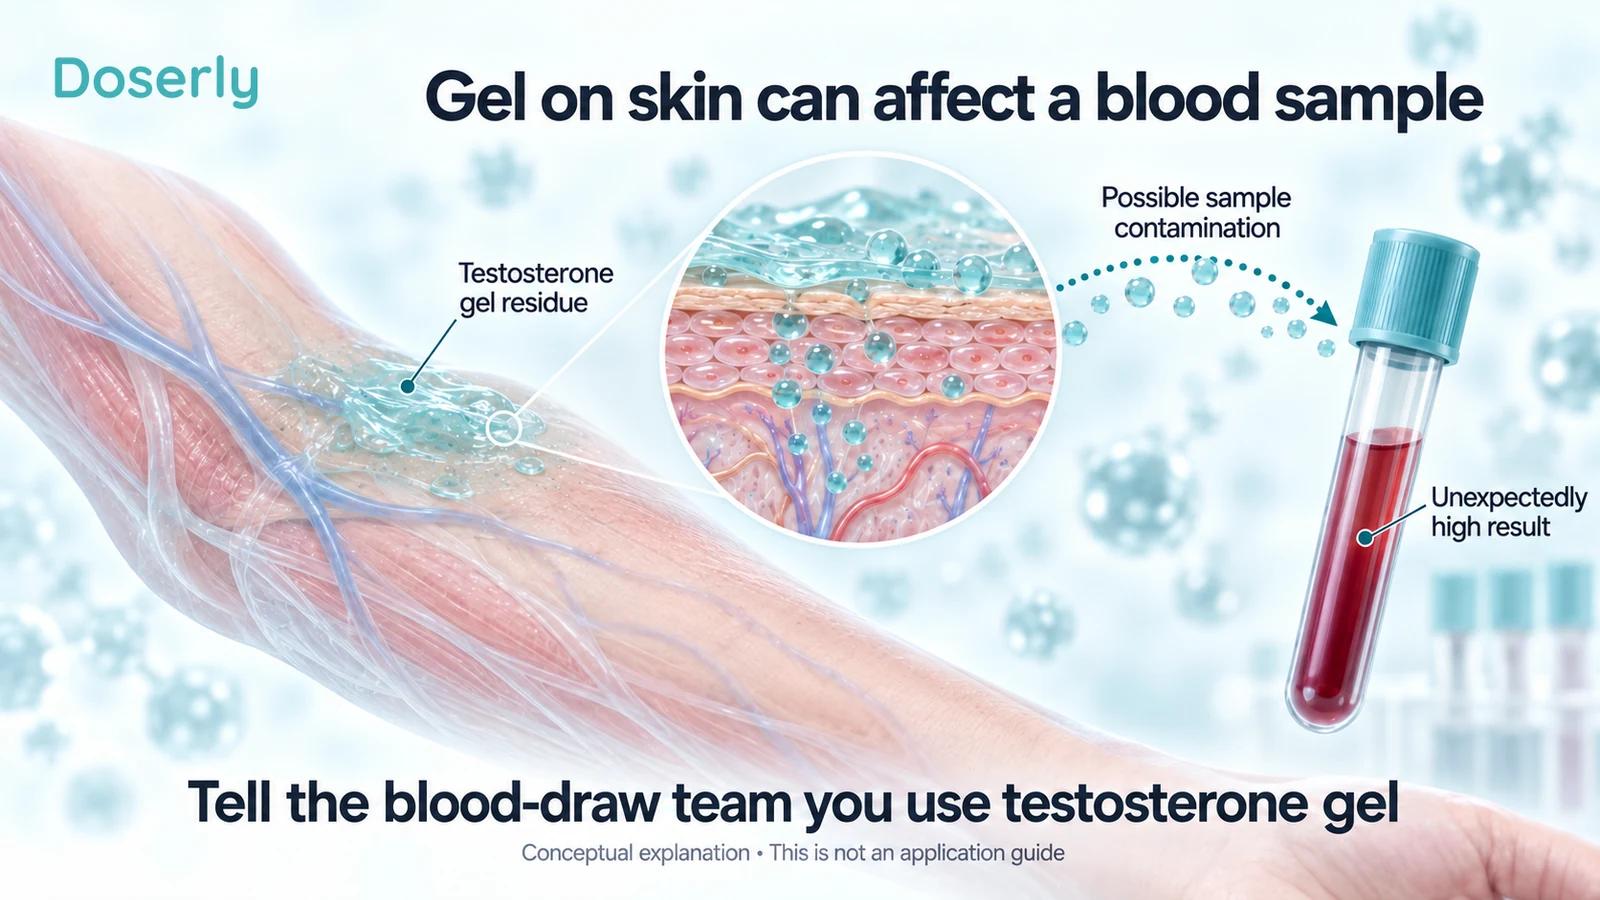
The relevant problem is surface gel contaminating collection, independently of the intended absorption into circulation. The illustration is a conceptual explanation, not a recommendation to apply gel near the inner elbow.
Recent changes can make a trend difficult to interpret
Suppose the prescription changed, several doses were delayed during travel, and the blood draw was moved to another weekday. A new result may reflect all three changes. Comparing it with the previous number as though only the dose changed loses that context.
The label-specific waiting periods above provide concrete examples of why clinicians allow time after adjustments. They should not be replaced with a universal claim that every testosterone product reaches a stable monitoring state after the same number of days.
For a follow-up visit, write down when the current prescription began and when you actually administered recent doses. Include missed or delayed doses honestly. The purpose is to explain the sample, not to demonstrate perfect adherence.
If the clinician is intentionally investigating an unusual symptom pattern, a nonstandard sampling time may be useful. It should be labeled as such so that it does not later get mistaken for a routine comparison point.
What a useful laboratory record looks like
A concise note can preserve the essential context:
- Exact medicine, formulation and prescribed schedule.
- Actual date and time of the most recent administration.
- Date and time of blood collection.
- Date of the last prescription change.
- Missed doses, unusual application circumstances or relevant illness.
- Symptoms around that part of the interval.
The laboratory report should remain attached, including units and reference ranges. A note saying “testosterone 600” omits the unit, the assay context and whether the sample was collected before or after medication.
For recurring tests, consistency helps. It is easier to compare visits when they answer the same question using the same intended timing. Consistency does not mean ignoring symptoms between visits; those belong in the record too.
A tracking app or a simple dated note can both work. The useful feature is the preserved relationship between administration, symptoms and collection, rather than the sophistication of the chart.
What to do with an unexpected result
First confirm that the clinician has the timing and medication details. If a result is very different from prior values, ask whether the collection matched the plan and whether a formulation change, missed dose, laboratory method or contamination could be relevant.
Do not select a new sampling time solely to obtain a more reassuring number. A deliberately different time may answer a different question rather than demonstrate an improvement.
Similarly, do not change the prescription yourself to correct one unexpected value. The clinician needs to interpret exposure alongside symptoms, the reason for treatment and other safety monitoring. An isolated testosterone concentration does not summarize the entire treatment assessment.
If the clinician requests a repeat, ask which uncertainty the repeat is meant to resolve. “Same regimen, correct product-specific timing, documented application site” is a much clearer plan than simply “check again.”
The question to settle before the next appointment
Ask: “For this exact product and the way I take it, when should the blood be collected, and what should I do with that day's scheduled dose?”
Then record the answer with the appointment. If the laboratory's generic preparation instructions conflict with it, have the clinic clarify the plan. This small piece of coordination can prevent an apparently dramatic hormone change from being interpreted without the information needed to understand it.
Sources
- Endocrine Society guideline: diagnosis and formulation-specific monitoring
- AndroGel 1.62% prescribing information
- XYOSTED prescribing information
- JATENZO prescribing information
- Pinedo Pichilingue and colleagues: gel contamination case series, 2023
- Nankin: intramuscular cypionate hormone kinetics, 1987