
Peptides
October 16, 2026
Why KPV is not a diagnosis for persistent digestive symptoms
On this page
When abdominal pain, bloating or diarrhea keeps returning, a treatment that promises to calm inflammation can feel like a direct answer. But “inflammation” is not a complete explanation for a symptom, and KPV is not a diagnostic test. Choosing a peptide before understanding the problem can leave the most important question unresolved: what is causing the symptoms?
Several conditions can produce overlapping digestive complaints. The useful next step is to describe the pattern, consider the medical context and decide whether targeted investigations are needed. That process can lead to very different treatments depending on what is found.
KPV has been studied in cells and animal models of intestinal inflammation. Those experiments do not show that an unexplained symptom is caused by the pathway being studied, or that a response to a KPV product confirms a particular disease. Our KPV guide covers the compound; this article focuses on getting a clearer explanation for persistent symptoms.
When symptoms should not wait for a routine appointment
Seek prompt medical care for severe abdominal or rectal pain, black tarry stools, red blood or pus in stool, frequent vomiting, confusion or signs of dehydration. Reduced urination, pronounced thirst and dizziness can accompany dehydration. For adults with diarrhea, NIDDK also advises contacting a doctor right away when it lasts more than two days, involves high fever or reaches six or more loose stools daily. NIDDK symptom guidance.
These are reasons to get assessed, not a checklist for deciding that everything else is harmless. A person who is pregnant, older, immunocompromised or taking antibiotics may need earlier advice. Children, particularly infants, need age-specific guidance; the adult discussion here is not a pediatric assessment tool.
Do not use a symptom diary or an experimental product trial as a reason to postpone care for a concerning change. If symptoms are severe or you feel acutely unwell, urgent services can determine the appropriate level of assessment.
Describe the symptom before assigning a mechanism
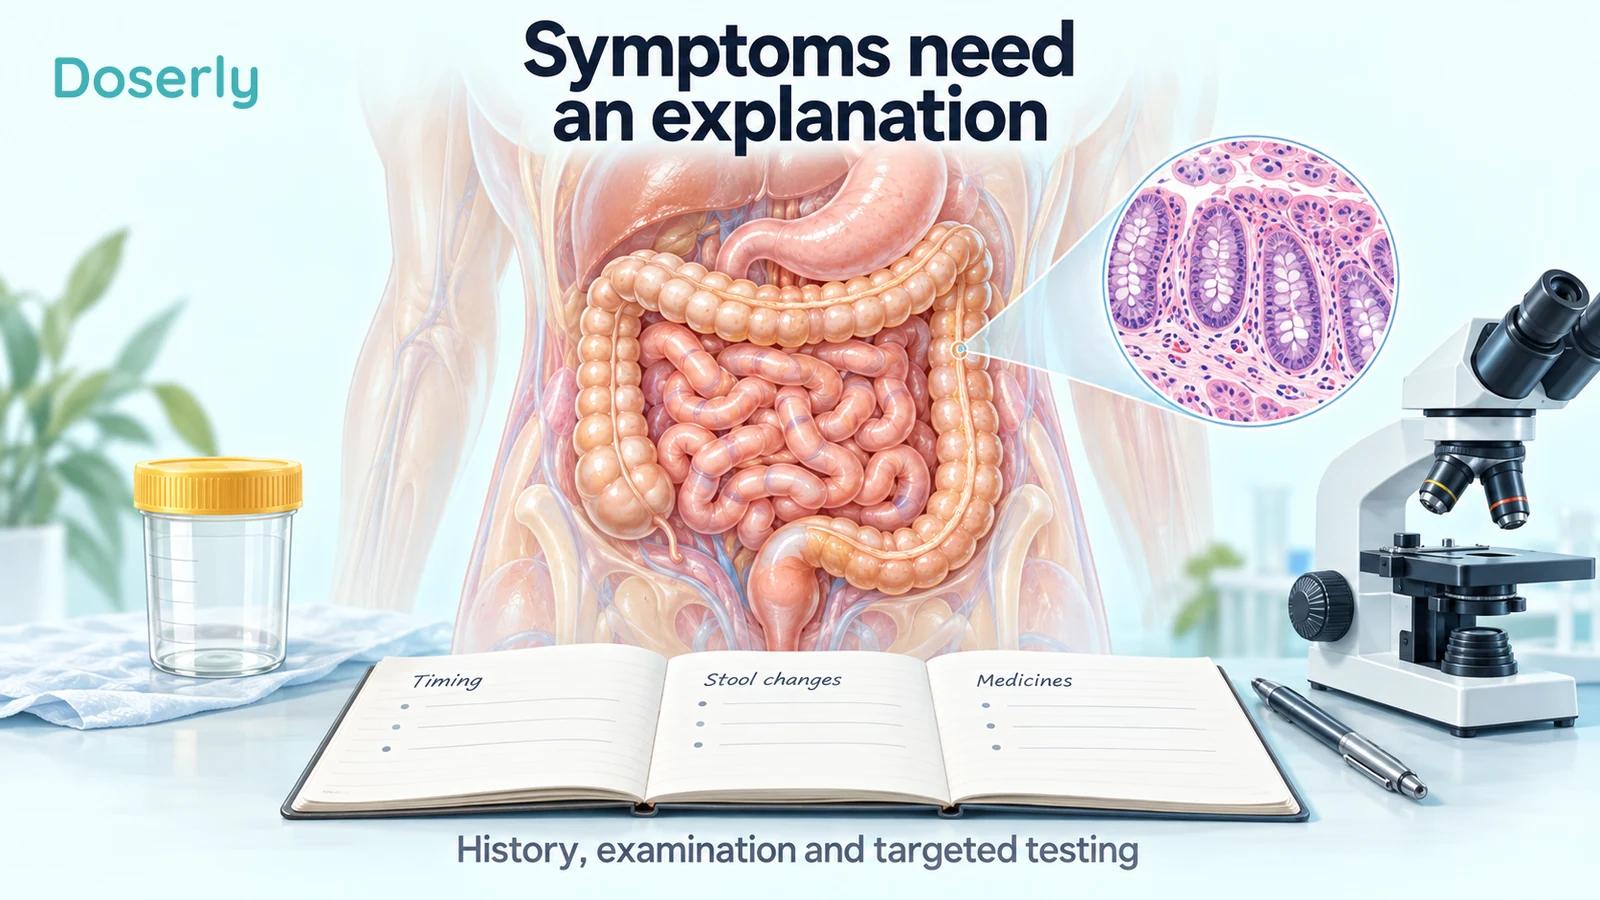
“I have gut inflammation” may be a confirmed diagnosis, a description someone gave you or an interpretation of how you feel. Those meanings are different. A more useful starting description is concrete: when the problem began, how often it happens, what the stools look like, whether pain relates to bowel movements and how symptoms affect eating, sleep or work.
NIDDK describes medical and family history, physical examination and selected tests as parts of evaluating diarrhea. Relevant history includes medicines, eating habits, prior conditions and recent travel. Stool testing, blood testing, breath testing or endoscopy may be considered depending on the clinical question. Not everyone needs every test. NIDDK diagnostic overview.
A clear history is useful even when it does not immediately reveal the cause. “Three loose bowel movements most mornings since a medication change” gives a clinician something more specific to investigate than “my gut is damaged.” It also leaves room for alternative explanations instead of assuming the answer in advance.
IBS and inflammatory bowel disease need different reasoning
Irritable bowel syndrome, or IBS, is diagnosed from a characteristic symptom pattern together with clinical assessment. NIDDK describes attention to abdominal pain, its relationship to bowel movements and changes in stool frequency or appearance. Depending on the history, clinicians may investigate other explanations. Rectal bleeding, anemia or unexplained weight loss deserve particular attention. NIDDK IBS diagnosis.
An IBS diagnosis does not mean the symptoms are imaginary. It also does not mean that every possible disease must be excluded with an unlimited set of tests. The assessment should fit the presentation and account for features suggesting another condition.
Ulcerative colitis, one form of inflammatory bowel disease, requires a different evaluation. Blood and stool tests can contribute information, while endoscopy with biopsies helps establish the diagnosis, assess severity and identify how much of the large intestine is affected. Testing also helps distinguish infections and other causes of similar symptoms. NIDDK ulcerative-colitis diagnosis.
This distinction explains why a general anti-inflammatory claim is insufficient. A product proposed for experimental colitis has not thereby been shown to treat IBS, and symptoms resembling a colitis flare do not establish that a flare is the cause. The diagnosis affects both the treatment and what needs monitoring.
Celiac testing can be affected by changes made beforehand
Celiac disease can share symptoms with other digestive disorders, so symptoms alone do not diagnose it. Blood tests and, in many cases, small-intestinal biopsies are used in the diagnostic process. NIDDK advises against starting a gluten-free diet before diagnostic testing because doing so can affect the results. NIDDK celiac diagnosis.
That is a useful example of why treatment experiments and diagnosis should be coordinated. Someone may remove gluten, start several supplements and add KPV at the same time, then find it difficult to explain what changed or how to interpret later testing. Feeling better is welcome, but it does not tell us which change mattered or establish celiac disease.
If you have already altered your diet, tell the clinician what you changed and when. Do not undertake a self-directed gluten challenge solely on the basis of this article. The clinician can decide how the history affects testing and what approach is appropriate for you.
The larger point is that an apparently simple “try it and see” strategy can change the information available for diagnosis. Keeping the evaluation plan visible helps avoid solving one uncertainty by creating several more.
Targeted testing is more useful than an indiscriminate panel
Professional guidance illustrates how testing can follow a defined question. The American Gastroenterological Association’s guideline for immunocompetent adults with chronic watery diarrhea discusses stool inflammatory markers, Giardia testing, celiac testing and consideration of bile-acid diarrhea. It does not recommend the same indiscriminate parasite testing for everyone. AGA guideline.
Its scope matters. The guideline concerns watery diarrhea lasting at least four weeks and excludes several presentations requiring a different evaluation, including bloody diarrhea, alarm features and certain higher-risk histories. It is not a universal self-ordering checklist for all abdominal symptoms. AGA scope explanation.
A stool inflammation marker, a blood antibody test and a tissue biopsy answer different questions. A result should be interpreted with the reason it was ordered, the clinical history and any next steps. “Normal blood tests” is too broad to know what was actually assessed; similarly, an abnormal result needs its exact name and context.
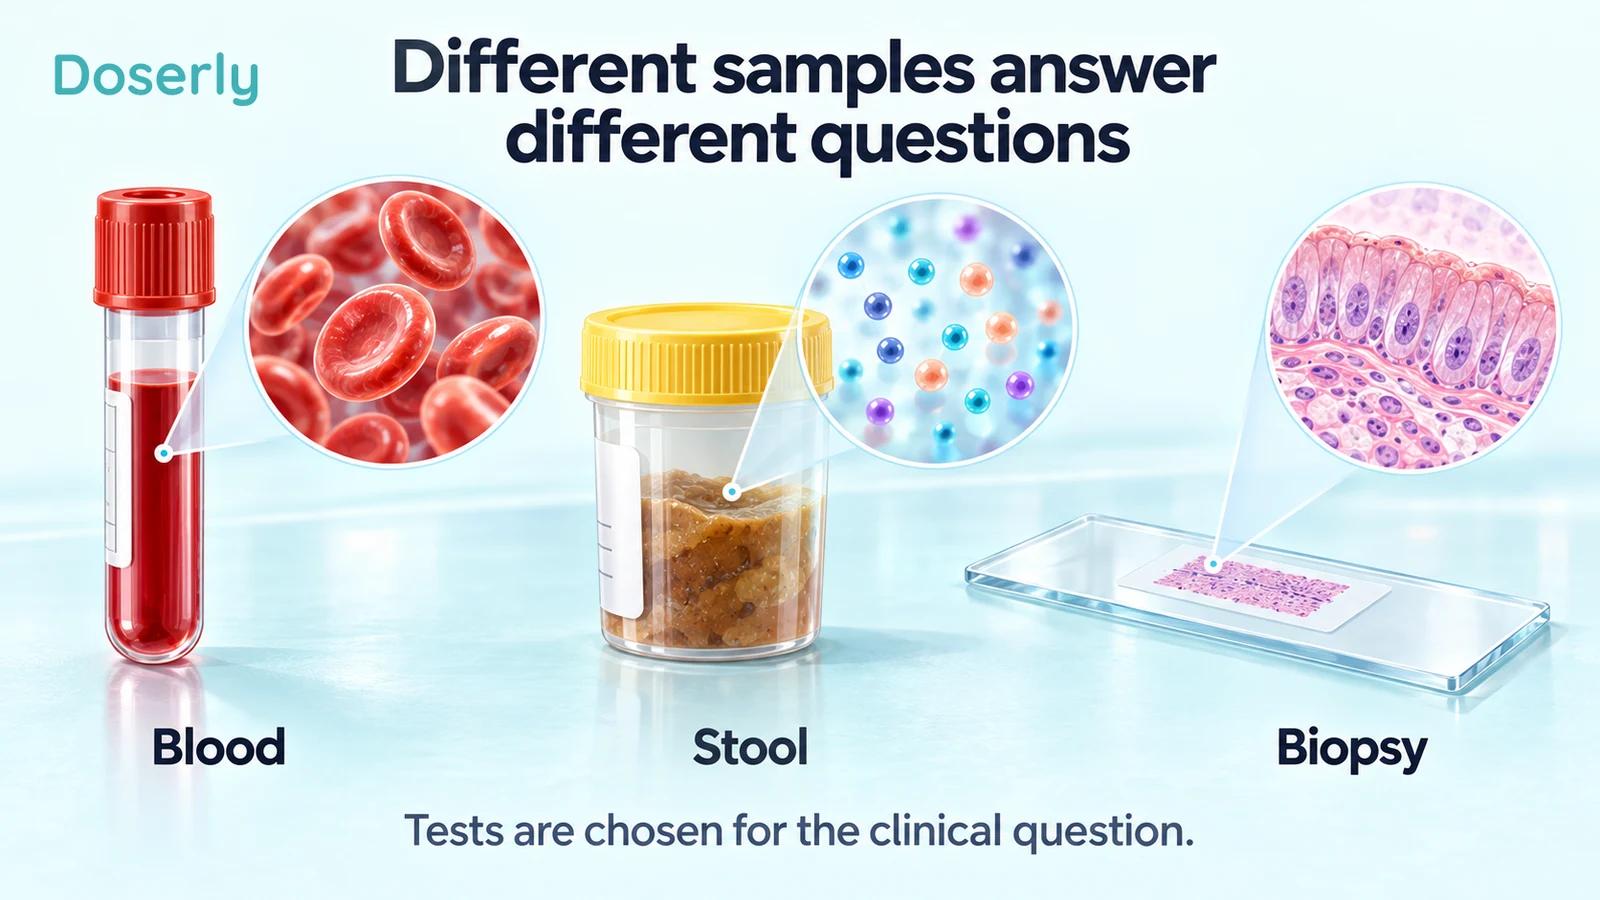
At an appointment, it is reasonable to ask what a test can establish, what it cannot exclude and how the result would change the plan. Those questions help connect investigation to a decision. They are more productive than trying to collect every available marker of “gut health.”
Persistent symptoms can still need assessment after an IBD diagnosis
Having established inflammatory bowel disease does not make every subsequent digestive symptom self-explanatory. AGA advice recommends a stepwise assessment for ongoing inflammation when gastrointestinal symptoms persist in people with IBD. It also calls for considering structural complications and other mechanisms according to the symptom pattern. AGA clinical practice update.
This matters in both directions. Symptoms should not automatically trigger an assumption that inflammatory disease is active, and reassuring symptoms should not automatically settle every question about disease activity. The relevant measurements and follow-up depend on the person’s established condition and treatment plan.
If you already have a gastroenterology team, report the change through the agreed route rather than replacing prescribed care with a new peptide experiment. Describe what is different from your usual pattern, any medication changes and any concerning associated symptoms. That makes it easier to distinguish a familiar fluctuation from something needing reassessment.
What KPV research cannot diagnose
The often-cited KPV gut study examined inflammatory signaling in cultured cells and outcomes in chemically induced mouse colitis. It offers a research rationale, not a test for whether a person’s bloating, pain or loose stools are caused by intestinal inflammation. Original KPV experiment.
The FDA’s July 2026 briefing found no identified clinical studies or human exposure data for KPV free base or acetate by any administration route, and no human pharmacokinetic or pharmacodynamic studies. That leaves substantial uncertainty about human benefit and safety. FDA assessment.
Even an established treatment response is not automatically a diagnosis. With KPV, the problem is more fundamental: the relevant human treatment effect itself has not been established by the sources checked here. “It helped, therefore I had inflammation” joins two uncertain conclusions together.
A lack of response is equally uninformative as a diagnostic test. It cannot rule out inflammatory bowel disease, celiac disease, infection or another cause. Neither improvement nor nonresponse should replace the investigations that are appropriate to the actual clinical presentation.
Make a medication and supplement timeline
Bring a complete list of prescription medicines, over-the-counter products and supplements, including products you do not regard as medicines. Record recent starts, stops and changes. If KPV or another peptide is already involved, include the product name, formulation, route and dates rather than simply writing “peptides.”
Some medicines can cause diarrhea, including antibiotics and magnesium-containing antacids; some liquid products contain sugar alcohols that can contribute. This does not mean a medicine is necessarily the cause in your case, or that you should stop a prescribed treatment without advice. It means the exposure history belongs in the assessment. NIDDK causes of diarrhea.
A timeline is especially useful when several changes occurred close together. Write down the sequence as accurately as possible and mark uncertainty honestly. An approximate date is better than a confident but incorrect recollection. A photo of the label or a retained package can clarify ingredients and formulation during a clinical review.
Use tracking to improve the conversation
A short, consistent record is usually easier to discuss than a large collection of disconnected notes. You might record the date, bowel-movement frequency, stool appearance, pain or urgency, relevant medicine changes and any blood, fever or vomiting—details that help supply the history described in NIDDK’s diagnostic guidance. Keep the entries descriptive rather than assigning a cause to each episode.
For example, “pain started after lunch and eased after a bowel movement” preserves an observation. “The peptide blocked inflammation” supplies a mechanism that the entry cannot verify. The first is useful even if your eventual diagnosis differs from your initial expectation.
Choose a recording approach that is manageable. A paper note or an app can organize the same basic information; neither measures intestinal inflammation or makes a diagnosis. Do not delay contacting a clinician in order to complete a perfect week of entries.
At follow-up, review whether the plan answered the original question. Which results are back? What diagnosis is being considered? What should change, and when should you make contact again? Knowing the next decision point can reduce the temptation to keep adding untested products while the explanation remains uncertain.
Persistent digestive symptoms deserve both relief and an explanation. KPV research does not remove the need for that explanation. A clear history, appropriately selected tests and a plan tied to the actual diagnosis provide a more useful foundation for deciding what to do next.
Sources
- NIDDK, diarrhea symptoms and causes.
- NIDDK, diagnosing diarrhea.
- NIDDK, diagnosing IBS.
- NIDDK, diagnosing ulcerative colitis.
- NIDDK, diagnosing celiac disease.
- AGA, chronic watery diarrhea guideline.
- AGA, guideline scope and exclusions.
- AGA, persistent functional symptoms in IBD.
- Dalmasso et al., experimental KPV study.
- FDA, KPV briefing.