
Peptides
October 16, 2026
Weight regain after semaglutide: what the STEP extension tells us
On this page
Semaglutide helps regulate appetite and food intake while it is being taken. It is understandable to wonder whether a period of treatment leaves a lasting effect once injections stop. If you've reached a weight that feels healthier or treatment has become difficult to afford or tolerate, the question is practical: what happens next?
The STEP 1 extension followed a subset of participants for a year after both study medication and structured lifestyle support ended. People previously assigned semaglutide regained, on average, about two-thirds of the weight they had lost. They remained below their original weight on average, and individual outcomes varied. STEP 1 extension
That finding supports planning for maintenance from the beginning. It does not mean everyone will regain the same amount, that a year of treatment was pointless or that every person must remain on the same regimen forever. The design tells us something more specific, especially when read alongside a separate randomized withdrawal trial called STEP 4.
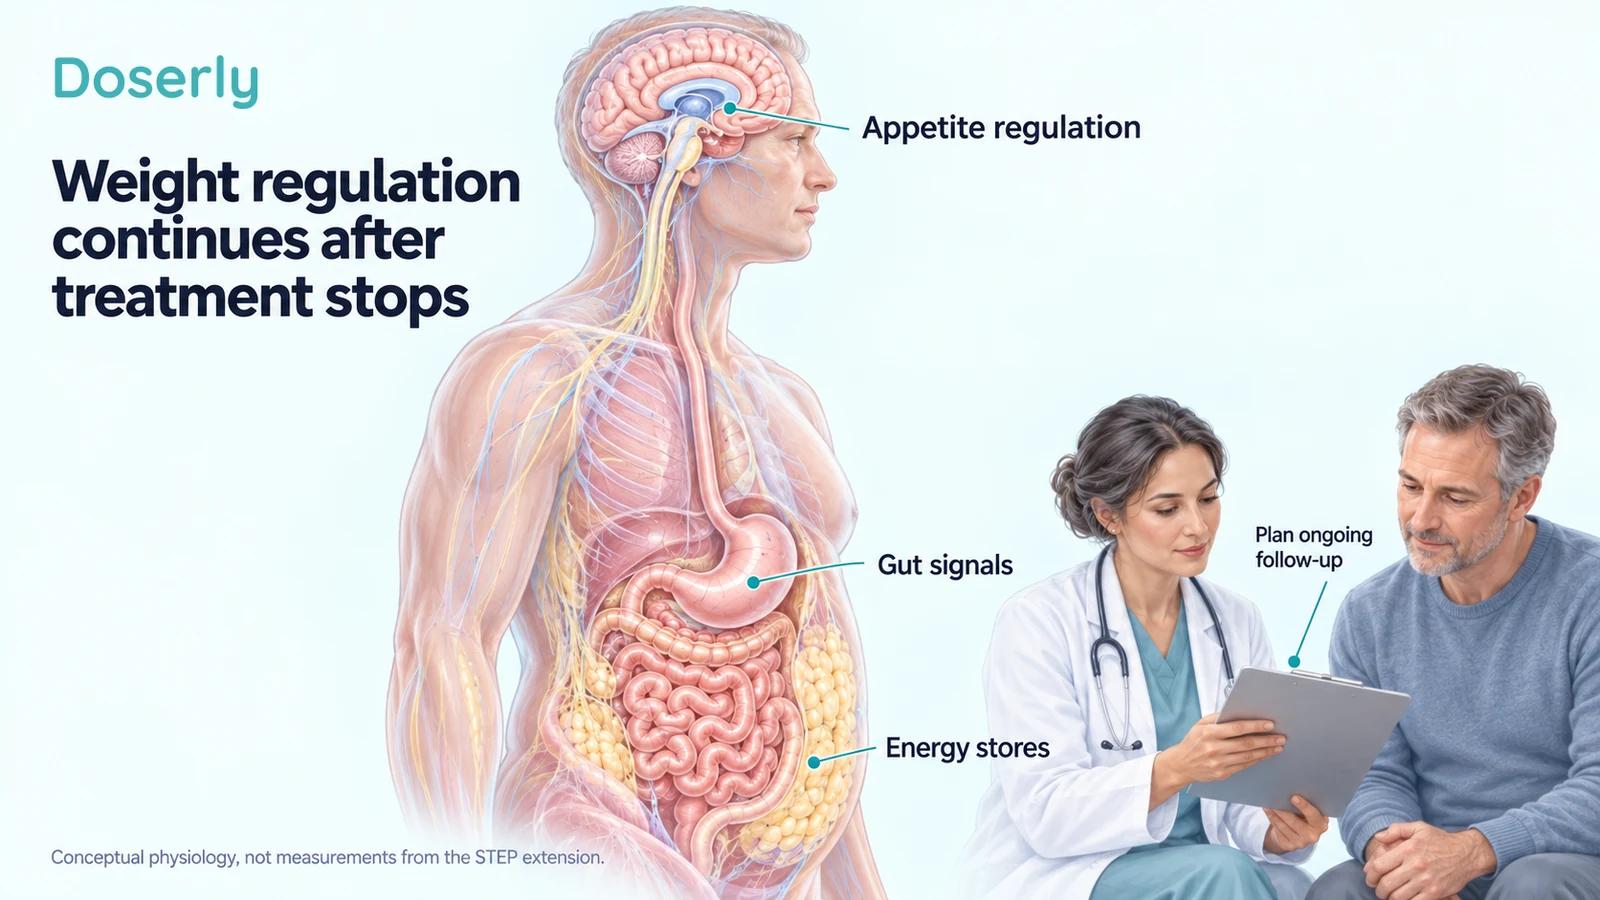
What ended at week 68?
The original STEP 1 trial studied adults with obesity, or overweight with at least one weight-related condition, without diabetes. Participants received weekly semaglutide, targeting 2.4 mg, or placebo alongside a lifestyle intervention. The main treatment period lasted 68 weeks.
At the end of that period, both medication and the structured lifestyle intervention stopped. The extension then followed a selected subset who had completed the main treatment period for another 52 weeks, through week 120. Its analyses included 327 people and were exploratory. Extension methods
This was not a new randomization at week 68 in which some semaglutide participants continued treatment and others stopped. The extension observed what happened after the trial interventions ended. It therefore cannot completely separate stopping medication from losing the trial's organized support.
That matters because real-world stopping can take different forms. Someone might discontinue medication but continue intensive follow-up, change to another treatment or lose access to both medication and care. The extension does not test every one of those scenarios.
What does “two-thirds regained” actually mean?
In the extension subset, average weight loss through week 68 was 17.3% in the semaglutide group and 2.0% in the placebo group. Over the following year, the former semaglutide group regained 11.6 percentage points of body weight, leaving an average net loss of 5.6% from the original baseline at week 120. The former placebo group regained 1.9 percentage points and was approximately back to baseline. Reported extension results
The phrase “two-thirds” refers to the fraction of the earlier loss that returned. It does not mean people gained two-thirds of their original body weight. The denominator is crucial: weight lost during treatment and total starting weight are different quantities.
As an arithmetic illustration, imagine a starting weight of 100 units. A 17.3% loss would put it near 82.7 units. Regaining roughly 11.6 units would put it near 94.3. That illustration is not an individual participant's record. The paper's reported net loss is 5.6%; rounding and the way summary values are calculated mean the displayed figures should not be forced into an exact subtraction identity.
It is also inaccurate to substitute the original trial's overall average loss for the extension subset's 17.3%. The people included in a follow-up analysis can have a different average from the full original population. Keep the result attached to the group actually analyzed.

Did everyone regain most of the weight?
No single average can tell us that. The extension reported substantial variability around the mean. Some people maintained more of their loss than others, and the study cannot forecast one person's trajectory from the group result alone.
A useful interpretation is that substantial regain was common enough to shift the average markedly within one year. The result should make maintenance planning a normal part of care, rather than turn into a prediction that a particular person is destined to fail.
It also does not establish that all prior benefits disappeared instantly. The average remained below baseline at one year. At the same time, many improvements in cardiometabolic measurements moved back toward baseline. These measurements included risk factors, not a direct demonstration of the long-term number of heart attacks or strokes after stopping. Extension findings
The distinction is particularly relevant if semaglutide was prescribed for more than weight management. A decision about treatment may involve glucose control or cardiovascular risk as well as body weight. The extension cannot settle all of those questions, especially because participants did not have diabetes.
What did STEP 4 add?
STEP 4 tested withdrawal more directly. Everyone first received semaglutide for 20 weeks. Of 902 people entering that phase, 803 who reached the 2.4 mg weekly maintenance dose were randomized either to continue semaglutide or switch to placebo for another 48 weeks. Both groups continued lifestyle intervention. STEP 4
Participants had lost an average of 10.6% during the initial period. From week 20 to week 68, those continuing semaglutide lost another 7.9% of their week-20 weight, while those switched to placebo gained 6.9%. The estimated difference was −14.8 percentage points, with a confidence interval from −16.0 to −13.5.
Because structured lifestyle intervention continued in both randomized groups, STEP 4 strengthens the conclusion that ongoing medication contributed to maintaining the weight response under those conditions. It addresses an uncertainty left by the STEP 1 extension, where medication and structured support ended together.
But STEP 4 also selected participants through its initial treatment period. People who could not reach the target dose were not part of the randomized comparison. Its tolerability and maintenance results therefore describe people who made it through that phase, not everyone starting semaglutide for the first time.
Why percentages from different phases cannot simply be added
In STEP 4, the first percentage change is calculated from the starting weight; the later change is calculated from weight at randomization. Those are different denominators. Losing 10% and then gaining 10% does not return a person exactly to the starting value, because the second 10% is calculated from a smaller number.
For a simple example, a weight of 100 units becomes 90 after a 10% loss. A subsequent 10% gain from 90 adds nine units, giving 99. These invented round numbers explain the arithmetic; they are not results from STEP 4.
The STEP 1 extension's regain is reported in percentage points relative to the original baseline. That is why “11.6 percentage points regained” needs different wording from STEP 4's “6.9% increase from week 20.” Keeping each study's reference point prevents apparently similar statistics from becoming misleading.
For personal tracking, record actual dated weights under reasonably consistent conditions. Your clinician can then interpret changes over a defined interval without mixing the start of treatment, the lowest recorded weight and the date medication changed.
What if treatment continues?
STEP 5 provides a separate two-year comparison. It randomized 304 adults without diabetes to semaglutide or placebo, both with behavioral intervention. Mean weight change at week 104 was −15.2% with semaglutide and −2.6% with placebo. Weight loss largely plateaued and was maintained during continued treatment. STEP 5
A longer analysis from SELECT found an average weight change of −10.2% with semaglutide versus −1.5% with placebo at 208 weeks. SELECT involved an older, cardiovascular-disease population and was designed primarily around cardiovascular outcomes. Its smaller average weight loss should not be read as proof that the medicine inevitably stops working after two years. SELECT weight analysis
These studies support durable average weight effects with ongoing treatment in their respective settings. They do not prove that every patient benefits indefinitely or that the same dose is right for every phase of care. Benefits, side effects and changing circumstances still need review.
Is regain evidence of addiction or personal failure?
The withdrawal studies measured weight and related outcomes. They were not demonstrations of an addiction syndrome. Semaglutide's intended effects on appetite and food intake can be reduced when treatment ends; needing continued treatment for an ongoing condition is a different issue from addiction. Wegovy mechanism and clinical studies
The findings also do not justify blaming people for insufficient effort. In STEP 4, the group switched to placebo regained weight despite continuing the trial's lifestyle intervention. That observation shows why motivation alone is an incomplete explanation for maintenance outcomes.
A helpful response to regain is to review what has changed: appetite, eating patterns, symptoms, activity, sleep, access to care and other medicines. The purpose is to identify an appropriate next step, not to judge whether someone deserved the earlier benefit.
What do we know about tapering or a lower maintenance dose?
Neither the STEP 1 extension nor STEP 4 randomized participants to a gradual taper versus abrupt withdrawal. They also did not identify a universal minimum dose that would preserve everyone's loss. A claim that a particular taper reliably prevents regain needs its own evidence.
A clinician may individualize treatment when side effects, cost or response require a change. That clinical judgment should be distinguished from a regimen proven by these trials. The studies support discussing maintenance, but they do not supply a do-it-yourself schedule for spacing injections or changing amounts.
The current product label includes instructions for missed doses and reinitiation after interruptions. Those are product-specific safety instructions, not evidence that irregular dosing is an effective maintenance strategy. If a gap occurs, ask how to restart rather than assuming the previously tolerated dose remains appropriate. Wegovy prescribing information
Stopping is common, so follow-up needs to be realistic
A Danish registry study published in 2026 followed 157,822 first-time semaglutide users for obesity management. Using a prescription gap of at least 60 days to define discontinuation, the estimated 12-month discontinuation risk was 49%. Changing the allowed gap changed the estimate. Discontinuation study
This describes prescription persistence, not a randomized stopping experiment. It does not show that all those people regained weight, why each person stopped or whether a particular alternative would have worked. Its practical contribution is to show that interruptions and discontinuation are common enough to plan for openly.
If treatment may end, discuss what follow-up will remain available. Clarify which outcomes matter beyond weight, what symptoms or measurements should prompt contact, and which alternatives may be appropriate. A planned review after a change is more useful than waiting until a large regain has occurred.
What to take from the evidence
The STEP 1 extension shows substantial average regain after medication and structured support stopped. STEP 4 more directly demonstrates the difference between continuing semaglutide and switching to placebo while lifestyle support continues. Continued-treatment studies show that average weight effects can persist for years.
Together, these findings favor thinking about obesity treatment as ongoing care with a maintenance phase. They leave room for individualized decisions about tolerability, access, other health goals and alternative treatments. Our semaglutide guide's stopping section provides additional context for that discussion.
Sources
- STEP 1 extension, 2022: exploratory follow-up after medication and structured support ended.
- STEP 4, 2021: randomized withdrawal after an initial treatment period.
- STEP 5, 2022: two-year randomized continued-treatment results.
- SELECT weight analysis, 2024: longer-term weight outcomes in a cardiovascular-disease population.
- Discontinuation of Semaglutide Therapy for Obesity Management, 2026: Danish prescription-record analysis.
- Wegovy US prescribing information, June 2026: mechanism, maintenance indication and interruption instructions.