
Peptides
October 16, 2026
What the 2025 amycretin trial actually adds
On this page
The 2025 study of injected amycretin attracted attention for an estimated weight reduction of up to 24.3% over 36 weeks. That is a striking early result. It is also a number from one part of a small, multipart development study—not the average outcome of 125 people receiving one established treatment regimen.
Amycretin, now called zenagamtide, is a single molecule with activity at GLP-1 and amylin receptor systems, with calcitonin-receptor activity also demonstrated. The trial helped show that this molecular approach could produce substantial effects in people. Its design and withdrawals determine how confidently the result can be interpreted.
Reading the paper alongside its supplementary appendix gives a fuller account than the headline alone. The zenagamtide guide provides broader context; this article focuses on what the 2025 injected study contributed and which questions it left open.
This was an early safety and dose-development study
The randomized, placebo-controlled phase 1b/2a trial took place at a single research center in San Antonio, Texas. It enrolled adults aged 18–55 years with BMI between 27.0 and 39.9.
Across five parts, 125 participants were randomized: 101 to amycretin and 24 to placebo. Participants and investigators were masked to treatment assignment. The primary endpoint was the number of treatment-emergent adverse events, while pharmacokinetic measurements and relative weight change were secondary endpoints. Primary publication
That purpose matters. The trial was designed to learn how the candidate behaved across exposure levels and whether further development was justified. It was not a large confirmatory comparison against an established obesity medicine.
Calling it a safety-focused study does not make the weight result unimportant. It means the result should be interpreted within an early development setting, where sample sizes, dose schedules and follow-up are chosen partly to characterize a new candidate.
Five parts did not mean five equal comparisons
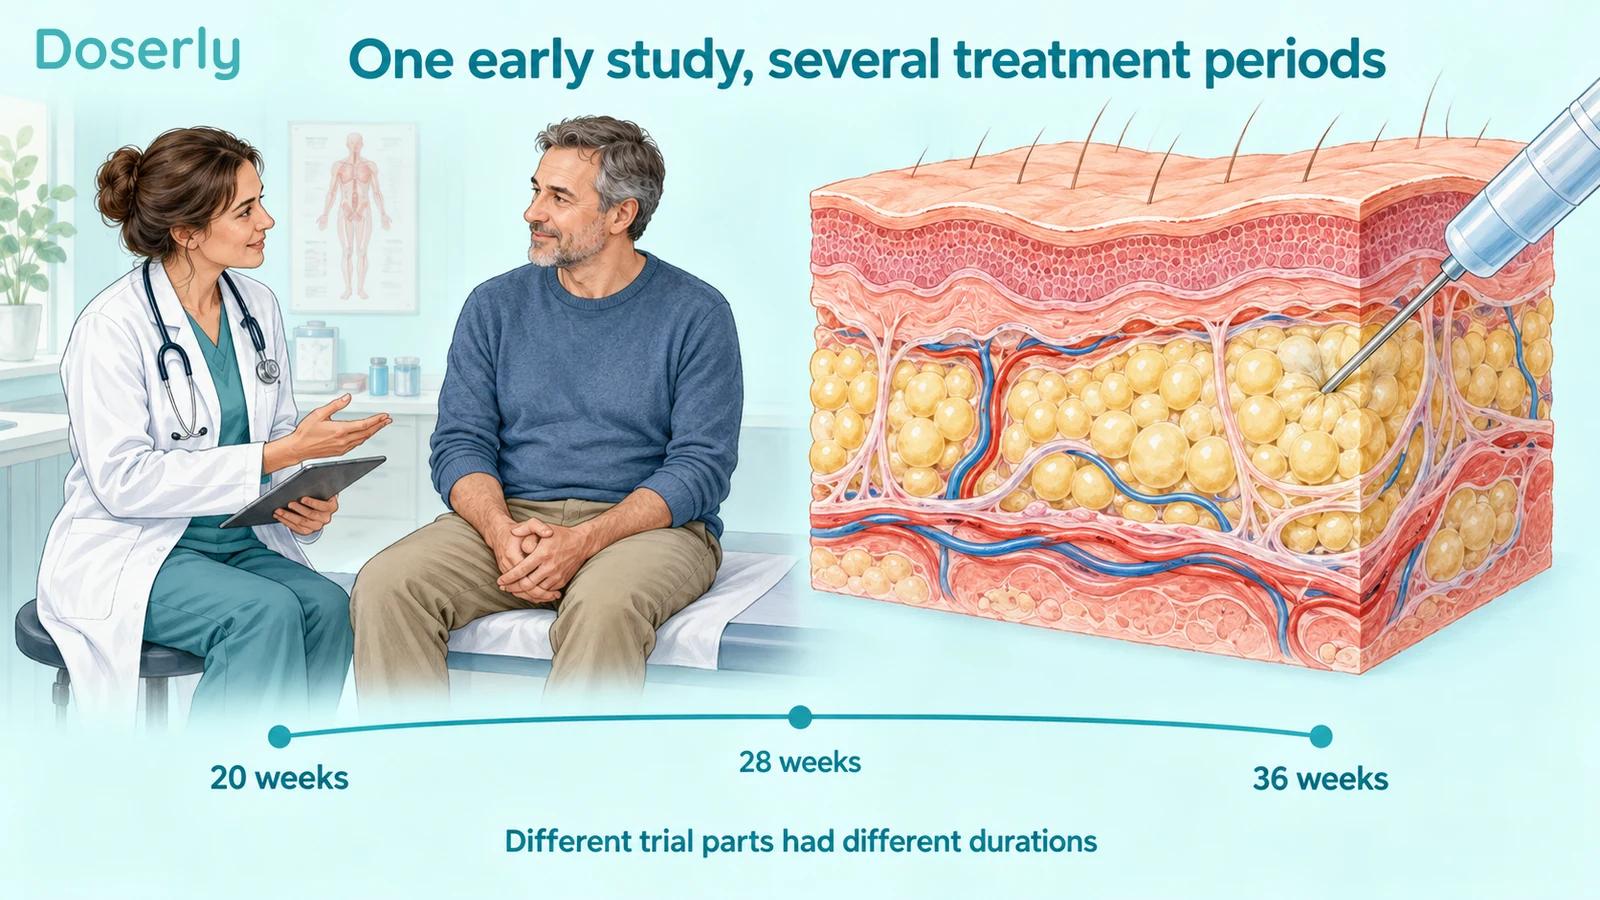
Part A investigated single ascending doses. The remaining parts examined repeated weekly administration, but they did not all use the same target dose or total duration.
Part B escalated toward 60 mg over a 36-week treatment period. Part C escalated toward 20 mg over 36 weeks. Part D studied a 5 mg maintenance target over 28 weeks, and Part E studied 1.25 mg over 20 weeks. In Parts C–E, the maintenance dose was sustained for the final 12 weeks.
These are descriptions of research regimens, not instructions for using an investigational product.
The appendix explains that the cohorts were introduced with staged safety observations and that participants could be replaced under specified procedures. It also distinguishes planned cohort sizes from the actual participant numbers reported in the main study flow. Trial appendix
This is why the total sample size cannot be attached to the largest-dose result. The 125 participants were distributed across different questions, including single-dose work. Each repeated-dose comparison involved a much smaller group.
What the weight estimates actually were
At week 36, the estimated mean weight change in Part B was −24.3% with amycretin and −1.1% with placebo. In Part C, also assessed at week 36, the estimates were −22.0% and +1.9%.
Part D reported −16.2% with amycretin and +2.3% with placebo at week 28. Part E reported −9.7% and +2.0% at week 20. Primary publication
The direction of change matters. Some placebo groups gained weight, so their active-versus-placebo differences are not the same as the active group's reduction from baseline.
For example, −22.0% versus +1.9% represents a raw difference of 23.9 percentage points between the reported group estimates. It does not mean participants in the active group lost 23.9% of their starting weight.
The time points matter too. Comparing the four active percentages as a simple dose-response ladder confounds dose with duration and escalation history. A 20-week result and a 36-week result do not offer equal observation time.
The appropriate conclusion is that several tested regimens produced substantial estimated weight reductions relative to their placebo comparisons. The trial did not establish the best long-term regimen for routine care.
Estimated outcomes are not identical to observed outcomes for everyone
The paper describes the weight changes as estimated means. An estimate uses a specified statistical approach to summarize the treatment effect; it should not be narrated as though every randomized participant completed treatment and had a final measurement.
This distinction becomes especially important when many participants withdraw. Randomization protects the initial comparison, but it does not guarantee that later missing measurements are harmless.
A statistical analysis may use available observations and assumptions to address missing information. The credibility of the result then depends partly on those assumptions and on how sensitive the conclusion is to plausible alternatives.
The general framework is explained in the FDA's estimand guidance: researchers must define the treatment question and how events such as discontinuation affect it. An analysis of continued treatment and an analysis of a treatment strategy that includes stopping are not automatically the same question.
The 2025 result is therefore best described using the publication's own qualification—an estimated mean weight change—while keeping the withdrawal pattern visible.
The appendix makes withdrawal harder to dismiss
The primary paper explicitly reports a large number of withdrawals, many for reasons other than treatment-emergent adverse events. The supplement shows why a single sentence about “non-adverse-event reasons” is insufficient.
In Part B, the appendix lists ten amycretin participants who discontinued: six under adverse-event-related discontinuation and four under other reasons. The adverse-event entries include nausea and other symptoms at different stages of escalation.
The other-reason category includes personal circumstances and protocol-related decisions. One entry also describes withdrawal of consent involving an adverse event complicated by social or home concerns. In another trial part, a non-adverse-event withdrawal was described as multifactorial, involving social circumstances and nausea. Appendix Table S5
That does not justify reclassifying participants without the investigators' data. It does show that administrative categories can simplify a complicated experience.
There are two separate questions: why someone stopped, and what outcome information remained available afterward. A reason unrelated to drug tolerability may change the safety interpretation, but it does not erase the statistical problem of missing follow-up.
The research setting was unusually intensive
The appendix describes administration by site staff. After the first dose at each new level in the repeated-dose parts, participants remained at the site for safety monitoring for up to 96 hours. Later doses within each four-week level involved shorter observation visits.
This is useful context for both safety and participation. The study was designed to observe a new medicine closely. It was not a test of a finished weekly product used independently at home with ordinary clinic follow-up.
An intensive visit schedule can support careful measurements while also making participation demanding. Work, transportation and family circumstances can become important reasons for withdrawal. Those details should neither be ignored nor used to assume that every discontinuation was unrelated to treatment.
The study therefore provides evidence under structured research conditions. Later trials need to show how the regimen performs with a practical treatment schedule and in a broader population.
Tolerability needs more than the phrase “mostly mild”
The most common treatment-emergent adverse events were gastrointestinal. Most were mild or moderate and had resolved by the end of the study, according to the primary report.
That is informative, but severity and treatment continuation are different dimensions. A symptom classified as mild can still be persistent, unpleasant or incompatible with someone's willingness to continue.
The appendix lists individual discontinuation events, including nausea, vomiting and dyspepsia. It also records an episode described as obstructive gallstone pancreatitis in Part C, classified in that table as non-serious and mild.
Those classifications should be reported accurately rather than replaced with assumptions based on the event's name. At the same time, a small trial cannot estimate the long-term frequency of uncommon events reliably. The event supports careful later surveillance; it does not establish a population risk rate or prove causation by itself.
The most balanced reading keeps common symptoms, individual clinically important events and withdrawal patterns in view together.
Exposure measurements support the weekly development strategy
The study also measured amycretin concentrations in blood. The appendix reports terminal half-life estimates broadly around three to four days across the evaluated settings, supporting the investigation of repeated weekly administration.
Pharmacokinetics helps explain whether a candidate achieves sustained exposure and how concentration changes with dose. It does not establish the exact duration of appetite effects or a personal schedule for missed doses.
The appendix's pharmacokinetic tables also show different numbers of participants contributing to different measurements. A count in a steady-state exposure table should not automatically be treated as the number completing the entire clinical trial.
That distinction is another reason to read table headings and footnotes. The denominator may refer to randomized participants, treated participants, available samples or a particular analysis set. Those groups can differ substantially in an early multipart study.
The study did not establish human muscle or metabolic protection
The molecular rationale is supported by preclinical experiments in cells and animals. Those studies examined receptor activity, food intake, energy expenditure and other metabolic outcomes. Primary preclinical report
They are not interchangeable with the human weight findings. A large reduction on a scale does not identify how much fat or lean tissue changed, and it does not demonstrate preserved strength or physical function.
Similarly, a rodent finding about energy expenditure cannot be used to explain the human result as proven prevention of metabolic adaptation. The clinical study would need appropriate human measurements to support that mechanism.
The 2025 trial's main contribution was early clinical evidence for the intact molecule. It did not validate every proposed advantage associated with targeting GLP-1 and amylin pathways together.
Later studies add evidence without rewriting this one
The name zenagamtide now links the early amycretin work to newer reports. A 2026 subcutaneous phase 2 publication studied 262 randomized adults with type 2 diabetes for 36 weeks, with HbA1c change as the primary endpoint. It demonstrated glucose-lowering effects relative to placebo across the tested doses. 2026 phase 2 publication
That is an important expansion into a different population and clinical question. It does not retroactively enlarge the 2025 cohorts or remove their withdrawals.
The oral amycretin phase 1 paper is also a separate experiment. Its findings cannot be substituted for the injected trial simply because the active molecule has the same name. Oral phase 1 publication
The 2025 injected-study registration helps keep these reports connected to the correct experiment.
What the result genuinely contributes
The trial established a substantial early weight signal for a single molecule designed to act across related appetite and metabolic pathways. It also characterized exposure and identified tolerability issues worth investigating in larger studies.
The next evidence needs are concrete: larger and more diverse populations, longer follow-up, transparent handling of discontinuation, practical regimens and outcomes beyond total weight. Active-comparator studies would be needed to establish advantages over other treatments.
The 24.3% estimate is worth understanding because it helped justify further development. Its value is clearest when it remains attached to the small cohort, 36-week escalation design and withdrawal limitations that produced it.
Sources
- 2025 injected amycretin primary publication.
- Peer-reviewed supplementary appendix.
- Injected-study registration.
- Separate oral phase 1 publication.
- Primary preclinical receptor and animal study.
- 2026 subcutaneous zenagamtide diabetes trial.
- FDA estimand and sensitivity-analysis guidance.