
TRT
October 16, 2026
Injection frequency and the smooth-curve promise
On this page
A graph with fewer peaks and valleys can make a testosterone schedule look obviously better. The line rises less after each injection, falls less before the next one, and seems to promise steadier energy, fewer side effects and simpler estrogen management. It is an appealing picture, especially for someone who feels distinctly worse toward the end of an injection interval.
There is real pharmacology behind changing injection frequency. There is also a gap between changing a blood concentration curve and proving that a particular schedule improves someone's life. “More frequent” describes an administration pattern. It does not, by itself, establish the right total dose, a safer hematocrit, preserved fertility or a better mood.
The useful question is therefore specific: what problem is a proposed schedule change intended to solve, and how will the patient and clinician know whether it worked? That question leaves room for genuine improvements without turning the smoothest possible line into the goal of treatment.
Why an injection does not behave like an on-off switch
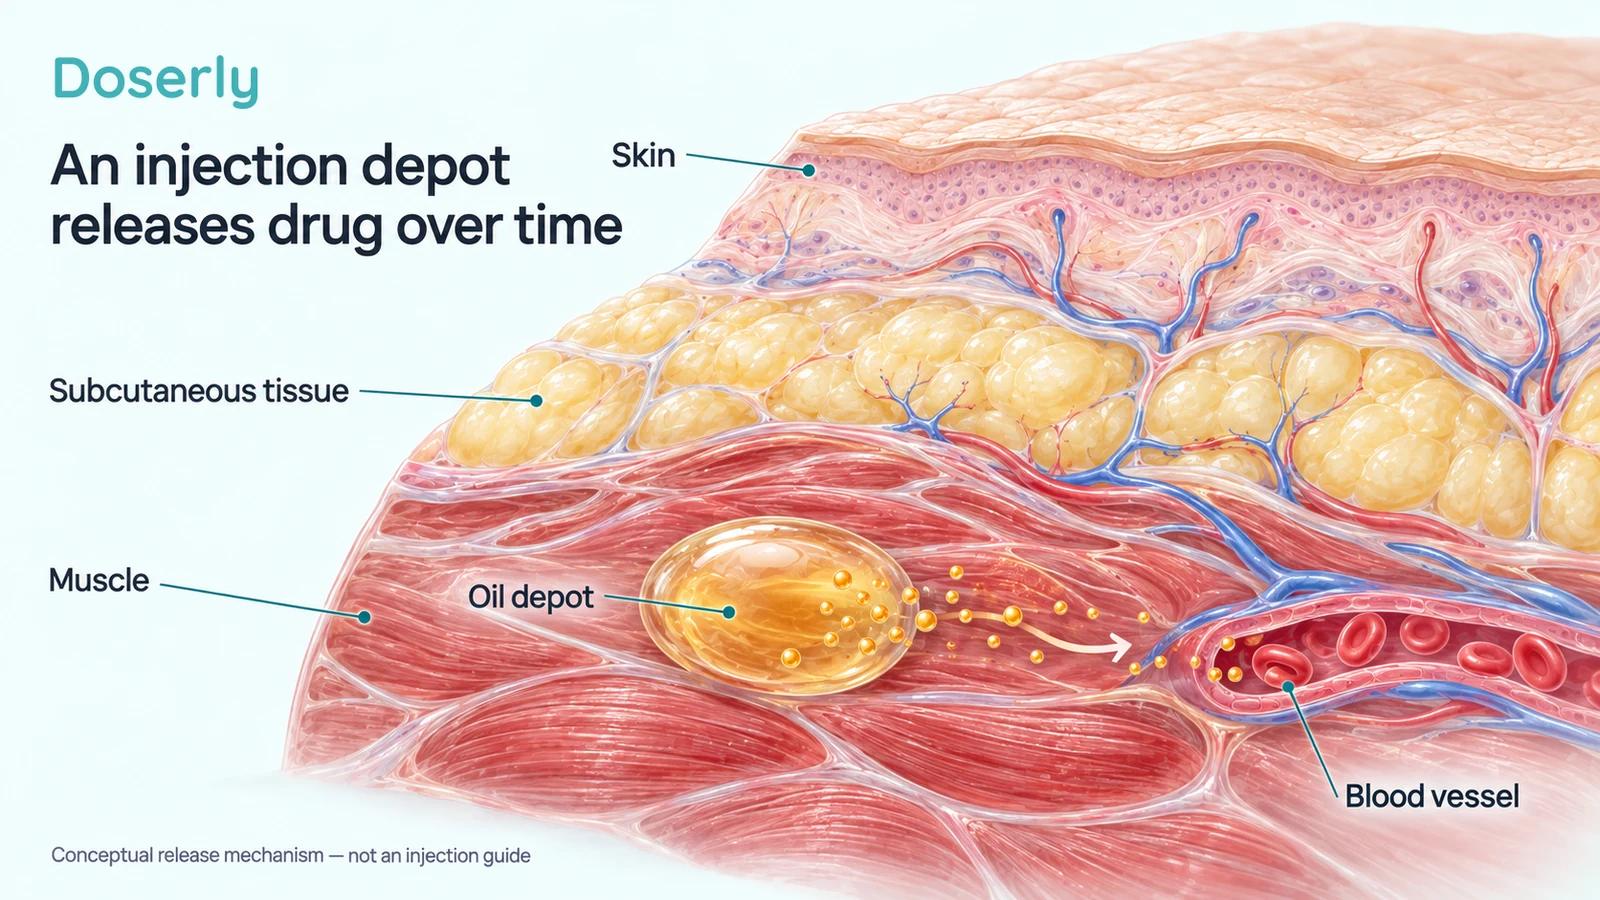
Testosterone cypionate and enanthate are ester formulations used to extend drug delivery. After an oil-based injection, release and absorption take time; the body then processes the ester and testosterone. A new injection can therefore arrive while earlier treatment is still contributing to circulating hormone. The size of each administration, the interval, formulation, route and individual handling all affect the resulting exposure.
An older but informative cypionate pharmacokinetic study followed 11 men with hypogonadism after a 200 mg intramuscular injection. Testosterone rose markedly, with peak values over days two to five, then declined toward baseline near the end of the two-week interval. This was a small study of one regimen, not a comparison of every modern injection schedule. Its continuing value is the demonstration that the same person can have substantially different results depending on when blood is drawn.
The milligram amount in that experiment is a description of research, not a suggested prescription. It also helps explain why a result obtained soon after an injection cannot simply be compared with a result obtained just before the next one. Both samples may be accurate while answering different questions about exposure.
A smaller injection is not necessarily less treatment
People sometimes describe a split schedule as a lower dose because each injection contains less medication. That leaves out how often it is given. The amount per administration and the total prescribed amount over a defined period are separate quantities.
If a clinician divides an unchanged total into smaller, more frequent administrations, the intended change may be the distribution of exposure. If the total amount also increases or decreases, the comparison is no longer about frequency alone. Changing route or formulation introduces another difference. A report of feeling better after “splitting the dose” can be sincere while still leaving several possible explanations.
This distinction matters when reading before-and-after stories. Did the person keep the same total prescribed amount? Were blood tests taken at comparable points? Did a missed dose, new medicine or change in sleep occur at the same time? Those details determine whether the account can reasonably support a claim about frequency.
A clinician can deliberately change more than one variable when care requires it. The point is to describe those changes accurately afterward. A smaller amount in the syringe is not evidence that total exposure fell, and a higher trough result is not automatically evidence that the new regimen is excessive.
What the weekly-versus-every-other-week study actually found
A comparative study published online in 2021 examined 263 men receiving either 100 mg intramuscular testosterone weekly or 200 mg every other week. Laboratory outcomes were evaluated at six months.
In the reported subgroup with baseline hematocrit below 54%, hematocrit subsequently exceeded that threshold in 1 of 102 men on the weekly regimen and 4 of 51 on the every-other-week regimen. That difference supports taking schedule seriously when discussing erythrocytosis, an increase in red blood cells. The study did not find significant between-group differences in the increases in total testosterone, free testosterone, estradiol or PSA.
These results do not establish that progressively more frequent injections are always safer. The comparison was weekly versus every other week, not daily versus twice weekly. It was not a randomized trial establishing a frequency-only causal effect, and the hematocrit result involved few events in a subgroup. It also cannot tell an individual whether their symptoms will improve.
The careful conclusion is useful enough: particular regimens can have different safety profiles, but a finding for two schedules cannot be extended indefinitely along a “more frequent is better” ladder.
Weekly subcutaneous treatment answers a different question
Subcutaneous administration places medication in tissue beneath the skin; intramuscular administration places it in muscle. Route and frequency are often discussed together online, even though they are distinct choices.
A 52-week study of a subcutaneous enanthate autoinjector was open label and single arm. With weekly treatment and dose adjustment, 92.7% of participants achieved the study's average testosterone concentration target at week 12. That supports the ability of this particular system to provide replacement exposure. There was no randomized daily-injection group establishing that a still flatter profile would deliver better symptoms or fewer long-term harms.
A separate 26-week safety study included 133 men using the subcutaneous enanthate system. Increased hematocrit of at least 52% was reported in 10 participants, and average blood pressure increased. A formulation can deliver relatively stable concentrations and still need surveillance for systemic effects.
The different hematocrit thresholds in these studies also matter. A study reporting values of at least 52% cannot be casually ranked against one reporting values above 54%. Populations, follow-up and ascertainment differ as well. Comparing the percentages without those details creates an appearance of precision that the evidence does not support.
Doserly's testosterone cypionate guide provides formulation background. Product and route instructions still need to come from the actual prescription and device information; an autoinjector should not be repurposed into a different schedule on the strength of a general discussion about splitting injections.
A simulation is an explanation, not a personal laboratory result
A smooth curve on a calculator usually reflects a model. It may assume a fixed absorption pattern, a particular half-life and perfectly timed administrations. Those assumptions can illustrate why overlapping smaller doses might narrow fluctuations. They cannot establish the person's measured concentrations, tissue response or symptom trajectory.
Even a graph drawn from actual research often represents a group average. A gentle average line can conceal people with different peak timing and different concentrations. Conversely, visible variation does not automatically mean a regimen is failing. The important question is whether exposure, clinical benefit and adverse effects are acceptable for that individual.
Before treating a graph as a reason to change treatment, identify what it depicts: measured or simulated data, which formulation and route, what population, and whether total exposure was held comparable. Then ask whether the study measured the outcome being promised. A testosterone curve cannot itself measure fatigue, sexual function, blood pressure or treatment burden.
This is especially relevant to claims that a flatter curve will “solve estrogen.” The weekly-versus-every-other-week study did not show a significant difference in the increase in estradiol. A plausible mechanism for changing peaks is insufficient evidence for a universal estrogen benefit or for adding an aromatase inhibitor.
Blood-test timing can make a successful change look unsuccessful
A trough is a concentration measured near the end of an interval, before the next administration. A midpoint measurement samples a different part of the interval. They are not interchangeable.
The Endocrine Society's 2018 guideline describes midpoint testing for injectable cypionate or enanthate. The Xyosted prescribing information, by contrast, specifies a trough seven days after the most recent dose following six weeks of treatment or adjustment. These instructions belong to particular treatment contexts. They are not competing universal rules that a patient should choose between independently.
When the interval changes, the old blood-draw appointment may no longer represent the same point in treatment. Recording the last administration's date and time allows the clinician to interpret that difference. If a new schedule produces a higher trough but a lower peak, one isolated result cannot describe both changes.
A meaningful comparison therefore starts with an agreed sampling plan. It also allows the prescribed regimen time to settle before a routine assessment, unless a safety concern requires earlier review. Repeatedly moving the schedule and the sampling window can turn a solvable clinical question into a series of incomparable numbers.

The practical cost of a schedule counts too
A schedule that looks elegant mathematically may be harder to carry out. More administration events mean more occasions to organize supplies, follow the prescribed technique, dispose of sharps and remember what has already been given. Someone else may find smaller, more frequent administrations easier to fit into a routine. Neither preference can be read from a hormone graph.
A useful treatment record distinguishes a scheduled administration from a completed one. It records deviations plainly rather than retroactively making the calendar look perfect. If a dose was late or missed, the clinician needs that fact to interpret symptoms and laboratory results. The appropriate response to a missed administration is product- and prescription-specific; it should not be improvised by doubling or redistributing doses.
There is also an interpretation cost to constant changes. If a person adjusts frequency every few days in response to energy, sleep or a forum post, it becomes difficult to know what regimen was actually evaluated. Agreeing in advance on the symptom being followed and the review point makes the information more usable.
For example, “I feel bad before my next injection” becomes more informative when the record identifies what “bad” means, when it starts, whether it repeats across intervals and what else changed. That pattern can support investigation. It still does not prove that every episode is caused by a testosterone trough.
The safety plan should survive the schedule change
Blood pressure and hematocrit do not stop mattering because injections are smaller. The FDA's 2025 class-wide labeling action required blood-pressure information for testosterone products. A frequency change is not evidence that this concern has disappeared.
Likewise, exogenous testosterone can suppress reproductive function. A schedule optimized for a serum curve is not a validated fertility-preservation strategy. Fertility goals need their own discussion before treatment decisions, rather than being inferred from a lower peak or a reassuring testosterone result.
The follow-up conversation can stay focused: what is the target symptom, what changed in total prescribed exposure, when will blood be sampled, and which safety measurements will be reviewed? If the initial problem persists despite adequate replacement, the next step may be to investigate other contributors rather than keep making the curve flatter.
Injection frequency is a useful clinical variable. Its value comes from solving an identified problem within a monitored treatment plan. The strongest evidence that a change helped is a coherent combination of correctly timed results, meaningful benefit, manageable administration and acceptable safety—not the visual smoothness of a line.
Sources
- Hormone kinetics after intramuscular testosterone cypionate
- Comparative assessment of outcomes and adverse effects using two different intramuscular testosterone therapy regimens: 100 mg IM weekly or 200 mg IM biweekly
- A 52-Week Study of Dose Adjusted Subcutaneous Testosterone Enanthate in Oil Self-Administered via Disposable Auto-Injector
- Safety of a New Subcutaneous Testosterone Enanthate Auto-Injector: Results of a 26-Week Study
- Xyosted prescribing information
- Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline
- FDA Issues Class-Wide Labeling Changes for Testosterone Products