
Peptides
October 16, 2026
Eloralintide and cagrilintide: meaningful differences without a premature winner
On this page
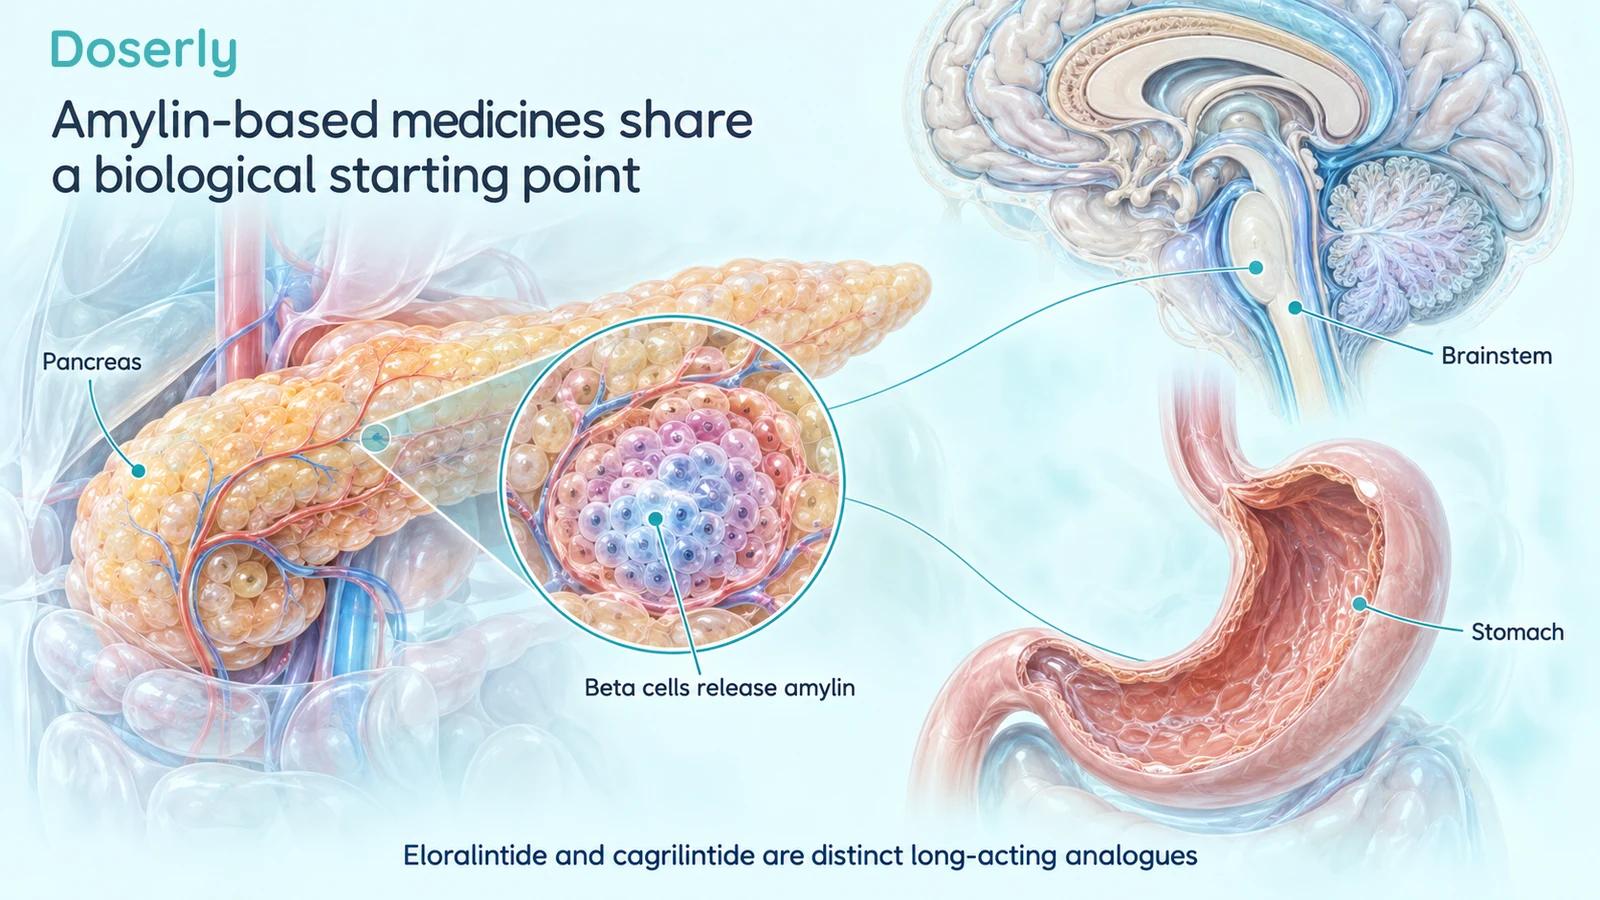
Eloralintide and cagrilintide are both longer-acting analogues of amylin, a hormone released by the pancreas after eating. That shared starting point makes them natural candidates for comparison. Both are being investigated for weight management, and both have human evidence of weight reduction.
They are nevertheless different molecules. Their receptor activity differs, their development programs aren't identical, and the most familiar numbers come from studies with different populations, durations and analyses. Some cagrilintide headlines also describe CagriSema, a combination with semaglutide, rather than cagrilintide alone.
A useful comparison can explain those differences without pretending that a human head-to-head trial has already selected a winner. We'll look at mechanisms, the main clinical studies and what would be needed to answer the questions patients actually care about. Our eloralintide guide and cagrilintide guide provide more detail on each compound.
What do they share?
Amylin participates in appetite regulation and the body's response to meals. Pancreatic beta cells release it alongside insulin. Longer-acting analogues aim to produce sustained effects through related signaling while remaining suitable for use as pharmaceutical products.
Both eloralintide and cagrilintide were designed to last longer than native amylin. Their shared hormone family helps explain why both have been studied for weight management. It doesn't make their doses interchangeable or their unwanted effects identical. Eloralintide discovery research
A helpful distinction is between belonging to a drug family and having the same clinical profile. Two medicines can address a related biological system while differing in exposure, receptor preference, dose-response relationship and tolerability. Those differences are reasons to study each one, not reasons to assume superiority.
How does receptor activity differ?
An amylin receptor is a complex formed by the calcitonin receptor and an accessory protein called a RAMP. Different RAMP partners create different receptor subtypes. Eloralintide showed a preference for human AMY1 in the discovery assays, while cagrilintide has broader amylin and calcitonin receptor activity.
In those assays, eloralintide was about 12 times more potent at human AMY1 than at the human calcitonin receptor. That is a concentration-response finding in cells, not a ratio of treatment benefit in patients. Activity at the other tested receptors was still observed. Comparative pharmacology
The distinction gives researchers hypotheses about effectiveness and tolerability. It doesn't establish that broader activity is necessarily undesirable or that more selective activity always produces better outcomes. Clinical effects depend on the entire molecule and how much reaches different tissues over time.
“Selective” is therefore a useful pharmacological description, not a clinical quality rating.
What did cagrilintide show as a single treatment?
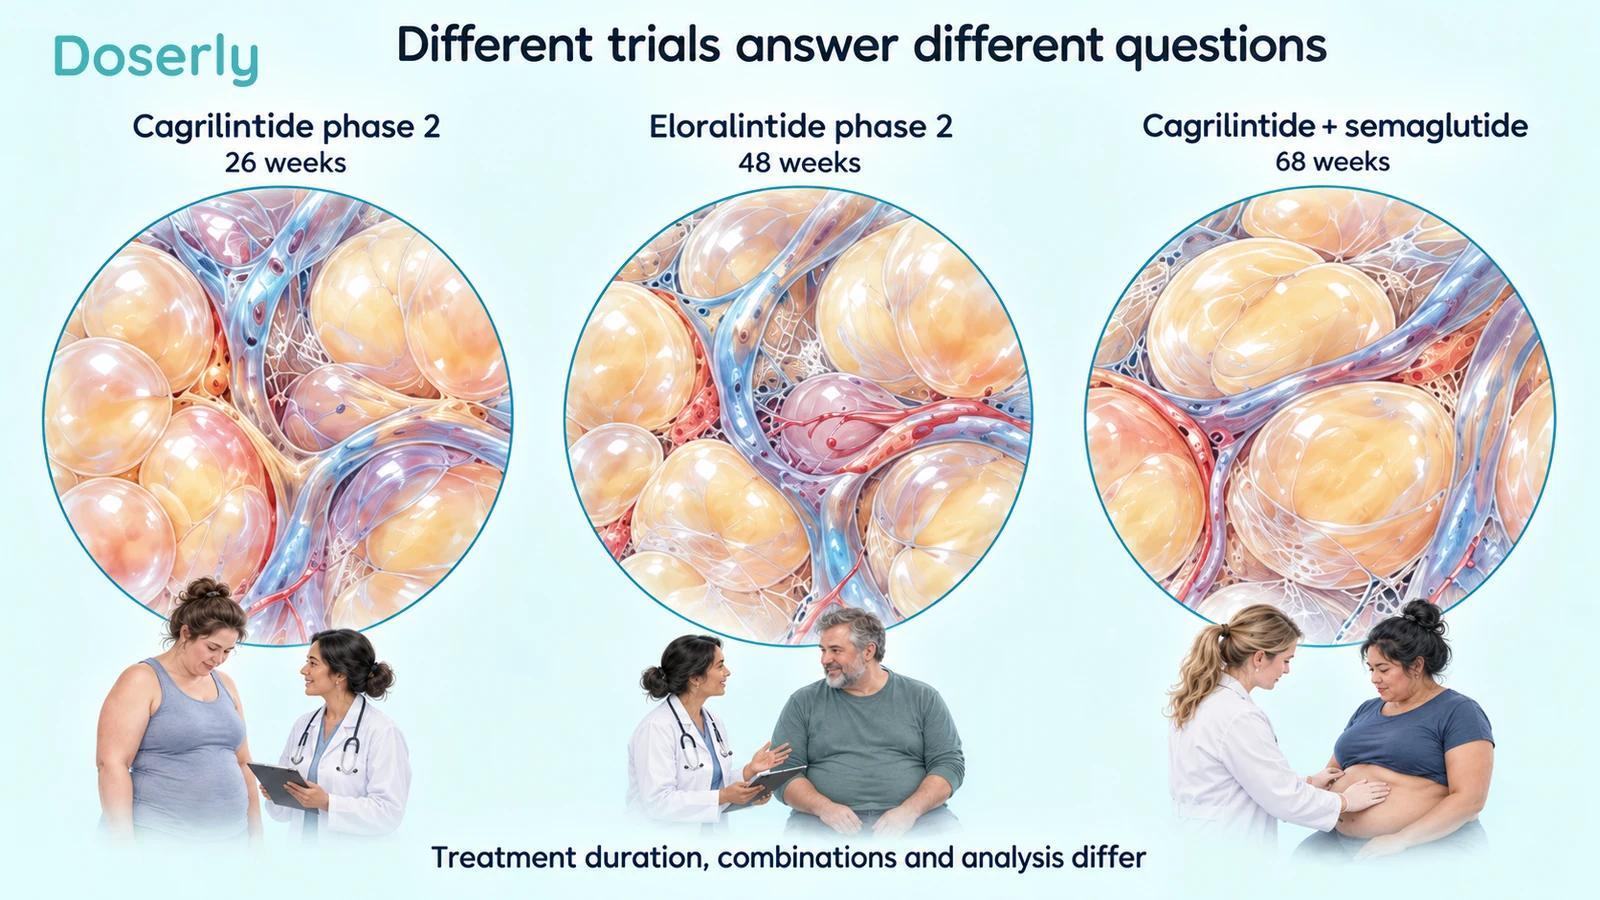
The 2021 phase 2 trial randomized 706 adults across cagrilintide groups, liraglutide and placebo. Participants had obesity, or overweight with hypertension or dyslipidemia, and didn't have diabetes. Treatment lasted 26 weeks.
Under the trial-product estimand, which assumed adherence to treatment, average weight reduction ranged from 6.0% to 10.8% across cagrilintide groups, versus 3.0% with placebo. The highest cagrilintide dose also produced more weight loss than the liraglutide comparator, which was actually randomized within that study. Cagrilintide phase 2 trial
That is evidence for cagrilintide's effect in its own trial setting. It is also an example of a comparison the design could support: cagrilintide versus a treatment included in the same randomized experiment.
It isn't evidence against eloralintide, which wasn't a treatment arm. The fact that both studies measured percentage weight change doesn't turn them into one shared trial.
What did eloralintide show?
Eloralintide's 48-week phase 2 study randomized 263 adults with obesity, or overweight and a related health condition, without type 2 diabetes. It evaluated several schedules against placebo.
The reported efficacy-estimand averages ranged from roughly 9% to 20% weight loss, compared with 0.4% on placebo. Nausea and fatigue varied considerably between groups. Eloralintide phase 2 trial
These results support continued development, but they shouldn't be placed beside the cagrilintide 26-week result as if the drugs had been compared under identical conditions. Eloralintide was observed for substantially longer. The study populations, schedules and analytical questions also differed.
A higher number can generate a hypothesis worth testing. It cannot, by itself, establish that the molecule is more effective for the same patient over the same duration.
Why CagriSema needs its own category
CagriSema combines cagrilintide with semaglutide, a GLP-1 receptor agonist. Its result reflects the combination strategy. Calling that result “cagrilintide weight loss” omits an active component.
REDEFINE 1 randomized 3,417 adults without diabetes to CagriSema, semaglutide alone, cagrilintide alone or placebo for 68 weeks. Under the treatment-policy estimand, the combination group had an estimated 20.4% weight reduction versus 3.0% with placebo. REDEFINE 1 primary report
The trial's separate component arms help investigate the value of combining two treatments. That is much more informative than simply adding their percentages from unrelated studies. It still doesn't compare CagriSema directly with eloralintide.
It also doesn't establish that every amylin–GLP-1 pairing behaves like CagriSema. Changing either component, its formulation or the schedule creates another treatment question.
The eloralintide combination has a separate population too
In September 2026, Lilly reported a 48-week phase 2b study of eloralintide plus tirzepatide in 367 adults with obesity or overweight and type 2 diabetes. The highest combination group had a reported mean weight reduction of 23.3%, compared with 14.8% for tirzepatide alone, under the sponsor's efficacy estimand. Treatment discontinuation because of adverse events ranged from 10.8% to 27.0% across combination groups. These are sponsor-disclosed results, not a peer-reviewed full report in the evidence reviewed here. Original EloraTZP disclosure
This makes the comparison problem more specific. Eloralintide alone, eloralintide plus tirzepatide, cagrilintide alone and cagrilintide plus semaglutide are four different strategies. The combination studies also differ in diabetes status, follow-up and analysis. Placing 23.3% beside 20.4% would therefore combine several differences at once, rather than isolate the choice of amylin component.
A useful clinical comparison would ask which regimen fits a defined population and how benefit compares with symptoms and persistence. It would not credit an entire combination result to the amylin molecule alone. Even a direct comparison between two combinations would compare the full regimens; it would not necessarily establish which individual component explained a difference. That narrower causal question requires the appropriate component arms and analysis.
Why subtracting placebo doesn't solve everything
Subtracting the placebo group's change can help show the additional average change associated with treatment within a study. It doesn't remove every difference between studies.
Placebo responses can reflect lifestyle support, participant selection, study procedures and other influences. Follow-up duration also changes the opportunity to lose weight. Statistical adjustment can't make an unmatched comparison equivalent to randomizing the same eligible population between two drugs.
The analysis itself matters. A treatment-policy estimate addresses outcomes under a strategy that includes specified events such as discontinuation. A trial-product or efficacy estimate can address a different scenario about treatment adherence. Comparing numbers that answer different questions adds another source of ambiguity. FDA estimand guidance
For a meaningful comparison, first align the population, treatment duration and question. Only then does the difference between percentages start to become interpretable.
Does eloralintide cause less nausea?
The early multiple-dose eloralintide study reported nausea in 6 of 73 active-treatment participants, about 8%. That was a small, 12-week phase 1 study. It isn't a universal nausea rate for the medicine. Phase 1 report
In the larger phase 2 trial, nausea ranged from 11% to 64% across eloralintide groups, compared with 14% with placebo. The higher range shows why schedule and population need to accompany tolerability claims. Phase 2 report
The discovery paper also compared conditioned taste avoidance in rats receiving eloralintide or cagrilintide. That experiment can inform a tolerability hypothesis, but rats aren't reporting nausea the way trial participants do. An animal behavioral measure isn't a human head-to-head safety endpoint. Preclinical comparison
A useful human comparison would use similar symptom collection, follow-up and treatment-adjustment rules. It would report severity, duration and discontinuation, not just whether nausea occurred at least once.
What about muscle preservation?
Some discussions draw on animal body-composition findings to claim that one drug preserves muscle better. The discovery work included diet-induced-obesity rat experiments in which body composition was measured. Those results cannot establish comparative muscle preservation in humans. Animal body-composition experiments
Even human “lean mass” measurements need interpretation. Lean mass isn't a direct measurement of muscle strength or physical function. A useful clinical comparison would examine body composition alongside outcomes such as strength, mobility, nutrition and how participants feel.
Weight loss alone doesn't identify which tissues changed. Nor does a percentage of weight loss classified as lean mass establish the clinical importance of that change for every person.
This is particularly relevant for older adults or people already at risk of frailty. The desired outcome is improved health and function, not merely a favorable-looking number in a body-composition chart.
Can the same number of milligrams be compared?
No. Milligrams measure mass, not equivalent biological activity. Different peptides have different molecular properties, receptor activity, absorption and persistence. Equal masses need not produce equal exposure or effects.
The trial doses identify the groups researchers tested. They don't provide a conversion between eloralintide and cagrilintide. A lower numerical dose doesn't establish greater potency in a patient, and a higher numerical dose doesn't establish greater risk.
The same applies to schedule. Two once-weekly medicines may have different concentration patterns between administrations. “Weekly” is a practical interval, not a statement that the molecules behave the same way.
For readers, a proposed conversion based only on trial milligrams should be treated as an unsupported assumption. Comparative dosing requires appropriate pharmacological and clinical evidence.
What would a fair comparison look like?
A direct trial could enroll one clearly defined population and randomly assign participants to the two treatments. It would use justified schedules, comparable follow-up and the same outcome measurements.
The question should be specified before the results are known. Is the aim greater weight loss, fewer troublesome symptoms, better treatment persistence or a better balance of these outcomes? Different patients might prioritize these differently.
A well-designed comparison would also preserve information after people stop treatment where possible. Otherwise, a favorable average could disproportionately describe participants able to tolerate sustained exposure.
For clinical usefulness, the trial should report both the average change and how many people achieve meaningful goals, alongside symptoms and function. There may be no single winner across every outcome.
What can be concluded now?
Both drugs have evidence supporting amylin-based approaches to weight management. Cagrilintide has been studied alone and in a large randomized combination program. Eloralintide offers a different receptor profile and promising 48-week weight-loss findings.
The evidence supports describing these differences. It doesn't support declaring one universally superior based on separate headline percentages, a receptor label or a rat experiment.
For a person discussing treatment options, the useful comparison begins with their condition, existing therapy, goals and tolerance of unwanted effects. It then asks which evidence actually matches that situation. The cagrilintide guide and eloralintide guide can help prepare that discussion as the research develops.
Sources
- Eloralintide (LY3841136): from discovery to clinical proof of concept — translational and human phase1, 2025.
- Eloralintide: Phase 1 proof of concept — human rct, 2026.
- Eloralintide for obesity: a 48-week phase 2 randomized trial — human rct, 2025.
- Once-weekly cagrilintide for weight management: phase 2 dose-finding trial — human rct, 2021.
- Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity — human rct, 2025.
- ICH E9(R1): Estimands and Sensitivity Analysis in Clinical Trials — regulatory guidance, 2021.
- Lilly EloraTZP phase 2b disclosure, September 30, 2026 — original sponsor disclosure, not a peer-reviewed full report.