
TRT
October 16, 2026
Enclomiphene Raises Testosterone: What the Trials Do and Do Not Establish
On this page
Enclomiphene is often described as a way to raise testosterone while keeping the body's own production working. That description reflects a real difference from testosterone replacement. It can also make the evidence sound broader than it is.
Clinical trials have shown increases in testosterone and preservation of sperm concentration in selected men with secondary hypogonadism. The harder questions concern how those findings translate into symptoms, long-term health, pregnancy and the choice of a particular product.
A useful reading of the evidence keeps both ideas together: a measurable hormone response is meaningful, but it does not answer every clinical question. The distinction helps explain why a medicine can produce favorable laboratory results and still face regulatory concerns.
What enclomiphene is trying to change
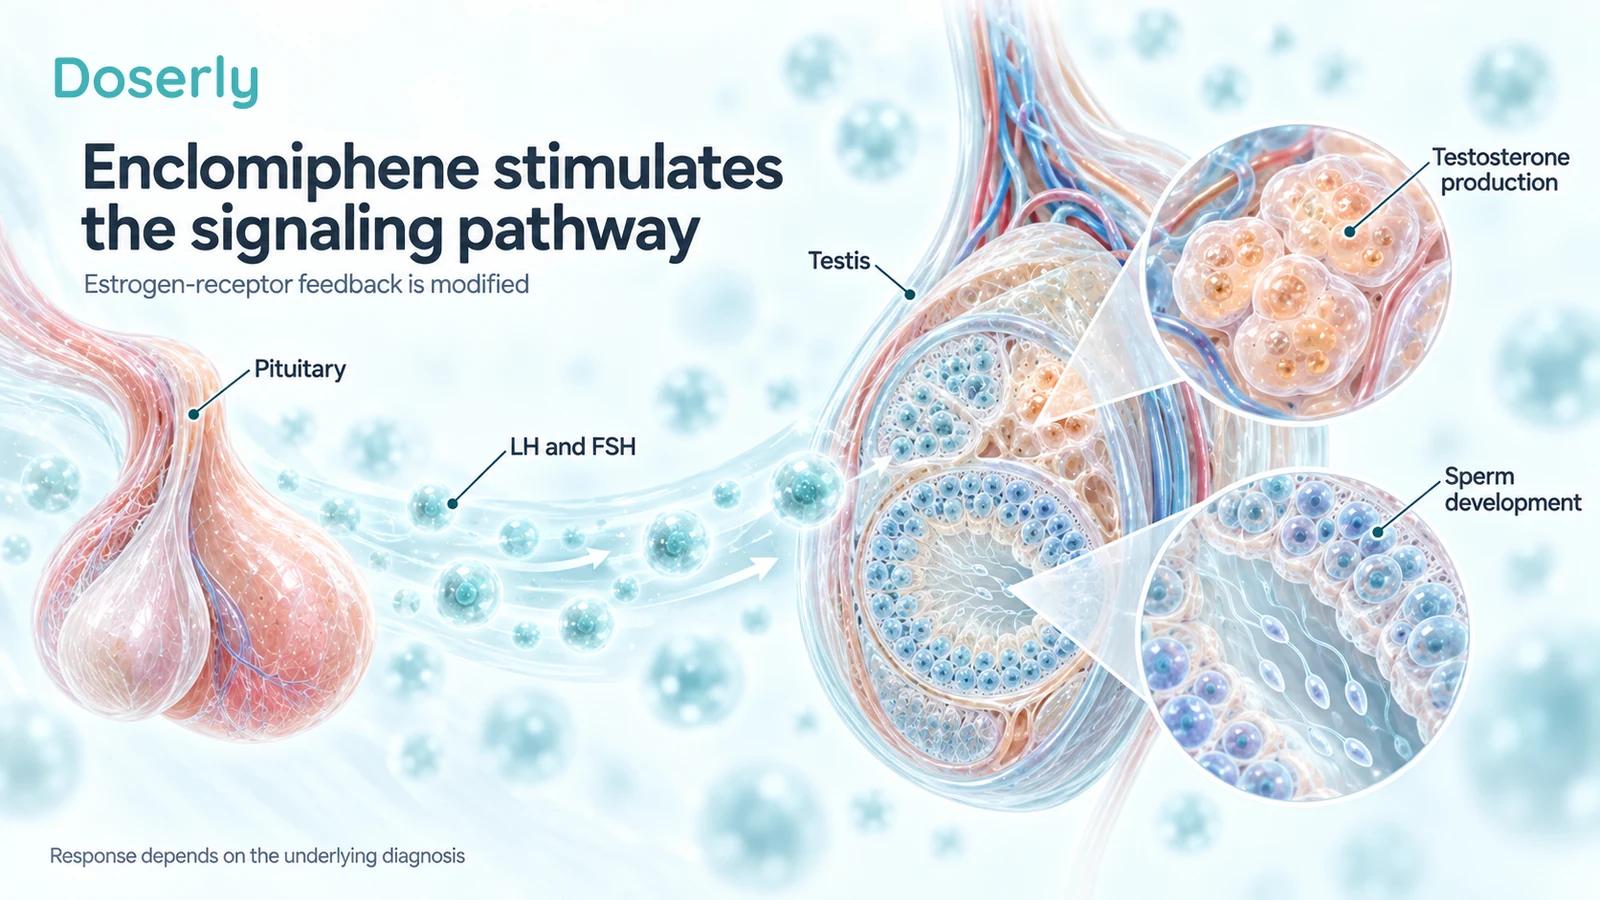
Enclomiphene is a selective estrogen receptor modulator, commonly shortened to SERM. Its intended effect in this setting is to modify estrogen feedback at the hypothalamic-pituitary level so the pituitary can release more gonadotropins: luteinizing hormone, or LH, and follicle-stimulating hormone, or FSH.
LH stimulates testosterone production in the testes. FSH contributes to the support of sperm development. This approach relies on a responsive hormonal pathway, whereas testosterone replacement supplies testosterone from outside the body.
The distinction appeared directly in randomized trials: enclomiphene increased LH and FSH, while testosterone gel reduced them. Both approaches could raise blood testosterone, but they did not produce the same effect on sperm concentration. Kim and colleagues
Calling this “natural testosterone” can obscure an important point: the response is still being produced by a medicine acting on hormone feedback. The word natural does not establish safety, suitability or a lasting effect after treatment ends.
It is related to clomiphene, but it is not the same product
Clomiphene citrate contains two geometric isomers, enclomiphene and zuclomiphene. They have the same chemical formula but differ in spatial arrangement. The CLOMID label describes the mixture and notes differences in their estrogen-related activity. CLOMID prescribing information
Isolating one component creates a different formulation to study. It does not mean that every clinical finding from clomiphene automatically applies to enclomiphene, or that removing the other isomer proves superior long-term safety.
This is especially relevant when comparing online accounts. One person may be describing prescribed clomiphene, another a compounded enclomiphene product, and another a combination containing additional drugs. Treating those experiences as if everyone received the same intervention makes the comparison unreliable.
Doserly's enclomiphene guide and clomiphene guide provide separate overviews. The names are similar enough that confirming the exact medication on the prescription is worthwhile.
Who entered the main trials?
The 2016 report described two parallel randomized, double-blind, placebo-controlled phase III studies in overweight men aged 18–60 with secondary hypogonadism. Participants had low or low-normal early-morning testosterone and low or normal LH on repeated testing.
After sixteen weeks, enclomiphene raised testosterone, LH and FSH and maintained sperm concentrations in the normal range. Testosterone gel raised testosterone but suppressed gonadotropins and markedly reduced spermatogenesis. Kim and colleagues
The population is central to interpreting the result. These were not trials in everyone who felt tired, in men with normal hormone testing seeking enhancement, or in all forms of testicular failure. Participants were selected for a hormonal pattern in which stimulating the pathway was biologically plausible.
A person with high LH and low testosterone may have a different problem: the pituitary is already signaling strongly, but the testes are not responding adequately. Increasing the signal may have limited benefit. Structural pituitary disease can also change what a SERM can achieve. AUA/ASRM guideline
This is why the primary versus secondary hypogonadism distinction is more useful than asking whether one drug is simply “better than TRT.”
What the earlier study adds
A randomized phase II trial reported in 2014 also compared enclomiphene with topical testosterone and assessed hormone and semen outcomes over approximately three months. Enclomiphene increased gonadotropins and testosterone while conserving sperm counts. Wiehle and colleagues
Consistency across studies strengthens confidence in the basic biological effect. It does not remove the limits of short follow-up or convert a semen measurement into a pregnancy outcome.
The study also illustrates why a trial report deserves more attention than a headline. Different analyses may include different subsets of participants depending on whether samples were collected and which endpoint was being examined. A percentage detached from its denominator can sound much more certain than the underlying data.
For a patient, the useful conclusion is that the approach has been tested in humans and can affect the intended pathway. The unanswered question is how well that evidence matches the individual's diagnosis and the outcome they want to improve.
Preserved sperm concentration is valuable—and specific
Avoiding the sperm suppression associated with exogenous testosterone is an important potential advantage for someone concerned about fertility. It is a more relevant finding than simply seeing testosterone rise.
But sperm concentration is only one part of reproductive assessment. It describes the number of sperm per unit of semen; it does not by itself describe every aspect of sperm function or the reproductive circumstances of a couple.
The main enclomiphene studies were designed around hormones and semen measures. They did not establish a reliable improvement in live-birth probability for men with infertility. Preserving a measured parameter during treatment also differs from treating an existing fertility problem successfully.
The AUA/ASRM guideline stresses that semen values above or below a reference limit do not by themselves determine whether a person can conceive. Its discussion of SERMs in selected infertile men with low testosterone should not be expanded into a claim that every SERM product has proven fertility efficacy. AUA/ASRM guideline
If having a child is the goal, say so explicitly. The TRT and fertility guide explains why the reproductive timeline and appropriate testing belong in the treatment decision.
Why regulators asked for more than a higher testosterone number
In 2018, the European Medicines Agency refused marketing authorization for EnCyzix, an enclomifene product intended for overweight men with hypogonadotropic hypogonadism. The application included four main studies involving 588 patients.
The agency acknowledged the increase in testosterone. Its concerns included the lack of evidence establishing improvement in clinically important manifestations such as libido, erectile function and other consequences of hypogonadism, together with a risk of venous thromboembolism. It concluded that the benefits had not been shown to outweigh the risks. EMA assessment
That decision does not mean the hormone measurements were imaginary. It shows the difference between demonstrating pharmacological activity and demonstrating a sufficiently favorable clinical benefit-risk balance for authorization.
It also does not prove that no individual can feel better. Individual improvement and a treatment effect established in an adequately designed trial are different forms of evidence. Both can matter in care, but they should not be described as interchangeable.
A response during treatment is not a permanent reset
The main phase III comparison measured outcomes after sixteen weeks of treatment. It was not a demonstration that every man's original condition had resolved permanently. Kim and colleagues
If someone describes enclomiphene as “restarting” the system, ask what they mean: a response while taking the drug, persistence after a short washout, or sustained recovery long after treatment ends. Those require different observations. A plan for reassessment should account for the underlying cause, rather than assuming a higher on-treatment result proves a lasting cure.
Availability is not approval
As checked in October 2026, no FDA-approved enclomiphene product was identified in the FDA drug-approval database search. FDA's May 2026 bulk-substance document lists enclomiphene citrate in Category 1, substances under evaluation for compounding. That listing is not a marketing approval for an enclomiphene medicine. FDA bulk-substance list
Compounding and product approval are separate regulatory questions. FDA explains that compounded drugs are not FDA approved and do not undergo its premarket review for safety, effectiveness and quality. FDA compounding questions and answers
A prescription, an online listing or a substance identifier therefore should not be presented as proof that a particular product has passed the approval process. Nor should a historical trial formulation be assumed identical to every preparation now offered.
Ask what exact product is being supplied, which pharmacy prepares it, and what evidence supports the proposed use. Local access rules can differ; the presence of a product in one setting does not establish authorization everywhere.
A symptom plan should accompany a laboratory plan
If treatment is being considered because of low libido, reduced sexual function or another symptom, define that problem before the first follow-up blood test. Otherwise a higher testosterone result can become the entire definition of success even when the original difficulty remains.
The Endocrine Society's diagnostic approach requires compatible symptoms and consistently low testosterone, not an isolated number. Evaluation of the cause is part of that process. Endocrine Society guideline

A useful follow-up asks whether the intended symptom changed, whether an adverse effect appeared, and whether another explanation remains relevant. It also asks whether the change is large enough to matter to the person taking the medicine.
For example, “my testosterone increased” and “my sexual symptoms improved enough that treatment feels worthwhile” are two different statements. A clinician needs both. Neither should be assumed from the other.
Safety uncertainty deserves a specific discussion
The EMA's clotting concern should be discussed in the context of personal history and the proposed treatment, rather than converted into an unsupported numerical risk estimate. Short hormone trials cannot answer every question about uncommon adverse events or prolonged exposure.
Likewise, a claim that enclomiphene has fewer side effects because it contains only one clomiphene isomer needs comparative clinical evidence. A plausible chemical explanation is not enough to establish the size of a safety advantage.
Ask which symptoms should prompt contact, what follow-up is planned and what would lead to stopping or changing treatment. A monitoring plan should be clear before an unexpected symptom occurs.
Do not respond to an unwanted effect by independently adding another hormone-modifying medicine. Combining treatments can change both the physiology and the ability to determine which intervention caused the problem. The evidence for one studied medicine does not automatically validate a multi-drug regimen.
What a careful decision looks like
The strongest starting point is a confirmed diagnosis, a clear treatment goal and an honest comparison of options. That includes the option of addressing a contributing condition when appropriate, rather than assuming that every low result requires the same hormonal intervention.
Before agreeing to treatment, consider asking:
- Does my hormone pattern resemble the population studied?
- Are we trying to improve symptoms, preserve sperm, or address an existing fertility problem?
- Which outcomes will we measure, and when will we reassess?
- What is known about this particular product, and what remains uncertain?
Keep copies of baseline results and record the exact formulation and changes. That makes later comparisons more meaningful and helps a second clinician understand what has actually been tried.
Enclomiphene's trial findings support a real effect on testosterone and gonadotropins, with preservation of sperm concentration in selected men. They do not establish a universal substitute for TRT, a guaranteed fertility treatment or a permanent hormonal reset. The evidence becomes most useful when its boundaries remain visible throughout the decision.
Sources
- Kim et al. Enclomiphene versus testosterone gel in secondary hypogonadism
- Wiehle et al. Enclomiphene and sperm preservation, phase II
- EMA: EnCyzix refusal assessment
- CLOMID prescribing information
- Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline
- AUA/ASRM Diagnosis and Treatment of Infertility in Men, amended 2024
- FDA: 503A bulk substances under evaluation
- FDA: Compounding questions and answers