
TRT
October 16, 2026
Clomiphene in Men: A Higher Testosterone Result Is Only Part of the Decision
On this page
Clomiphene can seem like an attractive alternative when a man has low testosterone and wants to preserve the possibility of children. It is taken by mouth, works through the body's hormone-signaling pathway, and has a longer history of clinical use than many newer products promoted in this space.
The evidence supports a real ability to raise testosterone in selected men. The decision becomes more complicated when the goal is symptom relief, treatment of infertility or years of continued use. Those outcomes need their own evidence and monitoring.
A useful conversation therefore starts with the reason for treatment: what are we trying to improve, and how will we know whether it has improved enough to justify continuing? A reassuring laboratory result is one part of that answer.
What clomiphene does—and what its approval means
Clomiphene is a selective estrogen receptor modulator, or SERM. In men, it can reduce estrogen-mediated feedback at the hypothalamic-pituitary level, increasing the release of LH and FSH. LH stimulates testosterone production by the testes; FSH helps support sperm development.
The AUA/ASRM guideline describes clomiphene as a commonly studied SERM in male infertility and allows selected hormone-stimulating treatments for infertile men with low testosterone. The recommendation is conditional and based on limited evidence. AUA/ASRM guideline
In the United States, clomiphene's approved indication is for ovulatory dysfunction in women desiring pregnancy. Use for male hypogonadism or infertility is off-label. Off-label does not mean that a clinician cannot consider it; it means the male indication is not the approved use described in the label. CLOMID prescribing information
That distinction should be explained plainly. Familiarity with a medicine does not eliminate the need to assess the evidence for the particular patient and purpose.
The starting hormonal pattern matters
Clomiphene relies on a pathway capable of responding. It is more biologically plausible when testosterone is low and the pituitary signal is low or inappropriately normal than when the testes are already receiving a strong signal but cannot respond adequately.
A high LH result alongside low testosterone can point toward primary testicular dysfunction. A low or normal LH result may suggest a different problem, but it does not by itself explain the cause. Structural pituitary conditions, medication effects and other clinical circumstances can change the evaluation and treatment choice. AUA/ASRM guideline
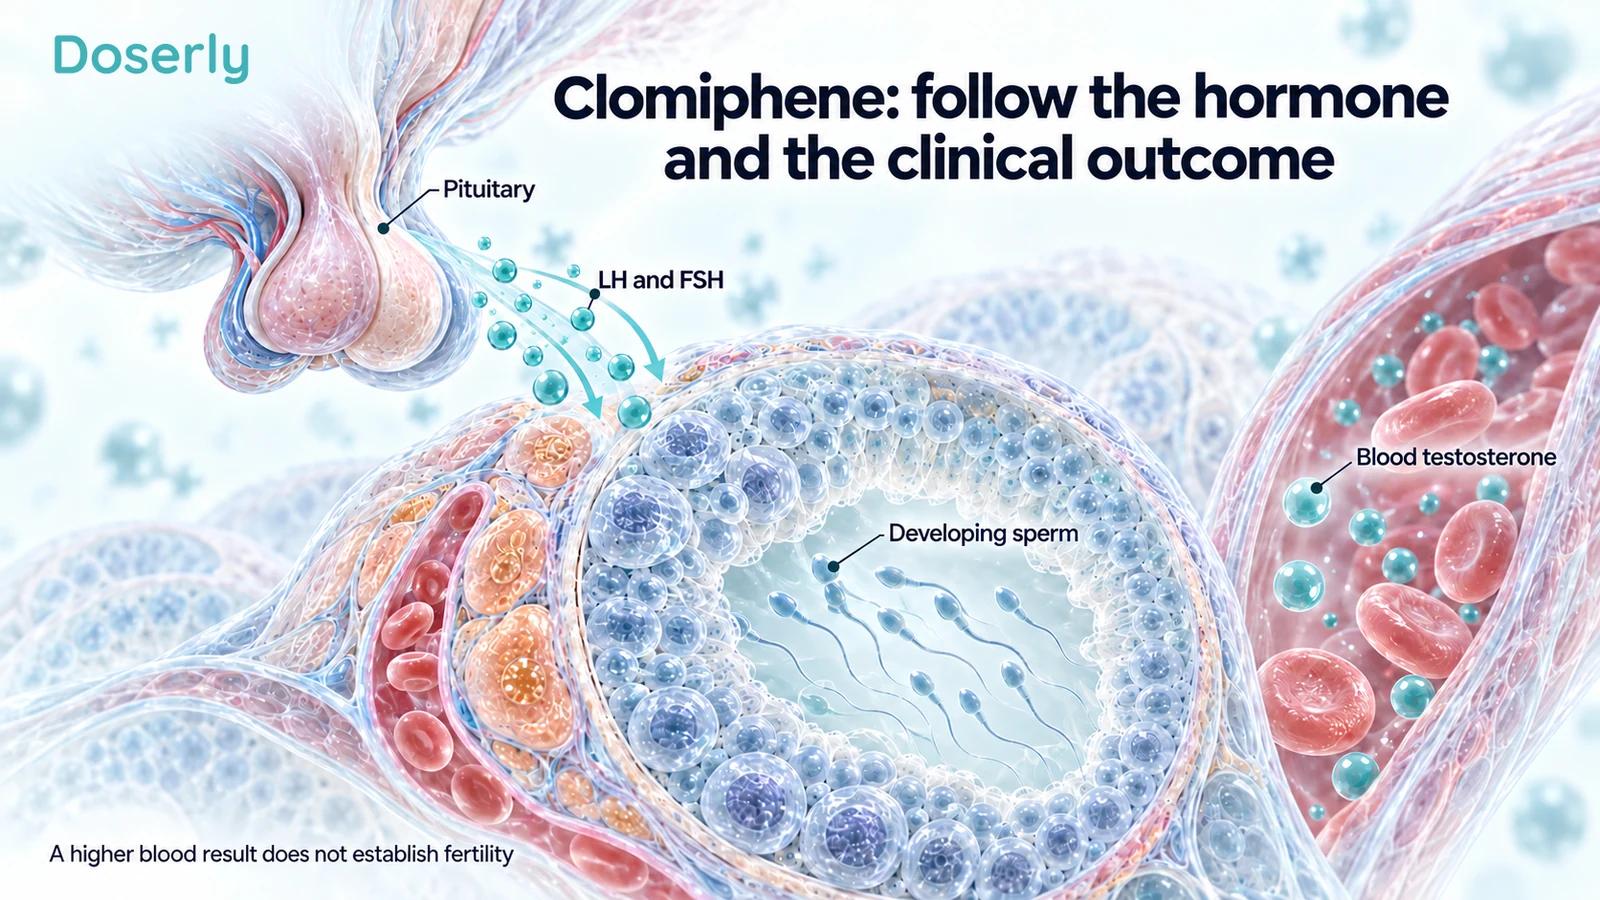
The illustration is conceptual: organ sizes, distances and hormone particles are not to scale. Its purpose is to show why an intervention upstream of the testes depends on more than the testosterone concentration alone.
The primary versus secondary hypogonadism guide explains this distinction. A confirmed diagnosis also requires compatible symptoms and consistently low testosterone assessed appropriately, rather than one isolated result. Endocrine Society guideline
What the symptom studies actually found
A prospective case series followed 86 hypogonadal men who chose clomiphene after discussion with their clinicians. Their mean age was 29, and mean treatment duration was 19 months. Hormone measurements increased, and symptom responses on the ADAM questionnaire generally improved. More than half reported improvement in at least three symptoms. Katz and colleagues
This offers useful clinical experience beyond a short laboratory experiment. It is not, however, a randomized placebo comparison. The men selected the treatment, and changes in symptoms could reflect several influences alongside the medicine.
A randomized, double-blind trial in 78 men with obesity-associated secondary hypogonadism provides a different type of evidence. Over twelve weeks, clomiphene increased testosterone and other hormones, improved one reported sexual complaint—weak erections—and changed some body-composition measures. HDL cholesterol decreased, and there was no statistically significant difference in the endothelial-function measures studied. Soares and colleagues
The controlled study supports a hormone response in that population. It does not establish broad improvement in every symptom, prevention of cardiovascular events, or the same effect in men with a different cause of low testosterone. A favorable result in one outcome should not erase a less favorable or unchanged result in another.
How to read the longer-term cohort
A retrospective study included 400 men treated with clomiphene for hypogonadism. Of these, 120 had received treatment for more than three years. Within that longer-duration subgroup, 88% achieved eugonadal testosterone levels, 77% reported improved symptoms and 8% reported side effects. Krzastek and colleagues
The subgroup is important. Those percentages do not describe 400 men all followed beyond three years. They describe the 120 who reached that duration.
The results are encouraging for people who continue treatment, but a retrospective continuation cohort has built-in limits. People who find a treatment ineffective or difficult to tolerate may stop earlier. Medical records may also capture symptoms and adverse events less consistently than a trial designed to look for them.
Reported longer-term side effects included mood changes, blurred vision and breast tenderness. The absence of a significant adverse event in this series cannot rule out uncommon harms in a much larger population.
These observations support an informed discussion of continued treatment. They do not justify describing long-term use as proven risk-free or promising a particular individual's chance of improvement from the subgroup percentages.
Raising testosterone is not the same as treating infertility
Clomiphene may be considered when low testosterone and fertility concerns overlap. That is different from prescribing it empirically for unexplained poor semen quality in a man without the same hormonal pattern.
An older but important randomized trial enrolled 190 couples in which the male partner had idiopathic impairment of semen quality. Men received clomiphene or placebo for six months. At eight months, the estimated cumulative pregnancy rates were 8.1% with clomiphene and 11.7% with placebo; the study did not demonstrate efficacy for that population. Semen-quality changes did not differ significantly. WHO trial
Those were pregnancy estimates, not live-birth rates. The finding does not prove that no man with low testosterone can benefit reproductively from clomiphene. It does challenge a blanket claim that increasing gonadotropins reliably treats all male infertility.
For someone trying to conceive, the relevant plan includes semen analysis and the reproductive circumstances of the couple. A blood testosterone rise cannot replace that assessment. The TRT and fertility guide places medication choices within that wider discussion.
Define success before the follow-up result arrives
A treatment plan becomes easier to evaluate when the intended benefit is written down in advance. If low sexual desire is the main problem, discuss how it affects daily life and what meaningful improvement would look like. If fatigue is the concern, keep the evaluation open to other causes rather than assuming testosterone explains everything.
At follow-up, assess the original problem alongside laboratory response. A person can have a substantial biochemical change without enough symptom improvement to make the treatment worthwhile. Conversely, a person who feels better still needs appropriate safety review.
This is also why a higher number should not automatically trigger enthusiasm for a higher dose. The purpose is to treat an identified problem, not to maximize a laboratory result. A clinician can help decide whether an apparent response is clinically useful and whether the balance remains favorable.
Practical details matter: exact formulation, start date, changes, adherence and the timing of testing. These make comparisons interpretable when the treatment is reviewed by another clinician.
Visual symptoms are a specific reason to act
The clomiphene label warns about visual disturbances, including blurring, spots and flashes. Some reported disturbances have lasted after stopping treatment, and some may be irreversible. The label directs patients with visual symptoms to discontinue treatment and obtain a prompt complete ophthalmological evaluation. CLOMID prescribing information
This should not be softened into “mention it at your next routine appointment.” If new visual symptoms occur while taking clomiphene, stop taking it and contact the prescriber promptly for eye assessment. Avoid driving if vision is affected.
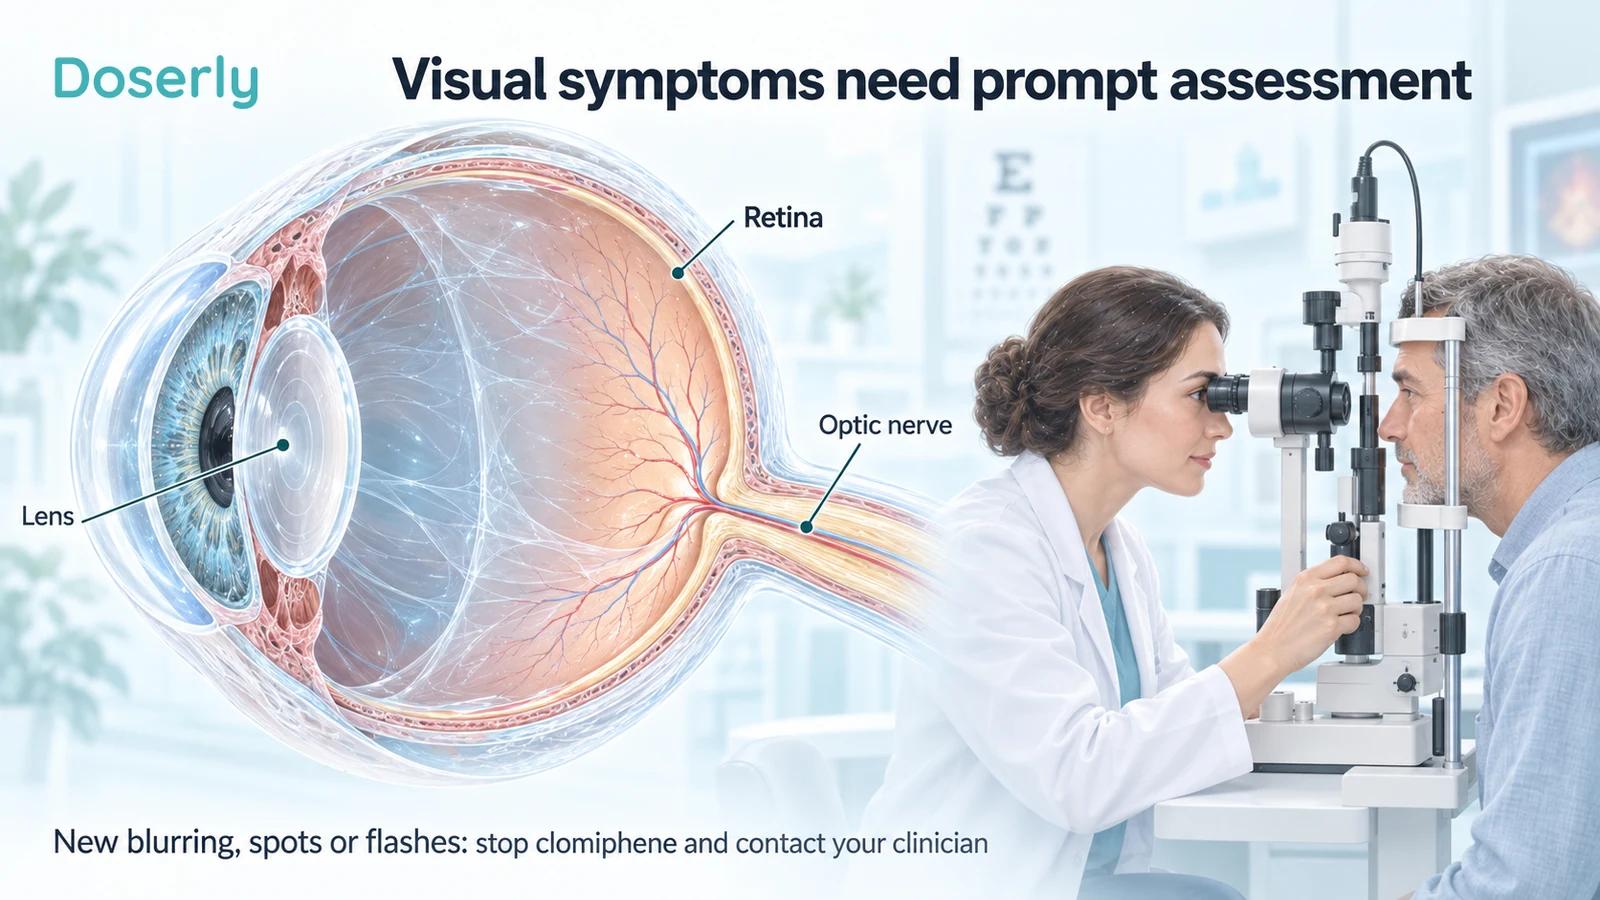
The label's adverse-event percentages largely come from its approved-use setting. They should not be copied as precise risk estimates for men taking prolonged off-label treatment. The action recommended for visual symptoms is clearer than the exact frequency in a particular male population.
The medical history is part of safety screening
The label lists liver disease or a history of liver dysfunction among contraindications. It also identifies uncontrolled thyroid or adrenal dysfunction and organic intracranial lesions such as a pituitary tumor. These are reasons for careful clinical assessment, not conditions to work around by choosing a smaller dose independently. CLOMID prescribing information
Bring relevant past diagnoses and previous abnormal results to the prescribing discussion. A clinic considering off-label treatment still needs to understand why a hormone result is low and whether another condition requires its own care. The medication's oral form does not make that evaluation optional.
Other changes still deserve review
The longer-term male cohort reported mood changes and breast tenderness, and estradiol increased during treatment. The obesity-associated hypogonadism trial also found an estradiol rise. Those observations make it inappropriate to describe clomiphene as simply “lowering estrogen.” Krzastek and colleagues, Soares and colleagues
It modifies receptor-mediated feedback; the measured hormone concentrations can change in several directions. A laboratory result and a symptom need to be interpreted together.
Tell the clinician about new breast symptoms, mood changes or other effects that began after starting or changing treatment. Do not assume every symptom is caused by the medication, but do not dismiss a consistent timing pattern either.
Adding an aromatase inhibitor or another hormone-active drug on your own creates a new intervention with its own effects and uncertainty. A treatment stack is not automatically supported by evidence for any one component.
Clomiphene and enclomiphene should not be swapped conceptually
Clomiphene contains both enclomiphene and zuclomiphene isomers. Enclomiphene alone has been studied as a separate intervention. The distinction is chemical and clinical, not just a different brand name. CLOMID prescribing information
When someone cites a study, check which medicine it used. The 400-person long-term cohort discussed here studied clomiphene. It cannot establish the long-term safety of every enclomiphene preparation, and a short enclomiphene trial cannot replace evidence about prolonged clomiphene use.
Doserly's clomiphene guide and enclomiphene guide keep those evidence bases separate. Confirming the actual product also helps avoid confusing a medication change with a dose change during follow-up.
Make continuation an active decision
An oral treatment can become routine quickly. Refills may continue while the original goal becomes less clear. Build in a point to revisit whether the treatment still serves that goal.
For symptom treatment, review the symptom that mattered at the start. For fertility, review semen testing and the timeline for conception. For either purpose, discuss adverse effects, monitoring and what would lead to a change of plan.
Useful questions include:
- Why is clomiphene appropriate for my underlying diagnosis?
- Which benefit is supported by evidence in people like me?
- What should we do if testosterone rises but the original problem does not improve?
- Who should I contact for visual symptoms or other new effects?
Clomiphene can be a reasonable subject for specialist discussion in selected men. Its value is best judged through a combination of diagnosis, patient-important benefit and safety—not through a testosterone result alone.
Sources
- CLOMID prescribing information
- AUA/ASRM Diagnosis and Treatment of Infertility in Men, amended 2024
- Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline
- Katz et al. Clomiphene outcomes in young hypogonadal men
- Krzastek et al. Long-term clomiphene safety and efficacy
- Soares et al. Clomiphene in obesity-associated hypogonadism
- WHO double-blind clomiphene trial in idiopathic male infertility