
TRT
October 16, 2026
Alex Tatem’s TRT Treatment Spectrum: The Evidence Behind Choosing a Route
On this page
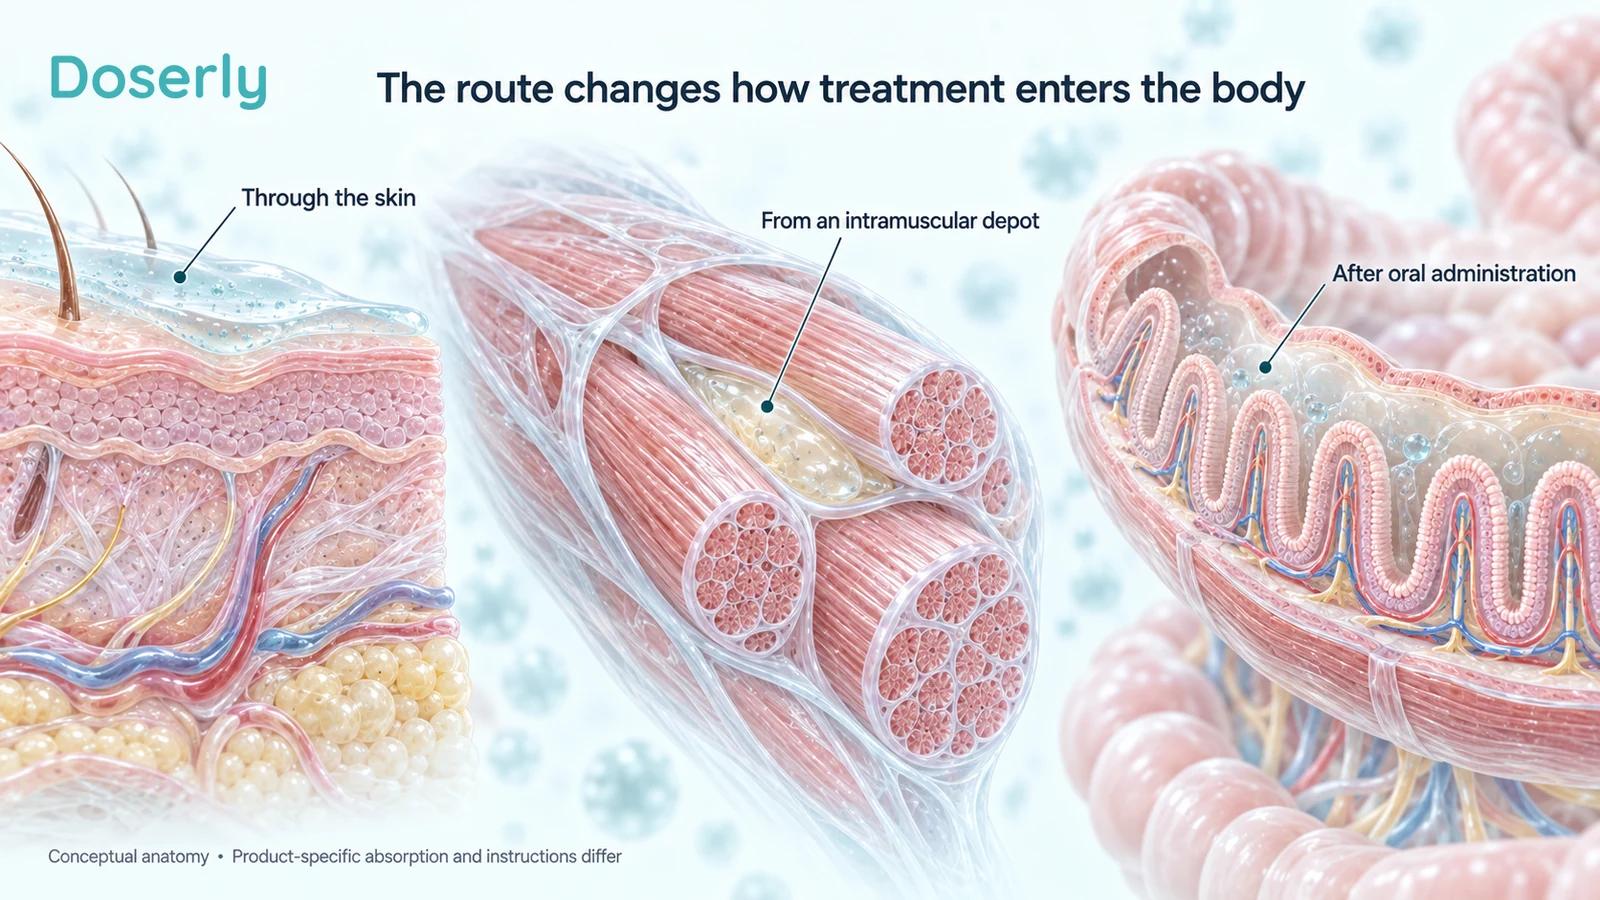
Choosing testosterone replacement therapy (TRT) is not finished when someone chooses “testosterone.” A gel, an injection, an oral capsule and an implanted pellet can create very different routines, precautions and follow-up requirements.
In a Urology Times discussion with Amy Pearlman, Alex Tatem explored that practical treatment spectrum. The publisher's summary and chapter list cover injection techniques, topical formulations, other delivery methods, pellets and patient preferences. This article uses that published material as the starting point, without claiming to quote a verified full transcript. Interview summary
The useful extension is to ask what evidence supports a route choice. A treatment may fit someone's schedule particularly well without being universally more effective or safer. The right comparison includes the diagnosis, desired benefit, product-specific instructions, monitoring and practical burden.
The diagnosis comes before the delivery preference
A preference for avoiding needles does not establish a need for TRT, just as a preference for injections does not establish the right hormone exposure. The Endocrine Society recommends confirming relevant symptoms or signs together with consistently low testosterone and investigating the cause.
For men who are appropriate candidates, the guideline supports choosing treatment with attention to patient preference, pharmacokinetics, formulation-specific adverse effects, treatment burden and cost. It recommends monitoring symptoms, adverse effects, testosterone and hematocrit, with additional assessment where indicated. Endocrine Society guideline
That makes route selection a shared clinical decision with several dimensions. “Which option will I actually use correctly?” is a legitimate question. So is “How will we know whether it is helping?”
Neither is answered by naming the most convenient product in an interview.
Gel exchanges injections for a daily skin routine
Topical testosterone can appeal to someone who wants to avoid injections. Its practical demands involve application, drying, washing and contact with other people.
For example, AndroGel 1.62% is applied to the upper arms and shoulders according to its instructions. The label calls for washing hands after application, covering the site after the gel dries, and washing the application site before anticipated skin-to-skin contact. It warns about secondary exposure, particularly involving children and women. Its application sites and dosing are not interchangeable with those of other topical products. AndroGel 1.62% label
For a patient, the question is whether that routine fits ordinary life: showering, exercise, intimacy, caregiving and clothing. These are not trivial inconveniences when a treatment is used repeatedly.
A route can be convenient in one household and awkward in another. Our testosterone-gel guide explains the distinctions among topical products and their instructions.
Contact precautions deserve their own place in the decision
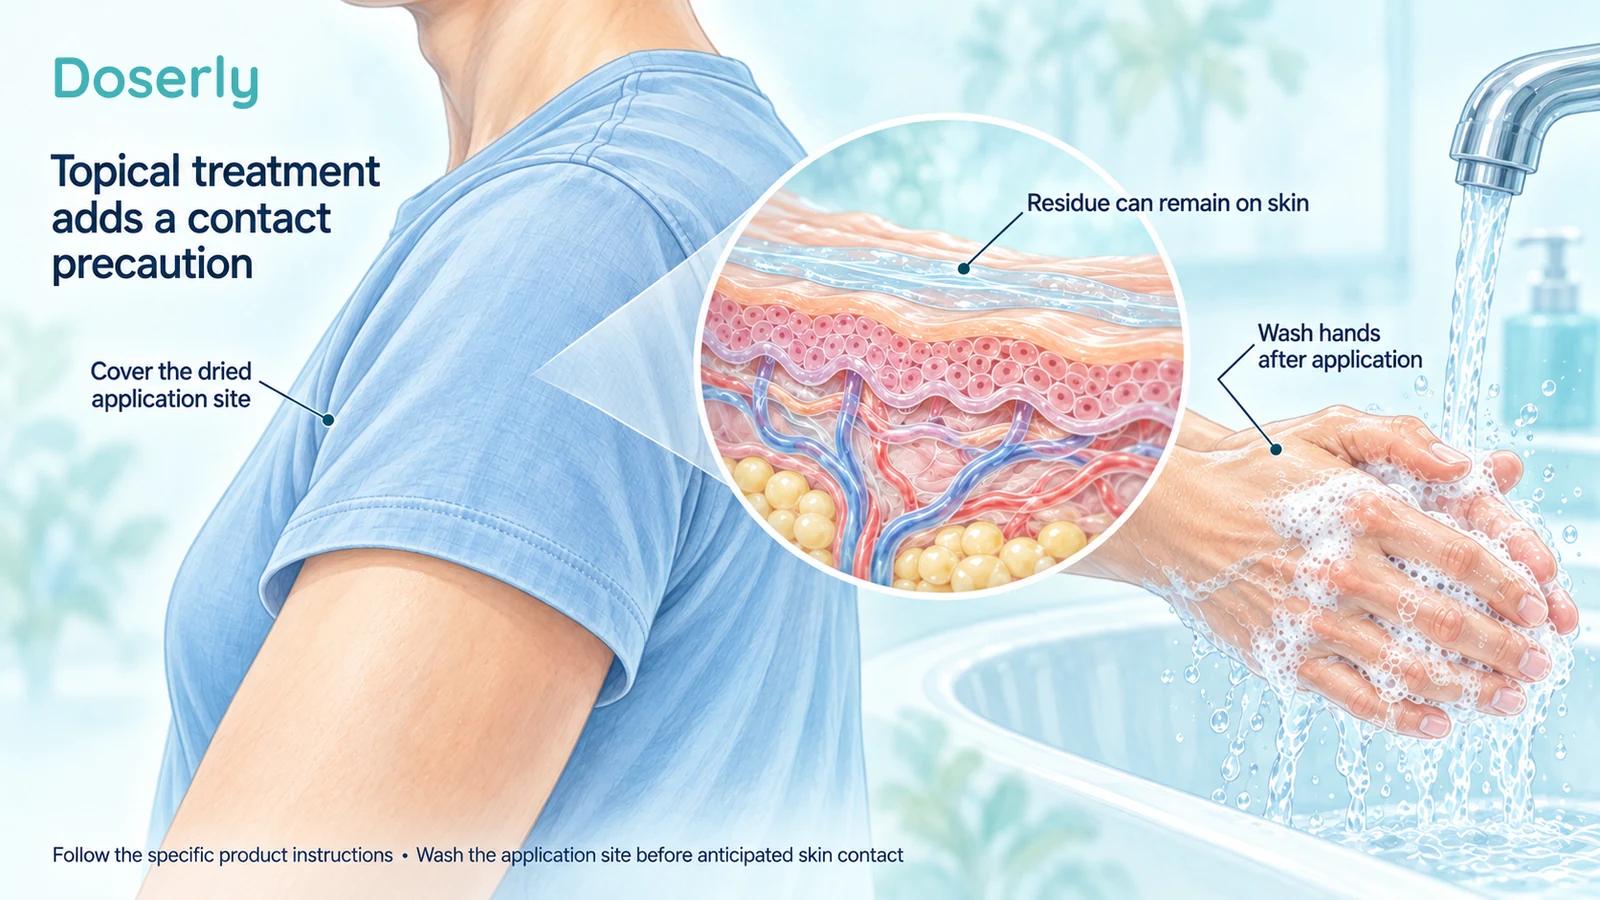
Someone comparing gel with injections may focus on avoiding needles and overlook secondary exposure. The practical comparison should include both.
It is useful to explain the application routine back to the clinician or pharmacist: where the product goes, when it can be covered, what contact precautions apply and which washing instructions matter. If the instructions do not fit the household routine, that is relevant information for choosing treatment.
Do not borrow a friend’s gel instructions or assume that the same number of pumps represents the same amount across products. Product identity matters even when the active hormone has the same name.
The aim is not to make topical therapy sound uniquely burdensome. Every route has demands; this is one that belongs explicitly in the topical discussion.
“Injection” is a category, not one regimen
Injectable testosterone includes different esters, preparations, devices and routes. Testosterone cypionate in oil is absorbed slowly from an intramuscular depot; that delivery process is part of why its exposure differs from a daily topical product. Cypionate prescribing information
A subcutaneous autoinjector is a different product example. Xyosted is labeled for subcutaneous administration in the abdominal region, with instructions to avoid intramuscular or intravascular administration. It also has its own training and blood-test timing requirements. Xyosted label
Those distinctions prevent a common shortcut: treating every injectable as if the same technique, route or schedule applies. A clinician may use some products differently from their label, but that is a specific clinical decision requiring instruction, not a rule to infer from the word “testosterone.”
Practical questions include comfort with administration, access to training, supplies, sharps disposal and the ability to maintain the prescribed schedule. These considerations can matter more to daily adherence than a theoretical preference for one ester.
A long-acting injection changes the appointment burden
A longer interval can reduce the frequency of administration, but the visit itself may involve additional requirements.
In the United States, Aveed, an intramuscular testosterone-undecanoate product, carries warnings for serious pulmonary oil microembolism reactions and anaphylaxis. Its prescribing information requires observation in a healthcare setting for 30 minutes after each injection and specifies a restricted safety program. Aveed label
That is a concrete example of why “fewer injections” does not fully describe convenience. Travel, appointment access and observation time all belong in the comparison.
These requirements are product-specific. They should not be transferred to every injectable testosterone product or ignored because another injection can be administered at home. Likewise, an oral capsule containing the same undecanoate ester is not administered or monitored like the injectable preparation.
Oral capsules have their own food and testing instructions
Modern oral testosterone-undecanoate products offer another route, but “oral testosterone” is not a single interchangeable medicine.
The Kyzatrex prescribing information issued in August 2026 instructs patients to take it with food and states that it is not substitutable with other oral testosterone-undecanoate products. It specifies its own timing for measuring testosterone after the morning dose and retains a blood-pressure warning. Kyzatrex label
For someone considering capsules, the practical question includes whether the prescribed routine and food instructions fit consistently. Avoid assuming that the milligram amount can be converted directly from an injection or that instructions for another oral product apply.
The oral-testosterone guide provides background on those formulation differences. A capsule can reduce one kind of burden while introducing another; that is a reason to compare routines carefully rather than rank routes by appearance.
Pellets trade frequent administration for a procedure
Testosterone pellets can reduce the need for repeated self-administration, but placement is a procedure and adjustment is less flexible.
The Testopel label describes implantation-site infection and pellet extrusion as possible complications. It also states that pellet dosing is less flexible to adjust than oral treatment or intramuscular oil preparations, and that removal may be necessary if the effects need to be discontinued. Testopel label
This changes what “easy” means. Someone who struggles with daily administration may value a longer-lasting approach. Someone still evaluating tolerability or seeking greater adjustment flexibility may place more weight on the difficulty of reversing an implanted treatment.
The relevant conversation includes procedure access, aftercare, follow-up and what would happen if an adverse effect or a change in goals required reassessment. Convenience should include the exit plan as well as the start.
All routes still need outcome and safety monitoring
A delivery preference does not remove the need to assess whether the treatment is appropriate or effective. Nor does it eliminate risks that are not unique to the route.
FDA's 2025 communication required blood-pressure information across testosterone products after reviewing ambulatory-monitoring studies. That is a reason to discuss actual product data and individual monitoring, not to assume that avoiding injections removes the issue. FDA labeling communication
Fertility goals also belong before route selection. Exogenous testosterone can suppress sperm production; the Endocrine Society recommends against starting testosterone in men planning fertility in the near term. Choosing a capsule or gel does not bypass that concern. Endocrine Society guideline
The practical benefit you want should remain visible throughout follow-up. A more convenient route is useful only in the context of an appropriate treatment goal and acceptable monitoring results.
Evidence for one product is not a route championship
TRAVERSE used testosterone gel in selected men aged 45 to 80 with hypogonadism and cardiovascular disease or elevated cardiovascular risk. It was a placebo-controlled cardiovascular-safety trial, not a randomized competition among gels, injections, capsules and pellets. TRAVERSE
Its findings therefore cannot directly establish that gel is the best route for every patient. Equally, a smaller study showing that another product brings testosterone into a target range does not prove superior symptom relief or long-term safety.
When comparing options, distinguish three questions: can the product deliver hormone exposure, does it improve a patient-relevant outcome, and what adverse effects or practical burdens accompany it? Different studies may answer different parts.
An interview can help explain how an experienced clinician weighs those pieces. It does not make the evidence identical across all choices.
Plan the blood test when planning the prescription
A result taken at the wrong point in relation to treatment can be difficult to interpret. Product labels and clinical guidance specify different approaches to testosterone measurement depending on formulation.
That makes test timing part of route selection, especially for someone whose work, travel or access to laboratory appointments makes a particular schedule difficult. Ask when the blood draw should occur relative to the most recent administration and whether the product should be used as usual that day.
Do not transfer instructions from the previous product after a switch. The blood-work guide explains why timing and formulation need to be recorded together.
A useful record contains the exact product, prescribed administration dates and the blood-draw date and time. Those details help a clinician interpret the result without guessing about exposure.
Compare the real week, not the ideal week
Imagine two hypothetical patients with similar clinical eligibility. One has a predictable morning routine and finds topical precautions manageable. The other works rotating shifts and regularly helps with hands-on childcare. Their practical preferences may differ even before considering laboratory response.
Now imagine a patient who travels frequently and prefers fewer administrations but lives far from a clinic offering the proposed long-acting product. The interval alone does not settle the burden.
These are examples of decision-making, not recommendations for those groups. The point is to test the proposed routine against actual circumstances: missed appointments, refills, travel, contact precautions, supplies and cost.
A plan that depends on an unrealistic routine may need revision before treatment begins. Discussing that openly is more useful than treating adherence difficulties as a personal failure afterward.
Leave with a specific plan for reassessment
Before choosing a route, clarify the intended benefit, the product's practical instructions, how monitoring will be arranged and what would justify reconsidering the choice. Ask what to do if an administration is missed or a refill is delayed; the answer should come from the relevant clinician or pharmacist.
If a switch is made, record the dates and instructions rather than trying to convert amounts between products yourself. Doserly can help organize the prescribed routine and follow-up observations, but it does not establish equivalent dosing or decide which route is best.
Tatem and Pearlman's discussion is useful because it brings practical treatment choices into view. The evidence adds the necessary detail: route selection works best when preference, product-specific requirements and a clearly defined clinical goal are considered together.
Sources
- Urology Times interview summary
- Endocrine Society guideline
- AndroGel 1.62% prescribing information
- Testosterone cypionate prescribing information
- Xyosted prescribing information
- Kyzatrex prescribing information
- Aveed prescribing information
- Testopel prescribing information
- FDA 2025 labeling communication
- TRAVERSE cardiovascular-safety trial