
Peptides
October 16, 2026
Why an LR3 certificate cannot establish human safety
On this page
IGF-1 LR3 is a modified form of insulin-like growth factor 1, a signal involved in cell growth and metabolism. People interested in it for muscle or recovery often encounter a certificate showing a high purity percentage. That document may contain useful laboratory information. It cannot, by itself, answer the more personal question: what would happen if this substance were administered to a person?
The distinction matters even when the laboratory and its results are genuine. A sample can contain the expected molecule and still have an unestablished balance of benefits and harms. Product quality and clinical safety are connected, but they require different evidence. A chemical test examines material; a clinical study follows people receiving a defined treatment.
This article explains what the common certificate entries mean, where their limits lie, and why neither a purity number nor a familiar growth-factor name supplies the missing human research. Our IGF-1 LR3 guide provides broader background on the molecule and the distinction from prescription mecasermin.
Start with the identity of the substance
The letters after IGF-1 are consequential. Long R3 IGF-I, commonly written IGF-1 LR3, has an added amino-acid segment and a substitution within the IGF-I sequence. These modifications affect its interactions with IGF-binding proteins, which influence the availability of growth-factor signals. The original recombinant analogue work studied activity in cell systems; it did not establish a clinical regimen for people. Francis and colleagues, 1992
This is why a document headed simply “IGF-1” needs clarification. Native IGF-1, LR3, and other analogues are not interchangeable names for one finished medicine. A laboratory method should be capable of distinguishing the material it claims to identify from relevant alternatives.
A 2021 anti-doping methods paper illustrates the point. Researchers developed a method combining antibody-based purification and high-resolution mass spectrometry to detect several IGF-I analogues. Its administration experiments involved rats. The work supports analytical identification and detection research; it does not establish human therapeutic safety. Mongongu and colleagues
Knowing that a molecule can be detected is useful. It is different from knowing its appropriate exposure, how a human body clears it, or which people are particularly vulnerable to unwanted effects.
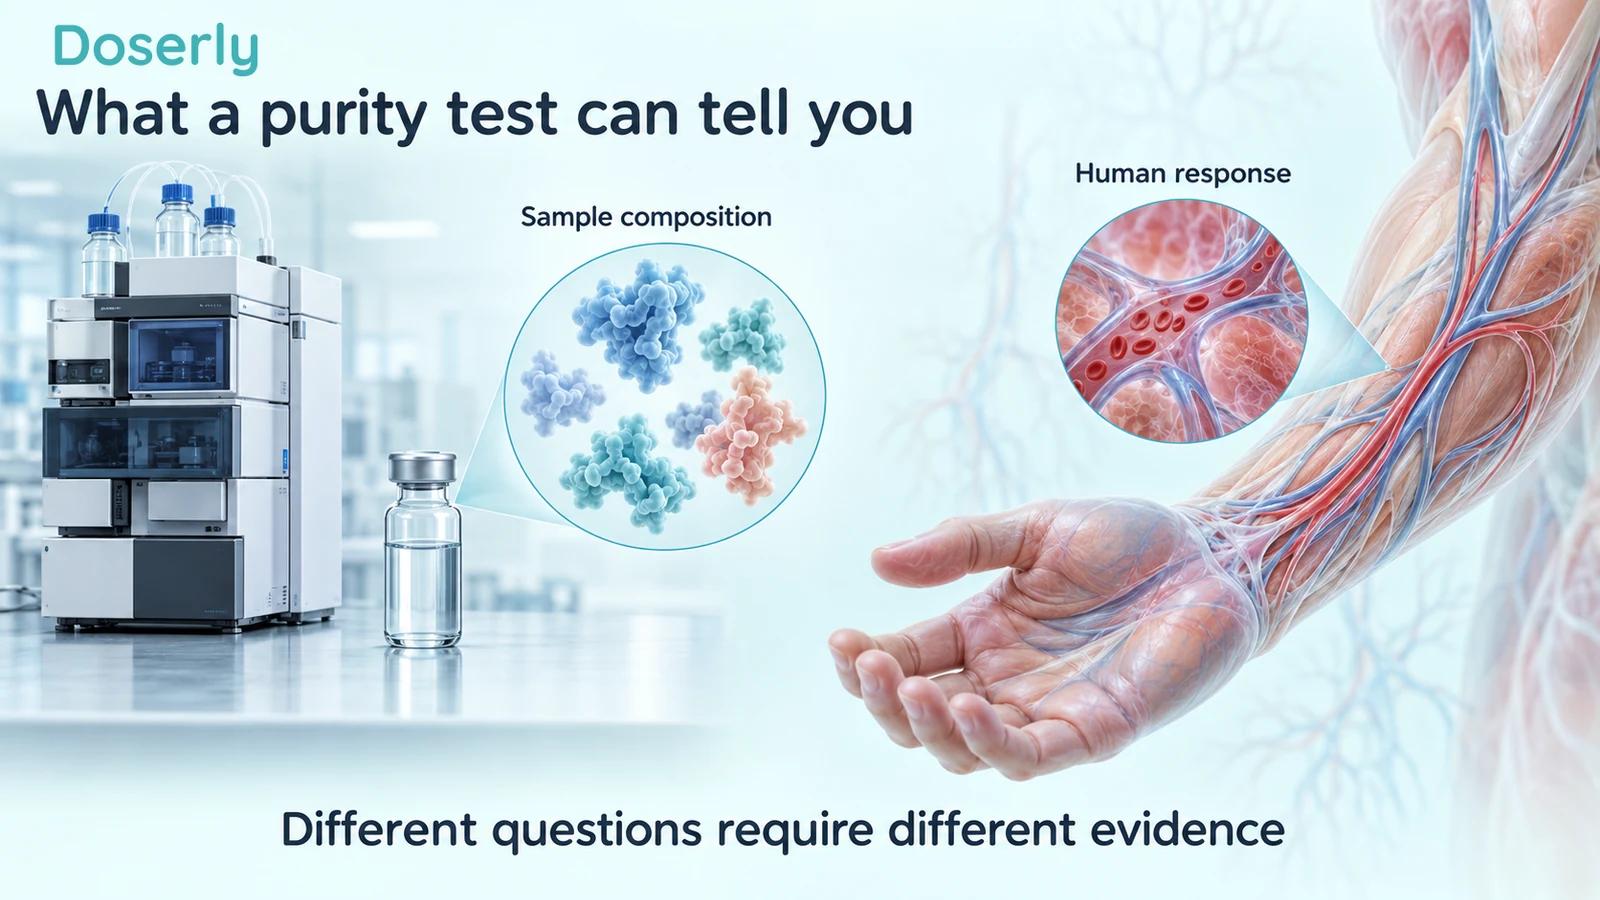
What a purity percentage actually describes
A purity figure is the result of a particular measurement and calculation. It should come with a method, a specification, and an identifiable sample. Without those details, “99% pure” has no clear denominator: 99% of what was measured, by which technique, under which conditions?
High-performance liquid chromatography, usually shortened to HPLC, separates material as it passes through a laboratory system. A detector records signals associated with material leaving the column. A reported percentage may describe the area of one peak relative to other detected peaks. That is not automatically the percentage of every substance in the vial by weight, and it does not measure every possible contaminant.
GroPep's media-grade LR3 specification makes the method dependence particularly visible. It lists purity of at least 95% by gel electrophoresis, while separately describing three HPLC peaks with the main peak exceeding 50% of total area. These are different analytical descriptions of a research product, not competing claims about the probability of harm. GroPep media-grade specification
The practical lesson is to read the method rather than treating the biggest number as a universal score. A measurement can be correct and still be irrelevant to a particular question. A report describing peptide-related material cannot be silently expanded into a finding about microbial contamination, the amount in each vial, or a person's response.
Nor does a percentage identify the remainder. A small impurity fraction could represent different materials in different samples. Assessing its significance would require characterization and an appropriate toxicological context, not arithmetic alone. “Less impurity” is a reasonable manufacturing objective; “therefore safe for me” is a much larger conclusion.
Identity, quantity, and biological activity are separate
An identity test asks whether the expected substance is present. A content or quantity test asks how much is present. A biological assay asks whether material produces a specified response in a test system. A report may include one, two, or all three, but they should not be collapsed into a single idea of quality.
Consider a hypothetical vial whose peptide identity is confirmed. That finding does not tell you whether the labelled amount is accurate. Conversely, a vial could contain the stated total mass while some of that mass is not the intended active substance. These examples explain the questions a report must answer; they are not allegations about a particular supplier.
Biological activity is also defined by the assay. GroPep's receptor-grade specification describes a protein-synthesis assay in L6 myoblasts, a laboratory muscle-cell model, and identifies the material as a research reagent. It explicitly excludes human use. A response in those cells establishes activity under those experimental conditions, not improved strength or recovery in someone using the product. GroPep receptor-grade specification
This distinction is especially relevant to growth factors. A substance being biologically active is the reason to investigate both benefit and harm. Activity is not inherently reassuring. If a compound affects a signaling system, researchers need to determine which tissues respond, how strongly, and for how long.
Why sterility and endotoxin need their own evidence
Sterility concerns viable microorganisms. Endotoxins are bacterial components that can provoke harmful inflammatory responses; an endotoxin test addresses a different target from a test for living organisms. A chemical purity result answers neither question.
FDA's guidance treats endotoxin testing as a method that must be appropriate for the product and its testing conditions. Sample interference, suitable limits, and validated methods matter. A report needs enough context to interpret the result; the word “tested” alone is not a complete finding. FDA, Pyrogen and Endotoxins Testing, Edition 2
These distinctions explain why a vial's appearance is inadequate reassurance. Clarity, colour, or the absence of visible particles cannot replace laboratory and manufacturing controls. A consumer cannot establish sterility by looking at a sealed container.
There is a concrete historical LR3 example, although it needs careful wording. FDA's amended October 2018 inspection record for Tailor Made Compounding listed an IGF-1 LR3 batch among documented sterility failures. The document specifically says the listed products were not dispensed to patients. It also records concerns about the scope of investigations into other potentially associated batches. The form contains inspectional observations, not a final agency compliance determination. FDA amended inspection record, page 1
That record does not establish a contamination rate for the present marketplace or say anything about an unrelated vial. Its relevance is narrower: chemical identity and manufacturing sterility are different questions, and actual quality systems have to address both.

A result belongs to a sample and a point in time
A certificate's usefulness depends on its connection to the material being discussed. A batch identifier, sampling date, laboratory identity, and description of the submitted sample help establish that connection. A report for bulk starting material is not automatically a report for a final filled container.
This is a matter of traceability: being able to follow what was tested and how it relates to what is supplied. Imagine a valid report that describes material before a later filling operation. The result can remain valid for that sample while leaving later handling unaddressed. Equally, a report from a previous batch cannot be assumed to describe every subsequent batch.
Manufacturing controls therefore matter alongside end-product tests. FDA's discussion of sterile drug production explains why sterility assurance depends on the production process and appropriate controls, rather than a single final test being sufficient on its own. FDA manufacturing questions and answers
For a reader, the useful question is not simply whether a certificate exists. It is what conclusion the actual document supports. If it reports only chemical purity, describe it as chemical purity evidence. If the sample-to-product connection is unclear, that uncertainty should remain visible rather than being filled by confidence in the presentation.
Even excellent quality would leave clinical questions open
Suppose identity, content, relevant impurities, and manufacturing controls were all well characterized. Researchers would still need to study the compound's behavior in people. The remaining questions concern the substance itself, not merely the possibility of poor production.
Pharmacokinetics describes how exposure changes as a substance is absorbed, distributed, and cleared. Pharmacodynamics describes what it does to the body. Neither can be read from a chromatogram. A purity result does not show how long an effect persists, whether repeated exposure accumulates, or how other medicines change the response.
Preclinical LR3 findings give reasons to avoid assuming that its effects are confined to skeletal muscle. In a seven-day infusion experiment in female guinea pigs, LR3 increased the relative weights of several organs without significantly stimulating overall body growth. That is an animal result under a specific exposure, not a prediction of what would happen to an individual person. It does show why “growth-related activity” and “desired muscle benefit” are different claims. Conlon and colleagues, 1995
The right response is neither to assign a human risk percentage from that experiment nor to dismiss the finding because it is preclinical. It identifies questions human development would need to investigate. A certificate cannot resolve them because no people were followed to produce it.
Mecasermin's label cannot fill the LR3 gap
INCRELEX contains mecasermin, recombinant human IGF-1. Its prescribing information describes a defined pediatric treatment context and warnings including severe hypoglycemia, hypersensitivity, intracranial hypertension, and malignancy-related concerns. Those warnings belong to that medicine and its evidence base. Current INCRELEX prescribing information
The label is useful for understanding why IGF biology deserves medical attention. It does not provide an LR3 adverse-event rate, approve an LR3 product, or validate applying the same treatment schedule to a modified analogue. Shared biological relationships do not erase differences in molecule, formulation, exposure, and patient population.
This is also why a claim such as “it is just like the body's own growth factor” is incomplete. The modifications that make LR3 interesting in laboratory research are precisely the reason its behavior requires independent characterization. Familiarity with the name IGF-1 should prompt more precise questions, not substitute for answers.
How to use a certificate in a health conversation
Bring the entire document, together with the product label and the reason you are considering the compound. That allows a clinician or pharmacist to distinguish an analytical claim from a medical claim. A cropped purity number strips away much of the information needed to interpret it.
Three questions make the discussion more concrete:
- What was actually measured? Ask about identity, quantity, impurity characterization, microbial testing, and whether the results concern starting material or the finished product.
- What human evidence supports the proposed benefit? A cell assay, animal experiment, or detection paper cannot show that a person will recover faster or gain useful strength.
- What remains unknown about harms? A quality report does not quantify unwanted effects, identify vulnerable populations, or establish long-term safety.
These questions do not turn a collection of certificates into a clinical validation checklist. They help prevent a limited document from being asked to answer a much broader question.
If you are trying to address weakness, slow recovery, or a change in physical performance, describe those symptoms and goals directly. The useful decision is which evaluated approach fits the underlying problem. The Doserly IGF-1 LR3 guide can help you keep the molecule names and research types distinct while preparing for that conversation.
Sources
- Francis et al., 1992: recombinant IGF-I analogues — original laboratory work.
- Mongongu et al., 2021: analytical detection of IGF-I analogues — anti-doping method and rat administration work.
- GroPep receptor-grade specification — manufacturer research-reagent specifications.
- GroPep media-grade specification — method-specific quality measures.
- FDA endotoxin testing guidance — testing principles.
- FDA amended inspection record, 2018 — historical observations with explicit non-dispensing qualification.
- FDA sterile manufacturing guidance Q&A — production controls.
- Conlon et al., 1995 — guinea-pig infusion study.
- INCRELEX prescribing information — mecasermin context, not LR3 labeling.