
Peptides
October 16, 2026
What would useful IGF-1 LR3 clinical research need to measure?
On this page
IGF-1 LR3 attracts interest because it modifies a growth-factor signal involved in cell activity and metabolism. The practical questions are more demanding than whether it can stimulate cells: would it improve strength, preserve muscle during illness, or help someone recover useful movement, and at what cost in unwanted effects?
Useful clinical research would have to answer those questions in people receiving a precisely identified LR3 preparation. A higher laboratory signal would be one piece of information, not the whole result. The outcome should match the benefit being claimed. If the promise is stronger muscles, researchers need to measure strength; if it is recovery from injury, they need to measure recovery.
The primary sources reviewed for this article did not provide a controlled human LR3 treatment study establishing those benefits. A direct registry search also encountered an access failure, so this is not a claim that an exhaustive search proved no study exists anywhere. The Doserly IGF-1 LR3 guide explains the laboratory and animal background. Here, we'll examine what evidence would make the clinical discussion more informative.
Why a biologically active compound still needs clinical testing
LR3 is an analogue: a modified version of IGF-I. Its altered interaction with IGF-binding proteins helps explain its activity in laboratory systems. The original analogue research compared biological responses across cell models; those conditions do not reproduce the full regulation of growth signals in a person. Francis and colleagues
That creates two linked questions. First, does a defined exposure produce the intended biological effect? Second, does that effect translate into a worthwhile benefit without unacceptable harm? The first question helps explain a mechanism. The second determines whether the intervention helps.
A biomarker is a measurable biological characteristic, such as a blood concentration. Some biomarkers can serve as substitutes for clinical outcomes after adequate validation. Others are useful for understanding drug activity but cannot establish that someone feels or functions better. FDA's endpoint framework makes this distinction explicit. FDA surrogate endpoint resources
For LR3, receptor activity or a growth-related blood measurement would not automatically be a validated substitute for strength, mobility, or recovery. A promising mechanism gives researchers a reason to test a hypothesis. It does not determine what the eventual answer must be.
A human IGF-I study shows why this distinction matters
A small randomized study published in 2001 examined native IGF-I, not LR3, in healthy, nonobese postmenopausal women over 60. Sixteen women completed a one-year protocol comparing IGF-I with placebo. The treatment raised circulating IGF-I, but the investigators did not find improvements in measured lean mass, fat mass, bone density, strength, mood, or memory. Further recruitment was stopped after preliminary analyses suggested no changes in the outcomes being studied. Friedlander and colleagues
This small, discontinued study cannot prove that LR3 would fail, nor settle every use of native IGF-I. Its value here is more specific: raising a biologically interesting signal did not ensure that the desired patient outcomes improved.
The comparison also prevents a common shortcut. A paper with “IGF-I treatment” in its title is not necessarily an LR3 trial. The exact molecule, population, duration, and outcome need to remain attached to the finding. Otherwise, a mechanism paper can become a muscle-gain claim through a change in wording rather than new evidence.
Choose a clinical problem before choosing a measurement
A study in a frail older adult, a person with muscle wasting from disease, and a healthy resistance-trained athlete would address different problems. Their baseline function, opportunities for improvement, accompanying treatments, and acceptable risks may differ substantially.
For example, a proposed study of disease-related muscle loss could ask whether treatment helps preserve the ability to rise from a chair or walk independently. A study about rehabilitation after a defined injury could ask how long it takes to recover a specified level of strength and safely resume an activity. Those are proposed questions, not established LR3 uses.
Researchers would also need to define the background treatment. If participants receive physiotherapy, nutritional support, or treatment of an underlying disease, that care should be described and appropriately balanced between groups. Otherwise, an improvement could reflect a difference in rehabilitation rather than LR3.
Eligibility criteria should make the findings interpretable. “Adults interested in recovery” is too vague to establish what was treated. A clear diagnosis or functional deficit, together with baseline measurements, gives the eventual result a clinically meaningful context.
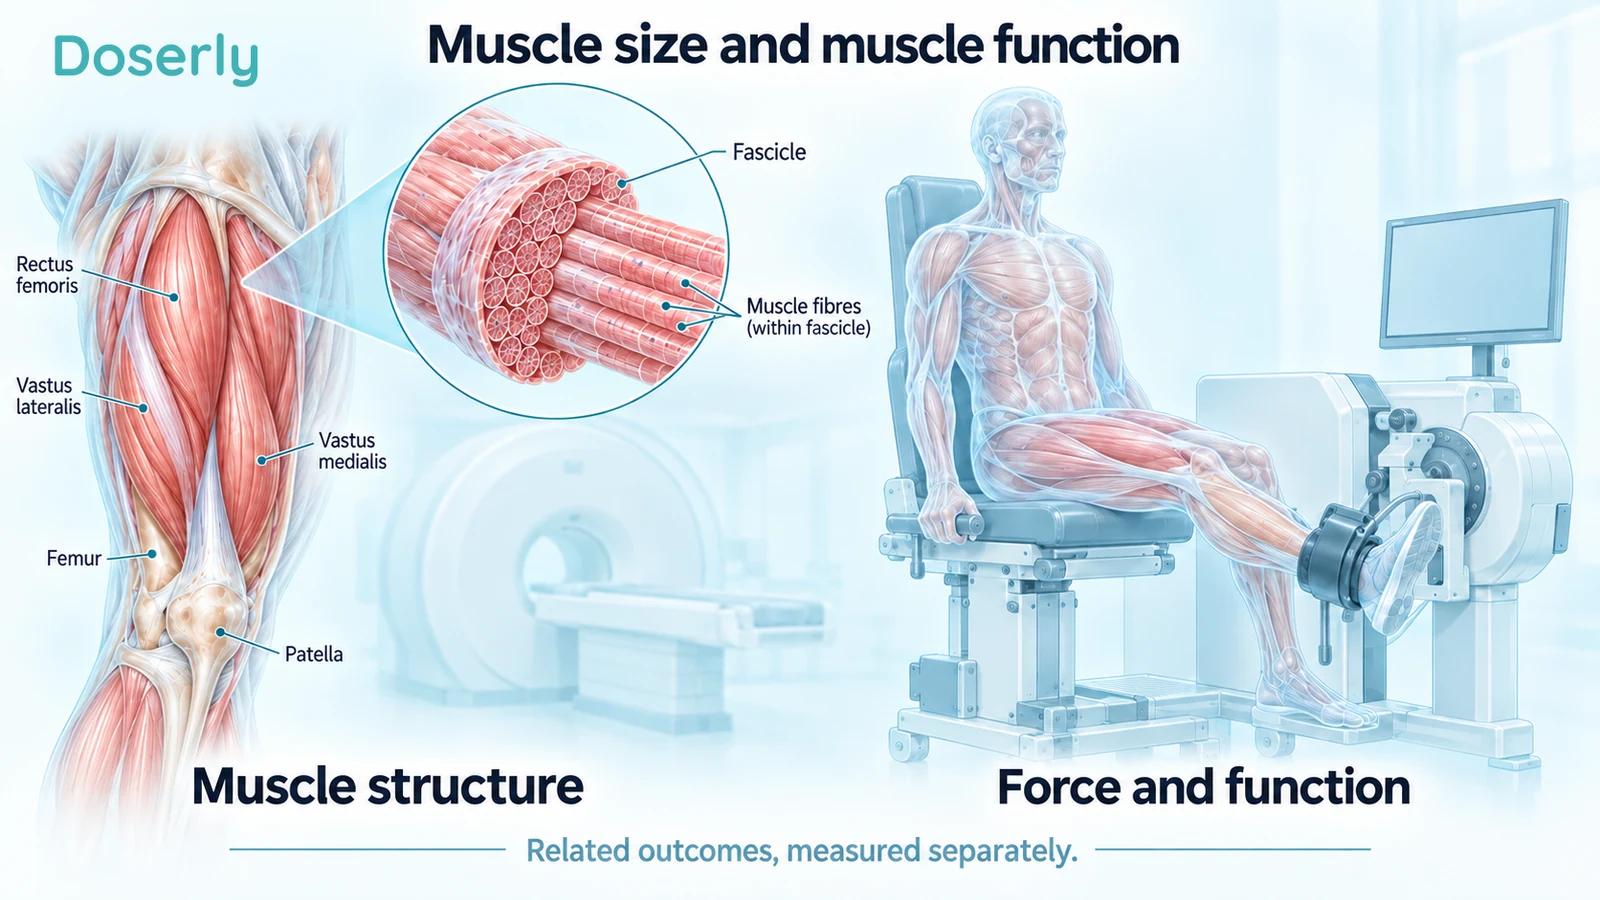
Measure structure, strength, and daily function separately
Muscle size can be useful, but it is not a complete description of muscle performance. Imaging can characterize tissue structure. Strength testing measures force. Walking, stair climbing, or repeated chair rises may reflect how someone performs tasks that matter outside the laboratory.
Which measure deserves priority depends on the intended benefit. A trial aimed at improving mobility should not declare success solely because an imaging result changed. Equally, if a small early study is explicitly designed to examine tissue biology, it should report that purpose without presenting itself as proof of improved everyday function.
The assessment must also work in the selected population. A demanding exercise test may be inappropriate for someone with substantial disability. An easy walking test may leave little room to detect change in a highly trained participant. FDA's clinical outcome assessment guidance emphasizes choosing measures that fit the intended concept and context. FDA fit-for-purpose assessment guidance
Repeated tests should use consistent procedures. Familiarity with equipment, encouragement, assessor expectations, and timing after exercise can influence performance. A carefully designed trial tries to separate those influences from the treatment effect.
Define what “better recovery” would mean
Recovery is often discussed as if it were a single number. In practice, less soreness, restored force, healed tissue, and return to normal activity can describe different aspects of it.
A useful injury study would specify the injury and establish when recovery begins. It would choose a meaningful outcome, such as regaining a defined functional capacity, rather than allowing the main outcome to change after the results are known. It would also record setbacks and further injury, because an earlier return to activity is not necessarily a benefit if it is followed by more problems.
Pain scores could be relevant, but they would need to be interpreted alongside activity and function. Someone may report less pain because they have reduced their activity. Someone else may regain strength while still experiencing discomfort. A combined account is more useful than assuming that one measure captures the entire process.
These distinctions are practical. They explain what a patient should expect a recovery claim to specify: recovery from what, measured how, compared with whom, and sustained for how long.
Establish exposure before interpreting a response
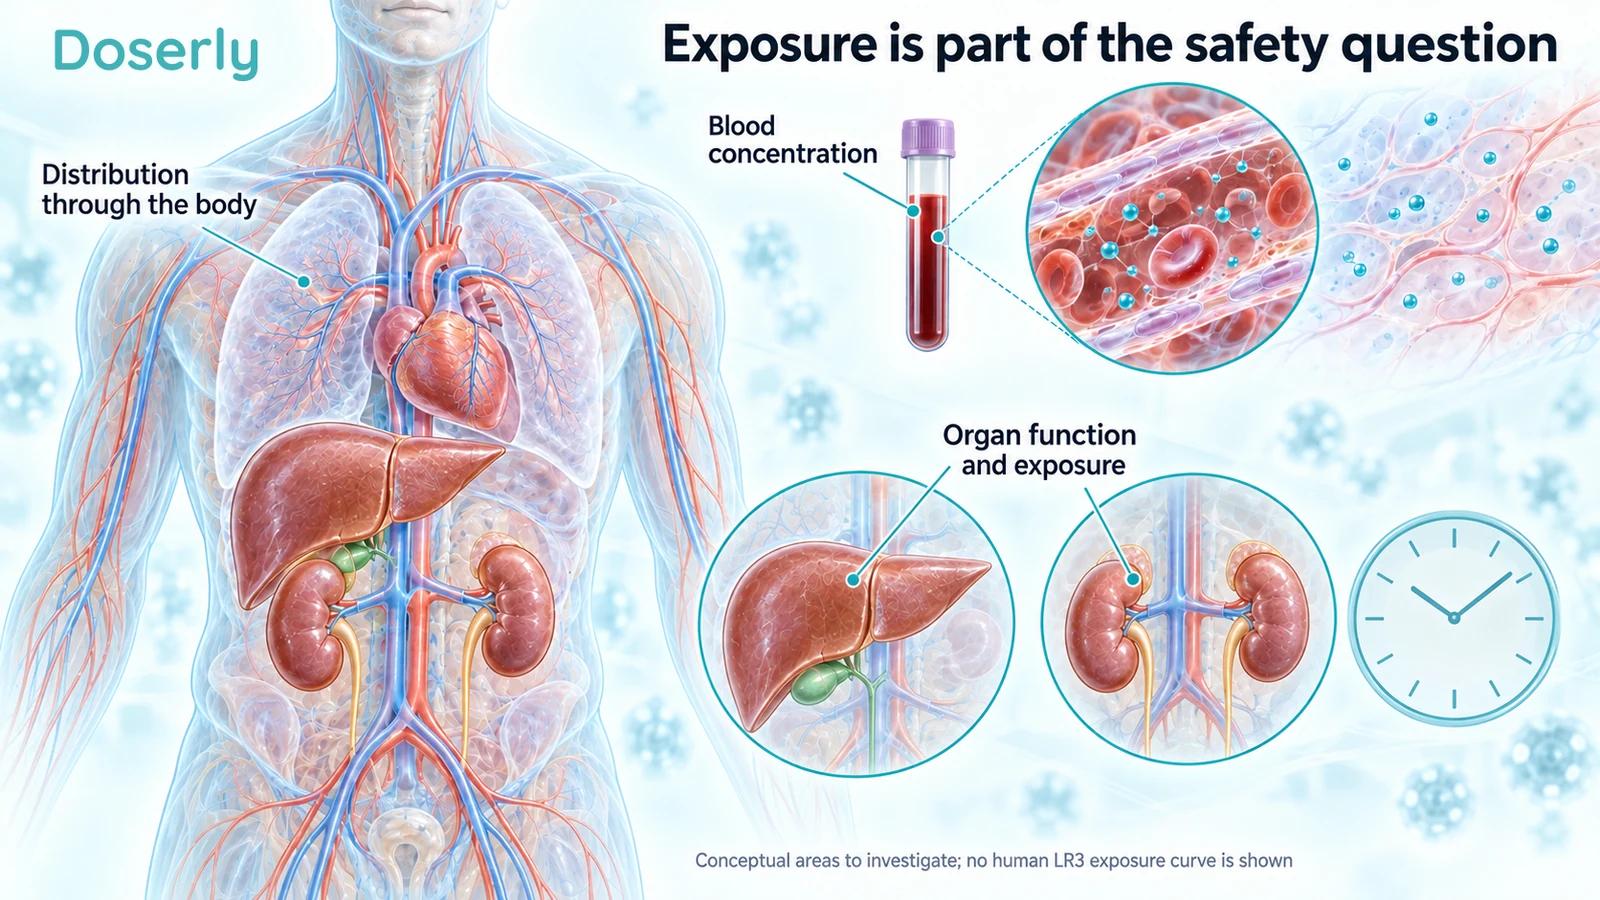
A clinical development programme would need validated ways to identify and measure LR3. Pharmacokinetics concerns the time course of exposure: absorption, distribution, and elimination. Without those data, a nominal amount does not tell researchers how much active material reaches relevant tissues or how long it remains available.
An LR3 assay would need to distinguish the analogue from related substances where appropriate. Existing anti-doping methods demonstrate that such analytical questions can be investigated, but a detection method and its rat administration experiments are not a human pharmacokinetic study. Mongongu and colleagues
Repeated exposure raises additional questions. Does the concentration pattern change over time? Do individual characteristics or other medicines alter it? Do biological effects persist after measurable concentrations decline? These are research questions requiring actual observations.
A standard IGF-I result should not be assumed to answer every one of them. Investigators would need to characterize what their chosen assay detects and how that measurement relates to the compound under study.
Safety needs planned observation, not just volunteered complaints
Safety assessment would begin before human exposure, with appropriate product characterization and preclinical development. Any human programme would then need formal oversight, informed consent, stopping rules, and systematic collection of unwanted events.
The IGF family gives reasons to pay attention beyond muscle. INCRELEX's prescribing information, for the separate medicine mecasermin, includes warnings about hypoglycemia and other clinically significant effects. That label can inform questions worth investigating; it cannot supply LR3 event rates or an LR3 monitoring protocol. INCRELEX prescribing information
Direct LR3 animal work also argues against assuming tissue selectivity. In a short guinea-pig infusion study, several relative organ weights increased without a significant overall growth effect. The result belongs to that species and experimental exposure. It is a reason to investigate systemic effects, not a quantitative prediction of human harm. Conlon and colleagues
Researchers should report how adverse events were sought, their severity, treatment discontinuations, and follow-up after stopping. “Well tolerated” is difficult to interpret without the numbers and observation period. A small early study may identify common immediate problems while remaining unable to exclude uncommon or delayed effects.
Use a comparison that answers the actual question
If all participants improve during rehabilitation, that does not reveal how much the experimental treatment contributed. An appropriate concurrent comparison helps account for natural recovery, background care, and expectations.
Random assignment can reduce systematic differences between groups. Blinding, where feasible, helps limit changes in behaviour and assessment caused by knowing who received the treatment. These design choices are particularly relevant when outcomes involve effort, symptoms, or decisions about returning to activity.
The report should show the between-group difference, not merely an improvement from baseline in the LR3 group. It should also show uncertainty around that difference. A large-looking estimate with a wide confidence interval can be compatible with a much smaller benefit, no benefit, or harm.
The amount of change that matters should be considered before recruitment. A statistically detectable difference may be too small to affect a person's life. Conversely, an inconclusive small study may leave a clinically meaningful effect unresolved. Both the size and precision of the estimate belong in the interpretation.
Decide the main outcome before examining the results
A broad research programme can measure many things, but a single study should clearly identify its main question. Testing numerous outcomes and highlighting only the favourable one increases the risk of a misleading conclusion.
FDA's multiple-endpoint guidance explains why outcomes may need an order of priority and statistical methods that account for multiple comparisons. FDA multiple-endpoint guidance For a proposed LR3 study, that could mean treating a prespecified functional outcome as the main test and imaging or molecular measurements as supporting or exploratory evidence.
A public trial record and analysis plan would help readers compare what was intended with what was eventually reported. Registration itself would still not constitute results. A completed report should explain missing measurements, withdrawals, changes to the plan, and relevant funding relationships.
These details matter because the most attractive result is not always the one the trial was designed to answer. Exploratory findings can be valuable without being presented as confirmation.
What would change the conversation?
A useful advance would be a transparent sequence of LR3-specific evidence: credible product and preclinical work, carefully monitored human exposure studies, and appropriately controlled trials addressing a defined clinical need. No single result would answer every population, duration, or combination question.
For someone considering a claim today, ask which of those steps the cited evidence actually represents. A cell result can explain interest in the compound. A small safety study could begin to describe tolerability. A functional trial could test a clinical benefit. Each contributes something different.
Keeping those contributions separate makes the question more constructive: what improvement was demonstrated in comparable people, and what risks were measured alongside it? That is the information needed to weigh a proposed treatment. The IGF-1 LR3 guide provides the molecular background for interpreting future studies without confusing them with mecasermin or general IGF-I research.
Sources
- Francis et al., 1992 — original analogue laboratory research.
- Friedlander et al., 2001 — one-year native IGF-I trial, not LR3.
- FDA surrogate endpoint resources — biomarkers and clinical outcomes.
- FDA clinical outcome assessment guidance — selecting appropriate measures.
- Mongongu et al., 2021 — analogue detection methods.
- INCRELEX prescribing information — separate mecasermin safety context.
- Conlon et al., 1995 — LR3 guinea-pig experiment.
- FDA multiple-endpoint guidance — controlling misleading endpoint selection.