
Peptides
October 16, 2026
What SS-31 injection-site reactions tell us about tolerability
On this page
Injection-site reactions are a substantial part of the human evidence on SS-31, also called elamipretide. They are common enough that a discussion of the drug's potential benefits is incomplete without them. A reaction may be medically mild yet still make repeated treatment uncomfortable or difficult to continue.
The useful questions go beyond whether a red patch occurred. How many participants were affected? How long did symptoms last? Were they local or part of a wider allergic reaction? Did they interfere with treatment? And was the product the same formulation being considered now?
The published studies and Forzinity prescribing information help answer parts of that picture. They do not support treating every reaction as harmless, interpreting redness as proof that a drug is working, or transferring trial safety findings to any product sold under the name SS-31.
What counts as an injection-site reaction?
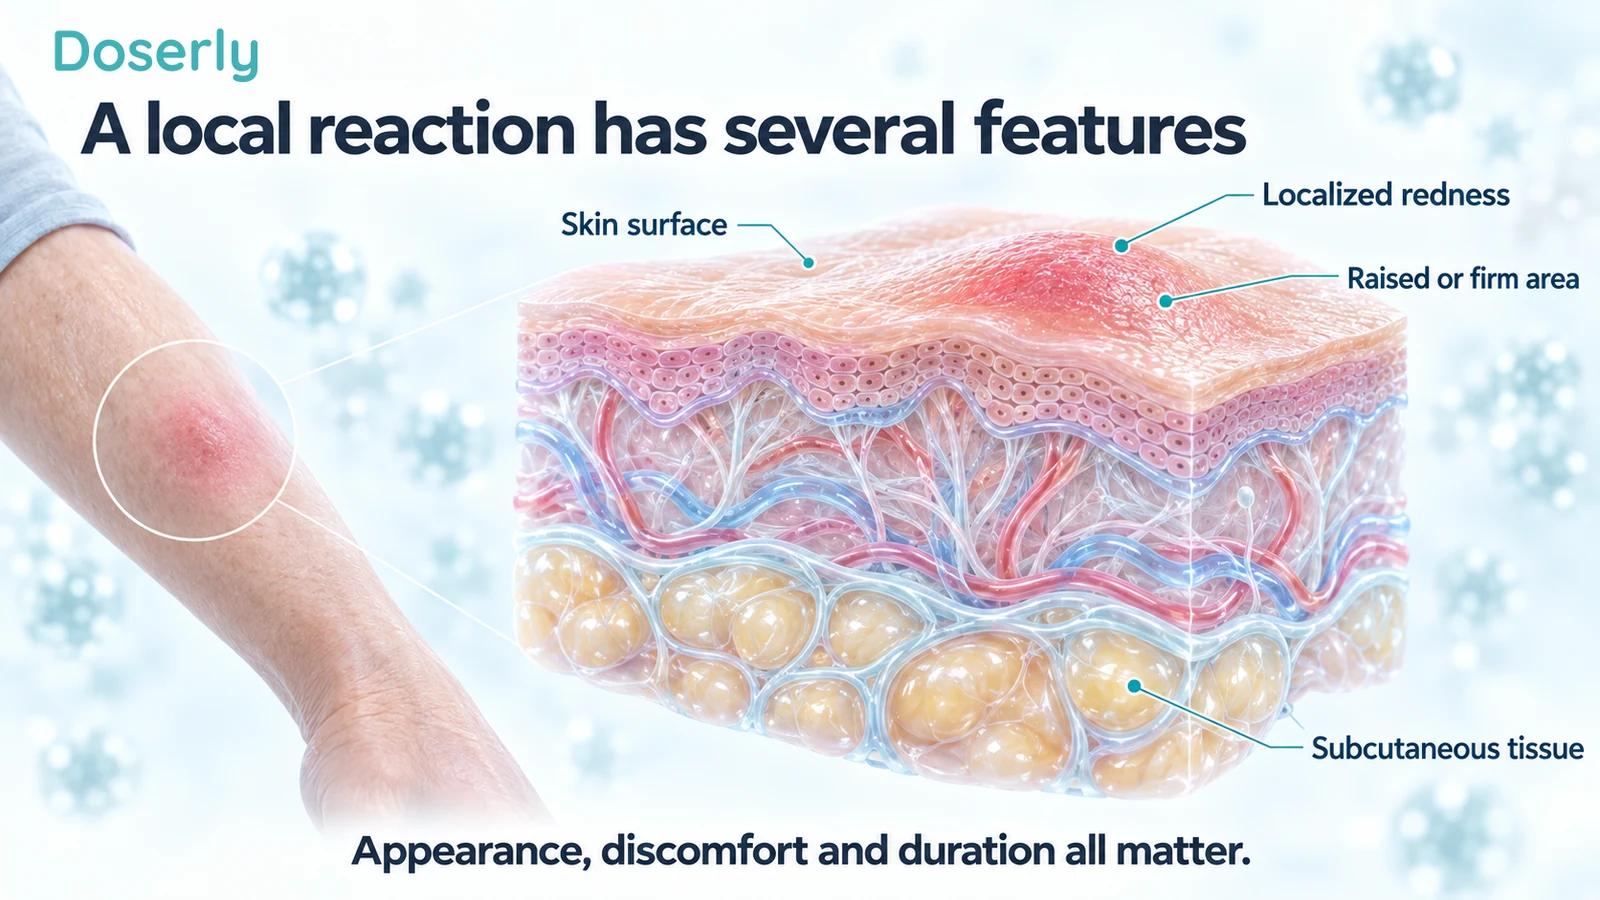
The term groups together several local findings. Erythema means redness; pruritus means itching; induration means a firm area of tissue. Pain, bruising, swelling and localized hives can also appear in reaction reports.
These descriptions tell us what was observed. They do not necessarily identify one shared cause or predict what will happen with the next exposure. A visible change, the discomfort it produces and its duration are separate features.
This is why “I had a reaction” is only the start of a useful account. A brief area of redness and a persistent painful lump could both fall within a broad local-reaction category while having very different effects on daily life.
The FDA's Forzinity trial snapshot lists the individual reactions reported in the small Barth syndrome trial. The categories make the experience more specific than an overall statement that treatment was tolerated.
How common were reactions in the Barth trial?
The blinded Barth syndrome trial included 12 participants in a crossover design, so participants received both elamipretide and placebo during separate periods. All 12 experienced an injection-site reaction during elamipretide treatment, compared with eight during placebo.
Redness was reported in 12 versus three participants, pain in nine versus five, and induration in eight versus two. These are participant counts during the respective treatment periods, not the percentage of individual injections that caused symptoms. FDA trial snapshot
The placebo findings matter. They show that some local reactions occurred under control conditions too. The higher counts with elamipretide remain relevant, but the comparison is more informative than attributing every symptom after an injection to the active molecule alone.
With only 12 participants, one person's experience changes a percentage considerably. Counts are therefore especially useful. They communicate the observed burden without giving a small dataset an appearance of precision it cannot support.
A participant rate is not an injection rate
Suppose a participant has one reaction during many administrations. A table reporting “participants with at least one event” counts that person as affected. The same table may also count a participant with repeated reactions as one affected person.
Without event frequency and duration, those experiences cannot be distinguished from the headline percentage alone. This is a general measurement issue, not a claim that the Barth participants had only one reaction.
The denominator also changes the question. The proportion of people affected, the number of reactions per administration and the proportion who stop treatment each describe different aspects of tolerability. One cannot be substituted for another.
When a summary says “100% had reactions,” ask what was counted and over what period. The result may be important while still leaving uncertainty about the likely burden for an individual patient.
Were local reactions seen outside Barth syndrome?
Yes. In MMPOWER-2, a four-week crossover study in 30 people with genetically confirmed primary mitochondrial myopathy, injection-site reactions were the most commonly reported adverse events with elamipretide. They affected 80% of participants receiving it, and most were described as mild. No serious adverse events or deaths were reported during that study. MMPOWER-2, 2020
ReCLAIM-2 studied 176 people with age-related macular degeneration over 48 weeks. Local reactions were again the most common events. The report's 86% versus 71% figures refer to participants reporting any adverse event, not specifically to injection-site reactions. Its primary efficacy endpoints were not met. ReCLAIM-2
These findings support taking local tolerability seriously across more than one clinical program. They do not establish that the exact rate is the same across diagnoses, ages, exposures or formulations.
A safety figure should stay attached to the population and event definition that produced it. Combining different studies into one universal “SS-31 reaction rate” would obscure those differences.
“Mild” does not mean irrelevant
Severity, seriousness and acceptability answer different questions. A mild symptom may not threaten health, yet a recurring symptom can still interfere with clothing, sleep, concentration or willingness to continue treatment. Those examples describe possible practical burdens, not outcomes measured in every elamipretide trial.
A serious event is classified by its consequences, such as requiring urgent intervention or hospitalization; it is not simply another word for a very uncomfortable symptom. Conversely, the absence of serious events in a small study does not prove that serious events cannot occur.
Tolerability also depends on what benefit is realistically expected. A person and clinician may weigh a recurring burden differently when treating a specific diagnosed disease than when the proposed benefit is uncertain.
The key is to avoid collapsing the discussion into “safe” or “unsafe.” A useful assessment describes the event, its impact, the relevant evidence and the clinical goal.
What longer follow-up adds—and cannot add
The TAZPOWER open-label extension followed a small Barth syndrome cohort for substantially longer than the blinded periods. Ten participants entered and eight reached week 168. Injection-site reactions remained the most common adverse events. Long-term TAZPOWER report, 2024
Longer exposure is valuable because short trials cannot describe the experience of repeated treatment over years. However, the extension remained small and lacked a concurrent placebo group. Its participants also represent people who entered and continued that phase of the study.
This limits what “long-term safety” can mean. Extended observation can reveal practical patterns, while a small cohort may miss uncommon events and may not reflect people who discontinue earlier.
A report of continued treatment should therefore be read alongside retention and adverse-event information. It is evidence about that cohort's experience, not a promise of effortless long-term use for everyone.
Local reactions and serious hypersensitivity are different concerns
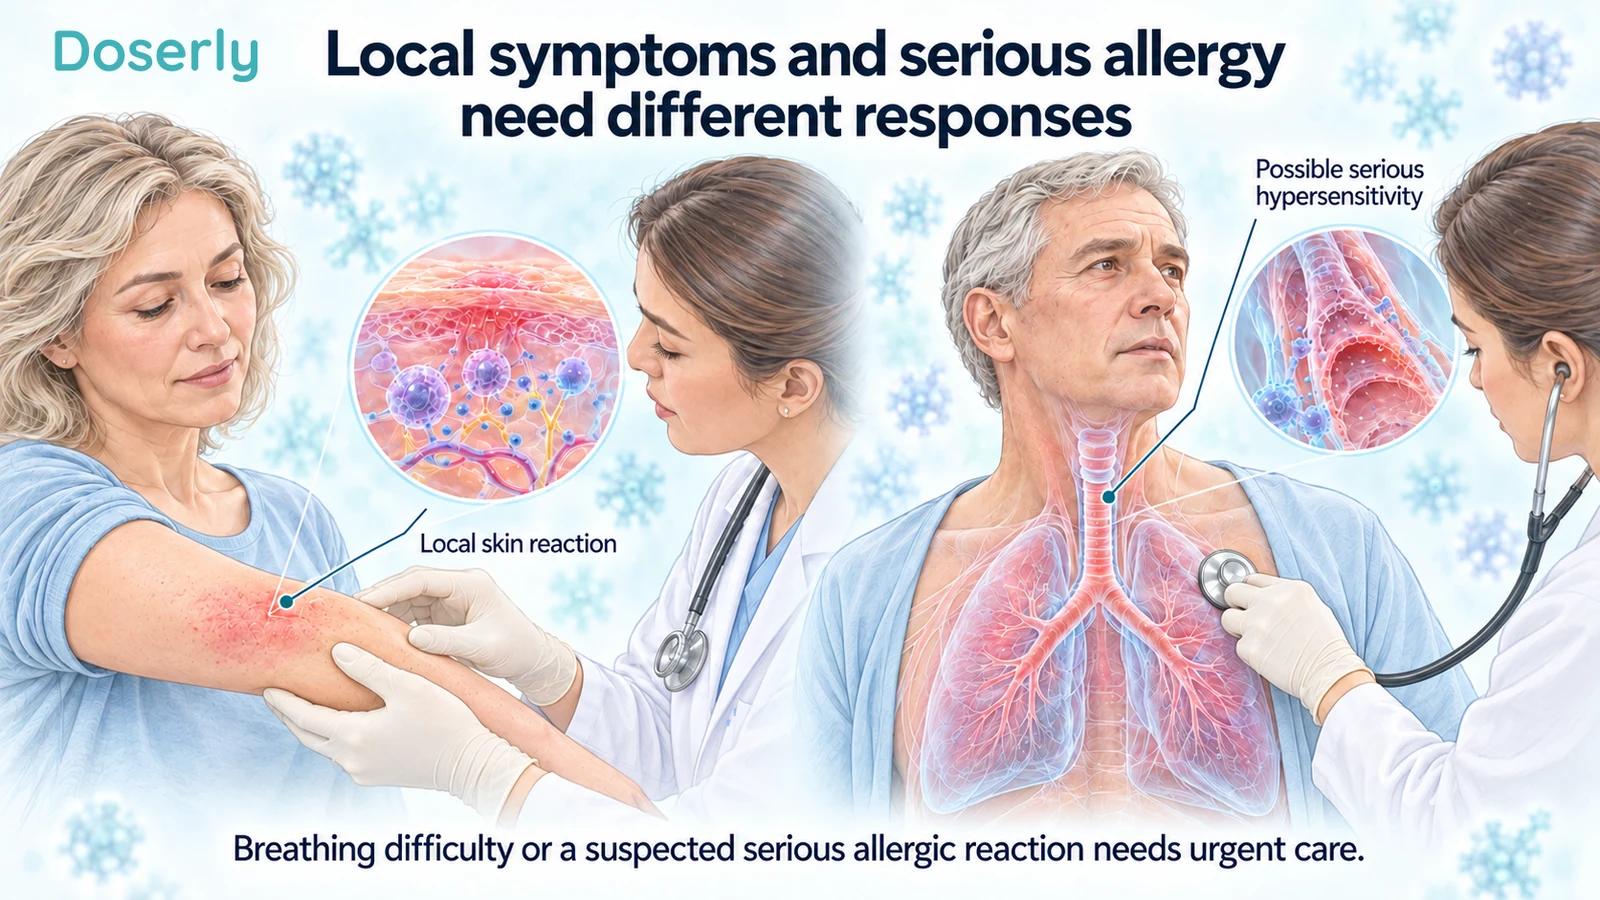
Forzinity's label warns that hypersensitivity can include serious allergic reactions requiring emergency intervention. Reported features include skin eruptions and respiratory symptoms, and onset has ranged from minutes to months after starting treatment.
For an immediate hypersensitivity reaction, the label directs patients to stop treatment and seek immediate medical attention. After serious hypersensitivity, further doses must not be given and the patient should not be rechallenged. Persistent or severe skin reactions also require clinical reassessment. Forzinity prescribing information
A familiar local patch does not establish that a new or spreading reaction has the same significance. Breathing difficulty or a suspected serious allergic reaction needs urgent care, rather than observation to see whether it resembles a previous injection response.
The distinction is not something a photograph alone can reliably settle. Timing, other symptoms and the clinical situation matter.
What have studies tested to reduce reactions?
A company-sponsored phase 1 study evaluated several approaches in ten healthy volunteers using an open-label crossover design. Some interventions reduced selected local symptoms. Topical mometasone showed a signal for reduced induration or swelling; diphenhydramine was associated with sleepiness in half the participants. Ice reduced early pain but also lowered measured elamipretide exposure.
The study was small, involved supervised experimental conditions and was not a long-term trial in people with Barth syndrome. Its accompanying preclinical experiments supported a possible mast-cell receptor mechanism, but do not diagnose the mechanism of an individual patient's reaction. Sullivan and colleagues, 2023
These findings explain why symptom-management choices deserve clinical review. An intervention can affect discomfort, cause its own adverse effects or alter exposure to the medicine. “Less redness” is not the only outcome to consider.
The paper provides a research lead, not a home pretreatment regimen. It does not justify adding medicines or changing administration practices without the prescribing team's advice.
The formulation belongs in the safety discussion
Forzinity is a defined prescription product with specific ingredients, preparation instructions and storage requirements. A research-market product labeled “SS-31” has not been shown equivalent merely because the name refers to the same peptide.
The Forzinity label calls for trained administration, daily site rotation and avoiding tender, bruised, red or hard skin. It also says not to mix other products in the same syringe. The full instructions and clinician training should guide its use. Forzinity prescribing information
A reaction cannot serve as a quality test. Redness does not verify identity, purity or potency, and absence of redness does not establish those properties either. The sensation at the skin is not an analytical assessment of the product.
For the same reason, changing an unknown formulation until it “feels right” does not reproduce the controlled product and monitoring used in trials.
What information makes a report useful?
Describe when the reaction began relative to administration, where it appeared and whether it stayed local. Note its appearance, discomfort, how long it lasted and whether it interfered with usual activities. Include symptoms elsewhere rather than assuming that only the injection area is relevant.
Record the product and any changes in administration or other medicines. This provides context for the clinician; it does not mean any one change has been established as the cause.
A photograph can help document visible progression when appropriate, but it cannot capture pain, breathing symptoms or every important feature. A brief written timeline often supplies information that an image cannot.
Do not delay urgent care to complete a log. For ongoing nonurgent local symptoms, the useful question is how the prescribing team wants them reported and managed, including when to contact the team before another dose.
Does a reaction tell you that SS-31 is working?
No clinical evidence presented here validates a local skin reaction as a marker of therapeutic benefit. A skin response and the intended disease outcome are different measurements.
A person could experience discomfort without improvement in the target symptom or function. Conversely, lack of a visible reaction cannot establish that a prescribed medicine failed to reach its target. Neither inference follows from the skin's appearance alone.
This matters when reactions are described as “proof of activity” or something to welcome. Such language can make it harder to report burden honestly and can encourage continuation without a clear assessment of benefit.
The relevant comparison is between the treatment goal, evidence of benefit and experienced adverse effects. The SS-31 guide places these tolerability findings alongside the clinical results and the specific Forzinity indication.
A complete account includes the burden
The elamipretide literature supports a clear conclusion: local reactions are common and deserve explicit attention. Their meaning depends on the event definition, study population, duration and impact on treatment.
It also supports keeping local tolerability separate from serious hypersensitivity and from claims about product quality or efficacy. A frequent event can be manageable in a clinical setting while still being important enough to discuss and document.
For someone receiving prescribed treatment, a useful conversation is concrete: what reaction occurred, how much it affected daily life, what benefit is being sought and what the clinical team recommends next. That is more informative than treating discomfort as either automatically harmless or proof that the treatment is working.
Sources
- FDA Forzinity trial snapshot: participant-level local-reaction counts.
- MMPOWER-2, 2020: early myopathy tolerability.
- ReCLAIM-2: longer eye-disease trial and adverse-event definitions.
- TAZPOWER extension, 2024: long-term small-cohort observations.
- Forzinity prescribing information: hypersensitivity precautions and product-specific instructions.
- Sullivan and colleagues, 2023: small intervention study and preclinical mechanism work.