
TRT
October 16, 2026
Testosterone undecanoate injections: what long-acting really changes
On this page
A testosterone injection that lasts for weeks can make treatment feel less intrusive. There is no daily application to remember, and the next administration may be far enough away that ordinary life takes priority again. For someone with a clear need for replacement, that convenience can matter.
The same persistence also changes the decisions around treatment. A long-acting injection continues releasing medicine after the appointment ends. It cannot be removed simply because a symptom appears or a laboratory result is unexpected. Its suitability depends on the diagnosis, the exact product, the follow-up plan, and how much flexibility the person needs.
Testosterone undecanoate is an ester of testosterone used in several formulations. Here the subject is the long-acting intramuscular injection. Oral testosterone undecanoate is a different delivery system; sharing an ingredient name does not make its absorption, precautions, or instructions interchangeable.
What “long-acting” means biologically
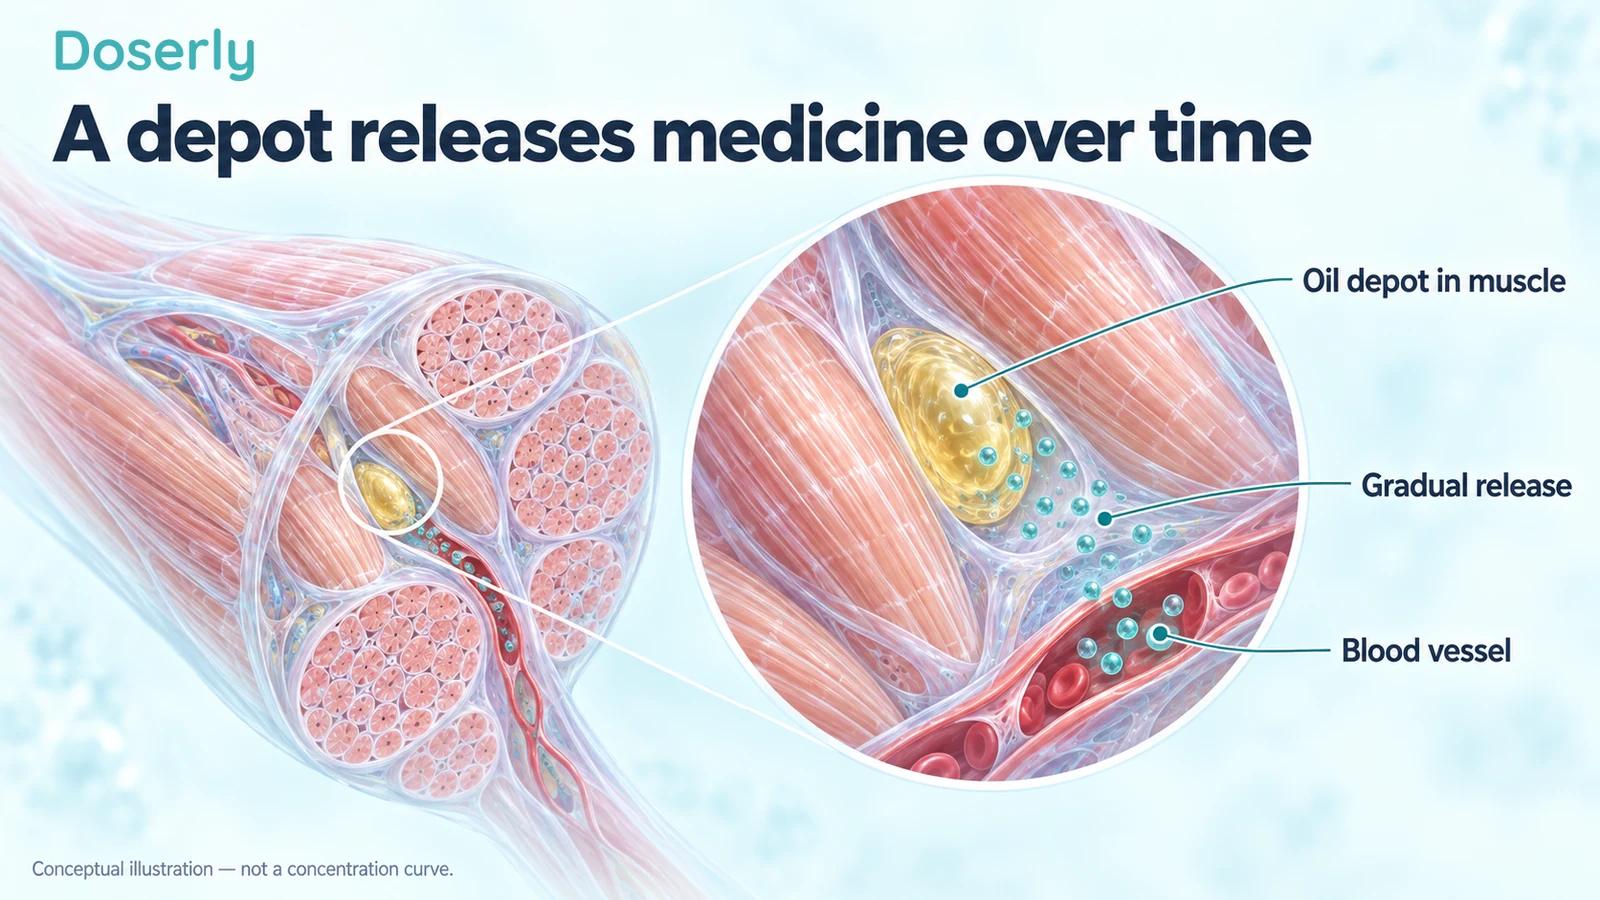
An intramuscular depot is medicine deposited in tissue for gradual release. With injectable testosterone undecanoate, the oil-based preparation releases the ester over time; enzymes then separate it into testosterone and undecanoic acid. The prolonged exposure comes from the formulation and release process, not from a new kind of testosterone effect. Nebido product information
This helps explain both the appeal and the constraint. A depot can maintain exposure between widely spaced appointments, but a decision not to give another injection does not instantly eliminate the medicine already present.
“Long-acting” also does not mean a perfectly flat hormone concentration. Blood levels still change over an interval, and people differ in their response. Describing a formulation as steady is most useful when tied to measured pharmacokinetics rather than a promise that symptoms can never fluctuate.
A laboratory sample is therefore a snapshot taken at a particular point in the treatment interval. The date of the last injection matters. A number collected soon after administration should not be casually compared with one collected near the next planned injection as if the circumstances were identical.
The brand and country are part of the prescription
The US product AVEED and the UK product Nebido illustrate why “testosterone undecanoate injection” is not a complete set of instructions. Their labeled amounts and schedules differ.
The US AVEED label describes 750 mg at initiation, again four weeks later, and then every ten weeks. The UK Nebido information describes 1,000 mg with a maintenance interval of ten to fourteen weeks and a different approach to the initial interval. These are descriptions of the labeled products, not a schedule to select or modify yourself. AVEED label, Nebido product information
That distinction matters when reading accounts from another country. An appointment interval that is ordinary for one licensed product may not be the local instructions for another. The volume, administration requirements, and monitoring context also need to match.
If care is transferred, record the actual brand, formulation, amount administered, and date. “Long-acting testosterone” in a message to a new clinic leaves avoidable uncertainty. A person moving between countries should arrange continuity with a clinician rather than assume the next available product is a direct substitution.
Doserly's injectable testosterone undecanoate guide provides broader context. The current local product information and the prescribing clinician remain the relevant sources for an individual administration plan.
What the pharmacokinetic trial established
A multicenter, unblinded phase 3 study published in 2010 enrolled 130 adult men with low testosterone and followed an injectable undecanoate regimen over 84 weeks. Its main measurements were testosterone and related hormone concentrations and safety parameters. Average hormone concentrations were maintained within adult male reference ranges at the measured time points. Wang and colleagues
This supports the ability of that regimen to provide sustained replacement exposure. It does not establish that undecanoate is the best formulation for every symptom or every patient. The study was not a blinded comparison designed to show superior sexual function, mood, fertility, or cardiovascular outcomes against all other options.
An average is also not a guarantee about every measurement in every participant. The useful clinical question is whether your exposure and response are appropriate, with blood results interpreted alongside the treatment schedule and symptoms.
When someone says a product “works for months,” clarify what they mean. Sustained drug delivery, a hormone concentration in a reference range, and sustained improvement in a symptom are related but different observations. Each can contribute to a treatment decision without standing in for the others.
Observation at the injection visit serves a specific purpose
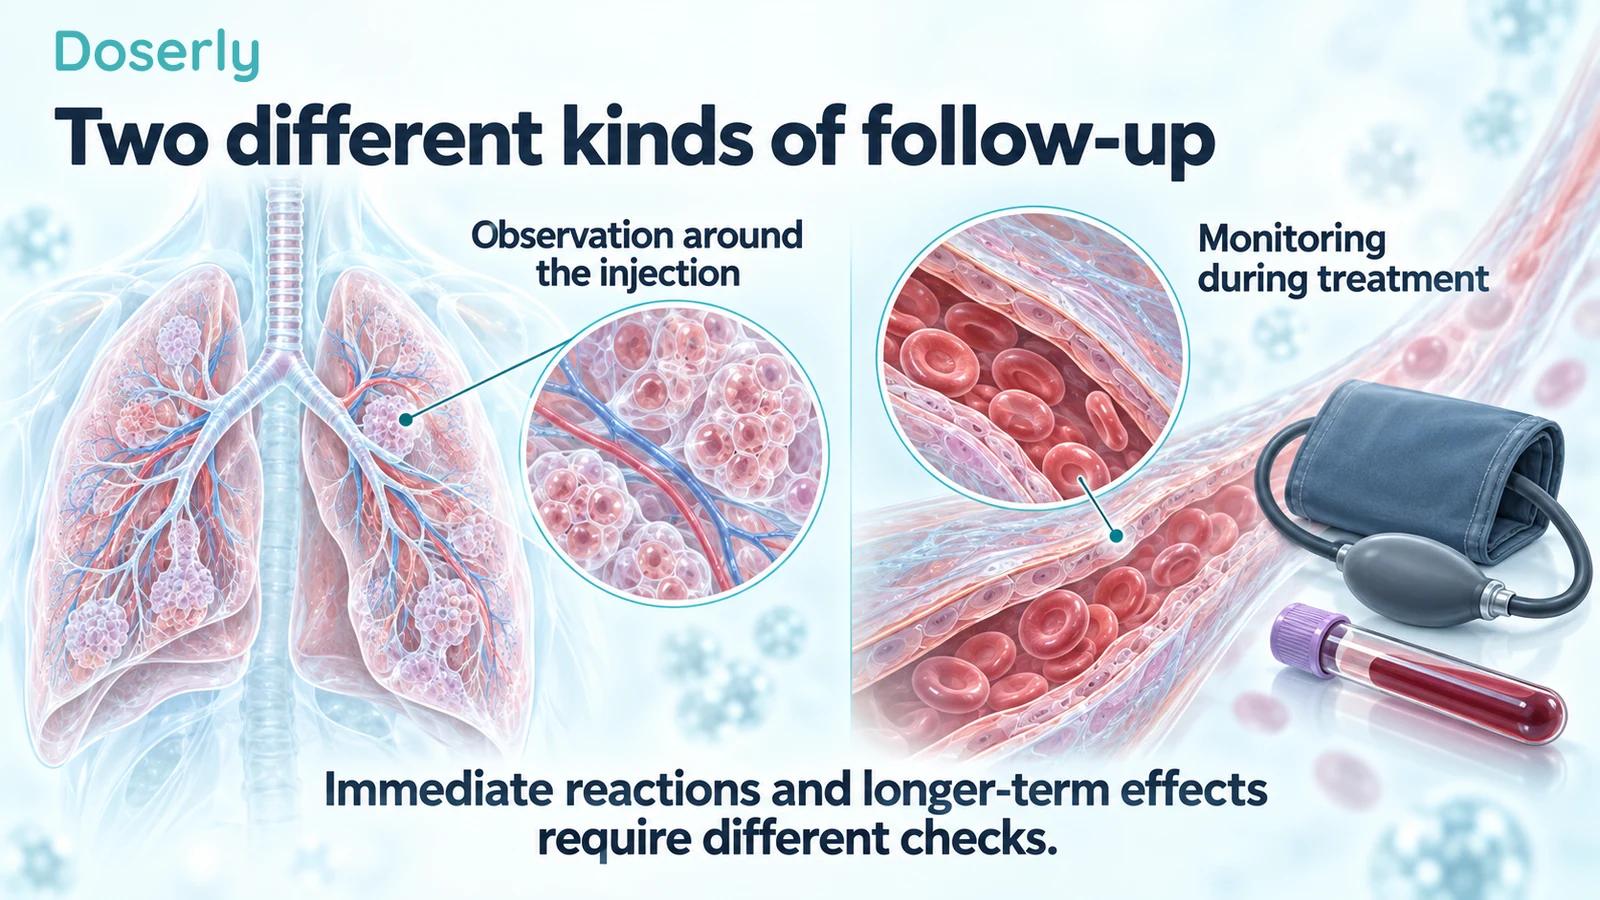
The AVEED label has a boxed warning for serious pulmonary oil microembolism reactions and anaphylaxis. Pulmonary oil microembolism, often shortened to POME, refers to an acute reaction associated with oil entering the circulation and reaching the lungs. It is different from the usual discussion of a blood clot traveling to the lung.
Possible symptoms include coughing, breathlessness, chest discomfort, dizziness, or fainting during or shortly after administration. Anaphylaxis is a severe allergic reaction. In the United States, AVEED is restricted through a risk-management program, and patients must be observed in the healthcare setting for 30 minutes after every injection. AVEED prescribing information
The word “every” matters. Having tolerated previous injections does not remove the requirement. Nor should a person dismiss new breathing symptoms because they have heard that the reaction is uncommon.
The UK Nebido information also describes oily pulmonary microembolism and reported anaphylactic reactions, with observation during and immediately after administration. Its wording should not be replaced by assumptions about the US program. Local staff should follow the exact product requirements.
These precautions are reasons to use an appropriate clinical setting, not instructions for managing a reaction at home. Report symptoms immediately to the staff administering the medicine; severe breathing difficulty or collapse outside the clinic requires emergency help.
A low reported reaction rate is not a personal exemption
A postmarketing safety analysis examined POME reports after US injectable testosterone undecanoate use. Such research helps characterize events occurring in clinical practice and the circumstances in which they are recognized. It is a different kind of evidence from a randomized trial. Postmarketing analysis
Spontaneous reports have important limitations. Not every event is necessarily reported, the available descriptions vary, and a denominator based on distributed doses is not the same as direct observation of every administration. A reported rate should not be treated as the precise probability for a particular patient.
The practical point is not to calculate whether you personally can skip observation. The product requirements already account for the need to recognize and manage an uncommon but potentially serious event.
This also explains why comparing reaction rates from different studies can mislead. Different countries may use different products, doses, reporting systems, and definitions. A clinic actively asking about symptoms after every injection can detect events differently from a passive reporting database.
Fewer injections do not mean fewer clinical responsibilities
The usual replacement-therapy questions continue between visits: is the treatment helping, is exposure appropriate, and are adverse effects emerging? Long duration does not make the body exempt from testosterone's effects.
The Endocrine Society recommends monitoring treatment response, testosterone, hematocrit, and adverse effects, with prostate assessment where appropriate to the patient's age and risk discussion. Hematocrit describes the proportion of blood occupied by red cells; it can increase during testosterone treatment. Endocrine Society guideline
Blood pressure also deserves attention. The current AVEED label includes a blood-pressure warning and recommends periodic monitoring, particularly for men with hypertension. A normal testosterone result does not tell you whether blood pressure or hematocrit has changed.
The monitoring schedule should be explicit enough to follow between injections. Know who orders the blood tests, when the sample should be taken relative to administration, who reviews the result, and how the clinic contacts you if a change is needed.
Doserly's TRT blood-work guide can help you organize the questions. It is especially useful to record injection and sample dates together, so a result does not become detached from the timing that makes it interpretable.
Flexibility matters before the first depot is given
A long interval may suit someone who finds frequent self-administration difficult and can reliably attend the clinic. Another person may prioritize the ability to change exposure more promptly if tolerability is uncertain. These are legitimate differences in preference and circumstances.
The Endocrine Society's formulation guidance includes pharmacokinetics, burden, cost, and preference. It does not frame the longest duration as automatically the best treatment. An appropriate plan is one that fits the indication and can be monitored safely. Guideline
Before starting, discuss anticipated travel, access to the administering clinic, and what happens if an appointment is delayed. The correct response to a missed visit depends on the actual product and treatment history; an internet schedule cannot supply that answer.
Also ask how new symptoms will be handled between appointments. Waiting until the next injection may be inappropriate for a significant adverse effect. A long prescription interval should not become a long interval without access to advice.
Stopping administration is different from recovery
Testosterone treatment can suppress the body's reproductive hormone signaling. When treatment ends, drug exposure declining and the body's own production recovering are separate processes. Neither process can be judged simply by counting from the last appointment.
A study of 303 men without pathological hypogonadism followed reproductive endocrine recovery after two years of injectable testosterone undecanoate or placebo in an earlier trial. Hormonal recovery after testosterone was gradual. The follow-up began three months after the final injection, an essential detail when interpreting its timeline. Recovery study
That population does not provide a promise of recovery for someone with permanent testicular or pituitary disease. It also does not establish when sperm production will recover or when a pregnancy will be possible. Fertility requires its own assessment.
Bring future family plans into the discussion before treatment. A convenient administration schedule cannot make external testosterone a fertility-preserving therapy. The original cause of deficiency, duration of treatment, and reproductive goals all matter more than the convenience of the next appointment.
The decision is about fit, not the longest interval
A useful conversation about long-acting testosterone ends with a clear product name, a reason for choosing it, and a plan for both immediate and ongoing care. It includes what will be measured, what benefit is expected, and how problems will be addressed while the depot is still releasing medicine.
The appeal is real: fewer administration events can make replacement easier to live with. The trade-off is equally real: exposure persists, local product requirements matter, and follow-up continues between injections. Understanding both sides makes convenience a meaningful part of an informed choice.
Sources
- AVEED: FDA prescribing information, 2025
- Nebido: UK summary of product characteristics
- Wang and colleagues: 84-week pharmacokinetic and safety trial, 2010
- Occurrence of pulmonary oil microembolism: Postmarketing safety analysis, 2020
- Endocrine Society: Testosterone therapy guideline
- Recovery of reproductive endocrine function after prolonged undecanoate injections, 2022