
Peptides
October 16, 2026
Oxytocin in childbirth and wellness sprays: why the evidence differs
On this page
Oxytocin has an established place in childbirth care because it can stimulate the uterus to contract. That same hormone name also appears in products promoted for mood, social comfort or intimacy. It is easy to assume that a medicine used in hospitals carries a general endorsement for those other purposes.
The evidence is more specific. An obstetric oxytocin product is used for particular clinical goals, through specified routes, with monitoring appropriate to those goals. A nasal spray proposed for a social or wellness benefit is a separate intervention and needs evidence for that use. The difference is about the product and treatment question, not whether oxytocin is a “real” hormone. Pitocin prescribing information.
Our oxytocin guide introduces the broader research. Here, we'll examine why the hospital context matters and how to interpret a claim that borrows credibility from childbirth medicine.
What oxytocin does in the uterus
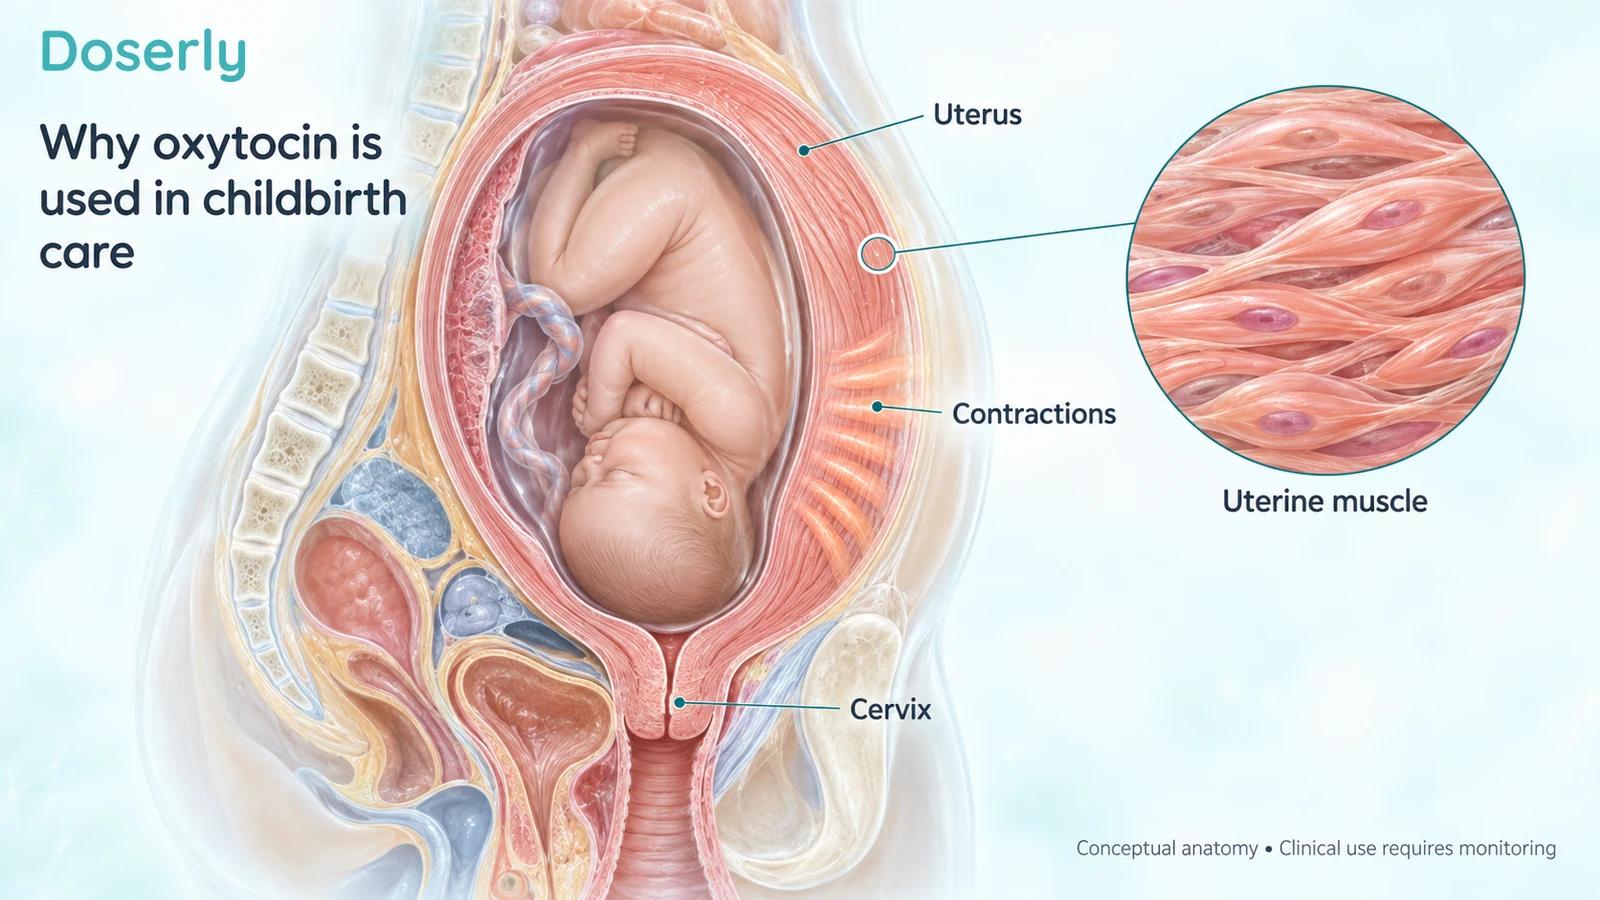
The wall of the uterus contains smooth muscle, called the myometrium. Oxytocin activates receptors involved in increasing calcium inside these muscle cells, supporting contraction. Receptor availability and uterine sensitivity change during pregnancy, so the response is not a fixed property of a dose alone.
The US Pitocin label describes synthetic oxytocin for intravenous infusion or intramuscular injection. Its obstetric indications include initiating or improving contractions in suitable circumstances and controlling postpartum bleeding. For induction or augmentation of labor, the label specifies intravenous use with medical supervision in a hospital. Product label.
This gives clinicians a concrete physiological target. They are not asking whether someone generally feels more connected. They are assessing uterine activity within a clinical situation in which the benefits, risks and alternatives can be considered.
It also explains why “the body already makes it” isn't a complete safety argument. A naturally occurring signal can have a substantial effect when administered as medicine. The relevant question is whether that effect is useful and appropriately controlled in the person receiving it.
Inducing labor and preventing bleeding are different goals
Induction means starting labor. Augmentation means helping labor that has already begun. After birth, oxytocin can also be used in care aimed at preventing or controlling postpartum hemorrhage, meaning excessive bleeding following delivery.
These purposes are related through uterine contraction, but their clinical circumstances differ. A treatment that stimulates contractions before birth affects a situation involving both the pregnant patient and fetus. After delivery, the care team is assessing bleeding and maternal stability as part of a broader postpartum response.
The 2025 WHO consolidated guideline recommends oxytocin as the preferred uterotonic for prevention of postpartum hemorrhage where multiple uterotonic options are available. A uterotonic is a medicine that promotes uterine contraction. The recommendation explicitly requires skilled personnel to administer injectable treatment. WHO prevention recommendation.
A recommendation for preventing postpartum bleeding is not a recommendation for routine wellness use. It identifies a defined event, clinical setting and treatment goal. The fact that a medicine is valuable in that setting cannot answer whether a different formulation helps a different symptom.
Why monitoring is part of the treatment
Oxytocin during labor is not simply a product handed to a patient with a fixed expectation of benefit. Clinicians assess the response and can adjust care if contractions become too frequent or the fetal heart-rate pattern is concerning.
NICE guidance addresses uterine activity and cardiotocography, or CTG, which records the fetal heart rate and contractions. It calls for immediate discontinuation of oxytocin and urgent review when the CTG is pathological. The care team interprets the tracing alongside the wider clinical picture. NICE intrapartum recommendations.
European perinatal guidance likewise recommends continuous monitoring of fetal heart rate and contractions during oxytocin use and emphasizes the minimum effective exposure. It describes circumstances requiring reduction or cessation of the infusion and clinical assessment. European guidelines.
These are active safeguards, not background details. They are part of how the intervention is delivered. Saying that oxytocin is “used safely in hospitals” while omitting selection, monitoring and response to complications leaves out much of what makes hospital use a controlled treatment.
This does not mean someone should be frightened of an appropriate obstetric recommendation. It means its benefit-risk assessment belongs in that care setting, with the professionals who can interpret and respond to what happens.
Even established use still involves research about tradeoffs
The CONDISOX randomized trial studied whether oxytocin stimulation should continue or stop after active labor was established. It randomized 1,200 women and compared management strategies within obstetric care.
Discontinuation was associated with longer time from randomization to delivery: a median of 282 versus 201 minutes. It was also associated with less uterine hyperstimulation, 3.7% versus 12.9%, and fewer fetal heart-rate abnormalities, 27.9% versus 40.8%. These were reported secondary outcomes. CONDISOX primary report.
Those results should not be turned into instructions to stop an infusion. They illustrate a real clinical tradeoff: changing exposure can alter both labor progress and unwanted effects. The study was conducted within monitored maternity services, not as an unobserved comparison at home.
The percentages also apply to the trial's management strategies and participants. They are not estimates of the risk from a nasal wellness product, and they cannot be used to calculate an equivalent nasal dose.
Established medicine does not mean every detail is permanently settled. It means research and guidance address a recognizable clinical question with outcomes that matter in that setting.
Why route changes the evidence question
A drug's route affects how it enters the body and the pattern of exposure it produces. An infusion can be adjusted over time. Intramuscular injection and intranasal administration have different delivery characteristics. A shared ingredient name does not make those patterns interchangeable.
A human mechanistic study compared nasal delivery methods with intravenous oxytocin while measuring regional cerebral blood flow. Some changes, including decreased amygdala perfusion, were explained by increases in circulating oxytocin, while other findings supported route-specific effects. Route-of-administration study.
That research is useful for understanding delivery. It does not establish that a nasal spray improves relationships, treats anxiety or helps someone feel better in daily life. Brain perfusion is a measurement of physiology; a therapeutic benefit needs a clinical outcome.
It also doesn't supply a universal conversion between intravenous, nasal and subcutaneous administration. A numerical conversion of units would not establish equivalent absorption, tissue exposure or effectiveness. Those are questions for formulation-specific research.

What an approval statement actually tells you
An approval relates to a particular medicine and its reviewed uses. It is not an endorsement of every product containing the same named substance, or every proposed reason to take it.
For example, an article may correctly state that oxytocin has an established obstetric use and then discuss an experimental social application. The problem arises if the second claim is presented as though it inherits the first claim's validation. The reader needs to know when the discussion has changed products, routes or indications.
A precise product description should identify what is being offered and why. “Oxytocin for wellness” leaves many questions unanswered: the formulation, intended effect, relevant participants in research, duration of use and how outcomes would be assessed.
This is not a semantic objection. If the benefit being promised is improved intimacy, evidence about uterine contractions does not measure that benefit. The treatment may share a molecule while having a different evidence base.
Compounding is another distinction to keep visible
Compounding can serve patients whose needs cannot be met by an appropriate approved medicine, such as when a necessary formulation is unavailable. FDA explains that compounded drugs are not FDA-approved and are not reviewed before marketing in the same way for safety, effectiveness and quality. FDA compounding questions and answers.
That does not mean every compounded product has the same quality problem or that compounding has no legitimate role. It means the word “compounded” should not be treated as another way of saying “approved generic.”
A pharmacy's ability to prepare something and a trial's ability to demonstrate benefit are separate matters. Product quality is necessary, but a well-prepared product can still lack evidence for the intended clinical outcome.
If a spray is being offered, the important questions include what it contains, who prepared it, which route is intended, and which direct study supports the proposed use. A reference to Pitocin's obstetric history does not fill those gaps.
Why the comparison should not be reversed
It would also be a mistake to take uncertainty about wellness sprays and conclude that oxytocin has no valid medical uses. The obstetric role and the experimental social role should remain separate in both directions.
Likewise, a risk observed during labor should not be presented as the measured rate of that risk in a nonpregnant person using a different preparation. The populations, exposure and organs at issue differ. Accurate safety discussion identifies what is known in each setting and what has not been adequately studied.
This distinction helps prevent two unhelpful extremes: treating all oxytocin as harmless because it is familiar, or treating appropriate maternity care as suspect because an unrelated commercial claim is unsupported.
The better question is always specific: what product, for what purpose, in whom, under what conditions?
What to discuss with the clinician involved
During maternity care, useful questions concern the reason oxytocin is being recommended, what changes the team hopes to see, how monitoring will work and what would prompt a different plan. Those decisions depend on the individual pregnancy and progress of labor.
For a proposed wellness use, start with the symptom or goal. Ask whether the supporting trial tested that outcome with the same route and a comparable formulation. If the answer rests mainly on childbirth use, then the evidence being cited is not directly answering your question.
A record of medicines, formulations and treatment goals can help keep these discussions clear. It is especially useful when different clinicians or products use the same hormone name for different purposes. It does not replace professional assessment or create an evidence-based dosing conversion.
Oxytocin's established obstetric value is real. It belongs to the clinical uses supported by the relevant label, research and guidance. A claim about mood, intimacy or social comfort needs its own evidence, as the oxytocin guide explains in the wider research context.
Sources
- Pitocin US prescribing information, updated 2026.
- NICE NG235 intrapartum care.
- European perinatal oxytocin guidelines, 2021.
- CONDISOX randomized trial, 2021.
- WHO postpartum-hemorrhage prevention recommendation, 2025.
- Human route-of-administration study, 2020.
- FDA: compounding questions and answers.